












Summary
A hospice eligibility agent reads each referral packet, checks it against CMS eligibility criteria and your own scoring rules, and returns an Eligible, Pending Review, or Ineligible status with the reasoning attached. Your physician still certifies the prognosis. This guide shows COOs and CIOs where AI eligibility verification for hospice fits, which documentation gaps it can catch, and how to evaluate it before you buy.
Introduction
Picture a Friday, 4:40 p.m. A 38-page referral packet arrives by fax from a hospital discharge planner.
Half of it is scanned, the face-to-face note is buried on page 29, and your intake nurse has six more packets waiting. She has two bad options: rush the review and risk admitting a patient the chart can’t support or hold the referral until Monday and risk losing it to the hospice that answered first. The first option has a documented price. In a June 2026 audit, the HHS Office of Inspector General reviewed 100 initial hospice certification periods and found that 45 did not meet Medicare requirements. In 21, the clinical record didn’t support a terminal illness. In the other 24, the documentation fell short.
A hospice eligibility agent is built for that Friday. It reads the packet, checks it against CMS criteria and your own rules, and tells your team what’s missing in minutes. We are covering how AI agents improve hospice eligibility verification while staying CMS-compliant, which covers the agent layer that sits on top of a governed data foundation. This is the first of a series of articles focusing on hospice eligibility agents and how they can help in automating intake validation in line with CMS criteria.
COOs and CIOs at hospice care agencies who need answers before they sign anything will find a lot of value here. Know what the agent checks, where it stops and the physician starts, and what evidence it leaves behind for a reviewer.

What is a hospice eligibility agent?
A hospice eligibility agent is an AI workflow that reads a referral packet, extracts the clinical values that matter for Medicare hospice eligibility, scores them against criteria your clinical team defines, and returns a status with the reasoning attached. The status is Eligible, Pending Review, or Ineligible. A person approves the result.
A checklist needs someone to read the packet first. The agent does the reading. Referral packets arrive as scanned PDFs, faxed notes, and EHR exports, and optical character recognition (OCR) turns them into structured values such as the Palliative Performance Scale (PPS) score, hospitalizations, and documented decline. Manual packet review is one of the biggest drivers of referral intake delay, and two reviewers will often score the same chart differently. An agent applies one set of rules to every packet.

What do CMS hospice eligibility criteria require at intake?
The federal rules at 42 CFR 418.22 set the documentation standard that most intake errors trace back to. The table maps each requirement to what an agent can check and who makes the call.
| Requirement | What CMS expects | What the agent can check | Who decides |
| Six-month prognosis | Certification that life expectancy is six months or less if the illness runs its normal course | Statement is present; supporting clinical findings are in the packet | Certifying physician |
| Who certifies | For the first 90 days: medical director, physician designee, or an IDG physician, plus the attending physician if there is one | Required signatures and dates are present | Physicians |
| Timing | Written certification before the claim; oral certification within 2 calendar days if the written one isn’t in hand; up to 15 calendar days before the election date | Certification dates against the election date | Hospice admin staff |
| Narrative | Brief, patient-specific explanation of clinical findings. No check boxes or standard language. Signature and attestation in the right place | Narrative is present, placed correctly, and signed | Certifying physician |
| Face-to-face encounter | Required before the third benefit period and each recertification after it, no more than 30 days prior, by a hospice physician or nurse practitioner, with a signed attestation | Dated, signed attestation is in the record | Hospice physician or NP |
| Election statement | Names the hospice and attending physician, acknowledges care is palliative, carries the patient’s signature | Each element is present | Patient or representative, hospice staff |
| Election statement addendum | FY 2027 final rule: addendum on non-hospice service coverage for every beneficiary at election | Yes or no field is complete | Hospice staff |
| Benefit periods | Two 90-day periods, then unlimited 60-day periods, each needing certification | Which period applies and what is due | Hospice staff |
What is a certification of terminal illness (CTI)?
A CTI is the physician’s signed statement that the patient’s life expectancy is six months or less if the illness runs its normal course. It needs a patient-specific narrative of the clinical findings, a signature and date, and the dates of the benefit period it covers.
Who certifies hospice eligibility?
Physicians do. OIG’s report notes that only a Doctor of Medicine or Osteopathy can certify or recertify a terminal illness. For the first 90 days that means the hospice medical director, physician designee, or an interdisciplinary group physician, and the attending physician if the patient has one.
What is a face-to-face encounter, and when is it required?
It’s an in-person visit by a hospice physician or nurse practitioner to gather clinical findings on continued eligibility. It’s required before the third benefit period and before every recertification after that, no more than 30 days ahead, with a signed and dated attestation.
How do LCDs and MAC jurisdiction change the eligibility check?
A local coverage determination (LCD) is a Medicare Administrative Contractor’s published criteria for when a service is reasonable and necessary. For hospice, LCDs define terminal status by diagnosis. Three MACs cover four home health and hospice jurisdictions: National Government Services (two), CGS Administrators (one), and Palmetto GBA (one), according to OIG.
Their criteria differ. NGS keeps its terminal-status criteria in a single LCD (L33393), Palmetto publishes disease-specific ones, and as we covered in our look at why polished AI documentation still fails hospice audits, CGS and NGS diverge on conditions such as ALS and renal disease. Reviewers look for documented decline, and for dementia, heart failure, and COPD they look for diagnosis-specific findings alongside PPS.
For a COO, that makes one national eligibility template a liability. Your scoring rules need to reflect the LCD language your MAC applies and the diagnosis in the packet. Caregence’s eligibility agent applies criteria that your clinical leaders write in plain English, so the LCD logic is yours to define and update. Ask every vendor, us included, who owns that mapping and how quickly it changes when a MAC revises an LCD.
Where does the hospice eligibility agent stop and the physician start?
The agent screens. The physician certifies. Under the federal rules, certification rests on the physician’s clinical judgment about the normal course of the illness, and the narrative has to be composed by the physician from the patient’s record. The agent prepares the evidence, checks it for completeness, and scores it. A human approves every determination.
| Task | Who does it | Why it sits there |
| Read the packet and extract PPS, prognosis, hospitalizations, decline indicators | Agent | High volume, repeatable, and OCR handles scanned pages |
| Check that the CTI, narrative, and election statement are complete | Agent | Rule-based and fully checkable |
| Apply the scoring criteria to every referral | Agent | Same logic every time removes reviewer variance |
| Write and update the scoring criteria | Clinical leadership | The platform never sets the clinical standard |
| Judge the prognosis and write the narrative | Certifying physician | Required by 42 CFR 418.22 |
| Resolve Pending Review cases | Clinician | Borderline packets need clinical judgment |
| Approve the final status | Human reviewer | AI scores and explains; a person decides |
Pending Review is where the design matters. A borderline packet should land in front of a clinician with the gap named, and it shouldn’t be quietly scored up or down to fit a threshold.
Which documentation gaps cause eligibility denials, and which can an agent catch?
OIG’s June 2026 audit gives a clear breakdown of how initial certification periods fail. Its sample covered fiscal year 2021 claims, so the counts describe failure types and shouldn’t be read as today’s error rate. The same records are what a MAC asks for in an additional documentation request (ADR) or a Targeted Probe and Educate (TPE) review.
| Failure type in OIG sample (of 100 periods) | Count | Can an intake agent help? |
| Clinical record did not support a terminal illness | 21 | Partly. It surfaces decline indicators and flags thin evidence. The physician judges. |
| No supporting records provided | 7 | Partly. The stored packet and audit trail create a record to produce. |
| Election statement missing | 3 | Yes. Completeness check at intake. |
| Election statement missing required elements | 7 | Yes. Element-level check. |
| Certification of terminal illness missing | 5 | Yes. Completeness check. |
| Certification elements missing, such as signatures | 2 | Yes. Signature and date check. |
Seventeen of the 45 failures were election statements or CTIs that were missing or incomplete. A rule-based completeness check at intake addresses those directly. The 21 clinical-support failures stay with the physician, though an agent can pull the decline indicators out of the packet so the narrative has evidence to cite.
OIG also flagged new enrollees with no inpatient or emergency room claim in the prior 18 months as a high-risk group, estimated Medicare could have saved $255.1 million had the MACs reviewed that group, and CMS concurred with the recommendation to consider it in eligibility reviews. The finding is claims-based, and a packet shows only what’s documented. Still, a configurable intake rule can route a packet with no recent hospital or ER use to a clinician for a closer look.
The pressure is rising on the compliance side too. The CMS FY 2027 hospice final rule, issued July 30, 2026, requires an election statement addendum on non-hospice coverage for every beneficiary at election, and CMS now scores providers with the Service and Spending Variation Index, which uses nine claims-based measures. Each new required field is another item a reviewer can check across every admission.
How does the Caregence Hospice Eligibility Agent work?
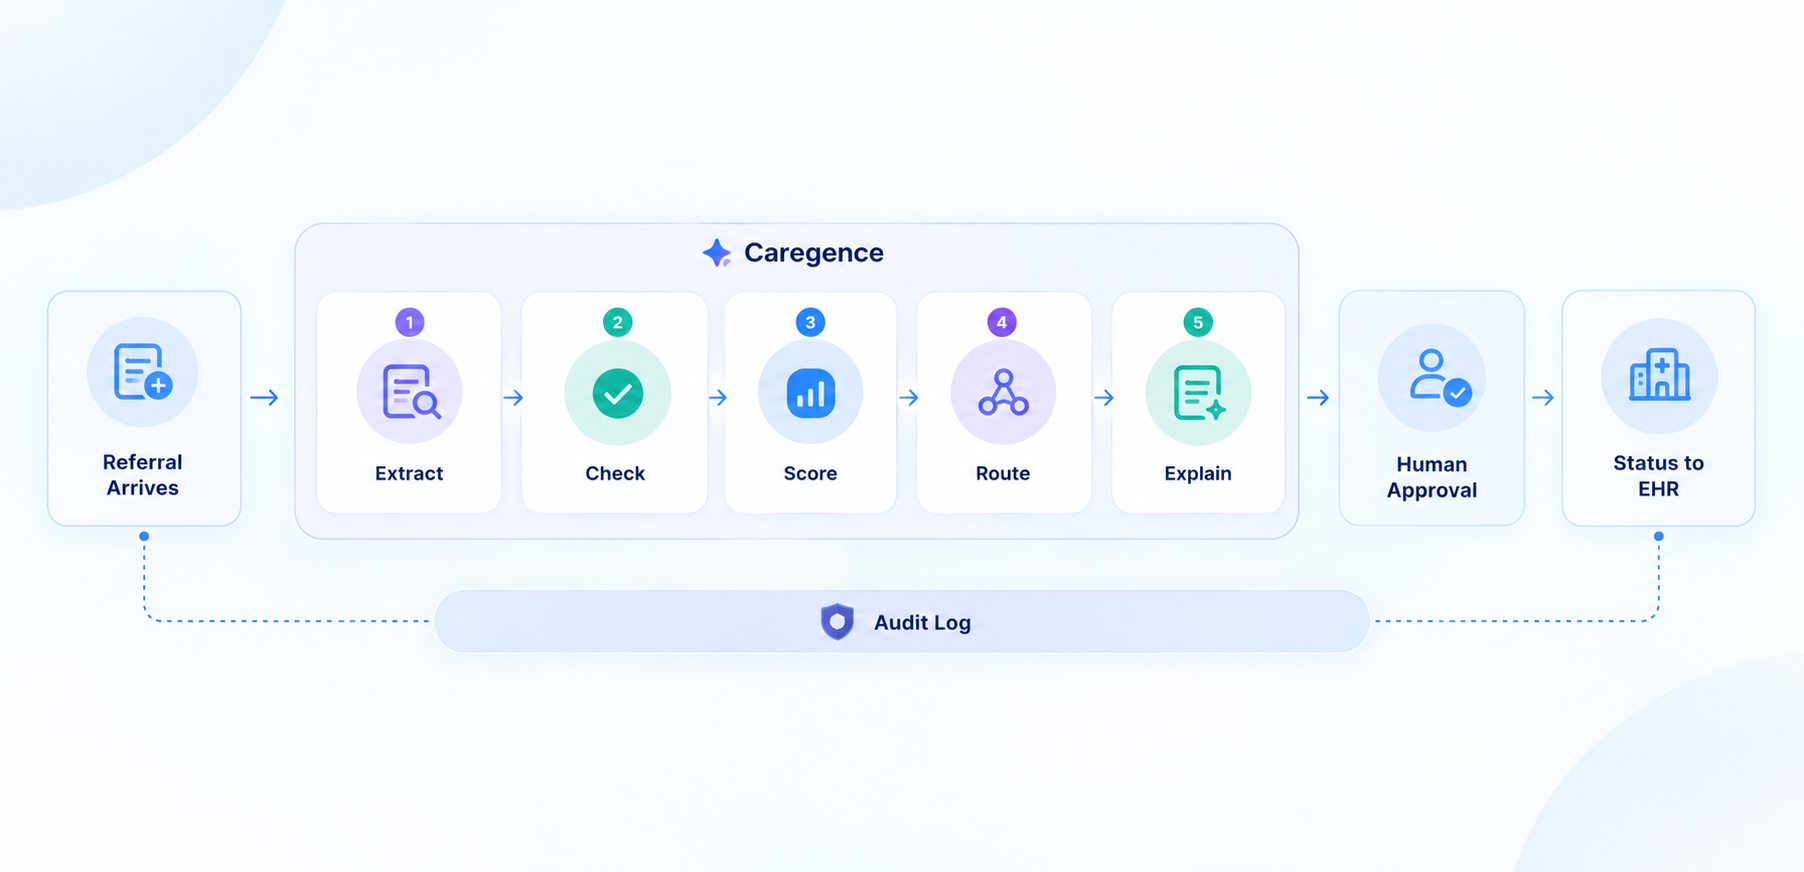
The Caregence Hospice Eligibility Agent runs in five steps. It starts when a referral lands through your intake portal, EHR, or CRM, or through an API call, webhook, or scheduled task.
| Step | What happens | Output |
| 1. Get data | Pulls the physician certification, face-to-face notes, decline indicators, admission form, and clinical notes from the hospice system | Complete referral packet in one place |
| 2. Extract (OCR) | Azure Document Intelligence parses scanned and unstructured PDFs | Structured values: PPS, prognosis, hospitalizations, decline indicators |
| 3. Score | The intelligent agent applies your scoring logic and reasons over gaps | Total score, determination, and the factors behind it |
| 4. Update status | Writes the determination back to the hospice system and portal record | Eligible, Pending Review, or Ineligible |
| 5. Notify | Emails the recipients you configured | Clinician sees score breakdown and notes |
Inferenz reports under five minutes per determination, against 30 to 90 minutes of manual clinical review. In the example Inferenz uses, a 25-person intake team can properly review about 75 referrals a day, and some days bring 500. Run the numbers on your own volume.
What does the agent extract, and how transparent is the score?
By default it scores terminal prognosis, PPS, documented functional decline, hospitalization history over the past six months, and documentation completeness. Each criterion carries a weight, the agent totals the points, and it returns the factors behind the total. A clinician can see why a packet landed in Pending Review without reopening all 38 pages.
Can you set your own criteria, or are you stuck with vendor defaults?
The defaults are a starting point. Clinical staff edit the weights, thresholds, mandatory documents, and routing in plain English, and a change goes live when saved, with no developer ticket. That speed needs a guardrail: every edit should have a named owner and a date, so you can show which rules were live the day a patient was admitted.
What does the second workflow add?
Eligibility tells you who qualifies. A second workflow scores eligible referrals on their likelihood of becoming admissions, using your own history: diagnosis fit, referral source, geography, caregiver availability, and documentation completeness. The coordinator still decides, and the score runs only on referrals already marked eligible. Caregence sits above your existing systems as an orchestration layer on the Caregence platform, so there’s no migration.
| Dimension | Manual intake | Caregence (Inferenz-reported) |
| Time per determination | 30 to 90 minutes | Under 5 minutes |
| Scoring consistency | Varies by reviewer and by day | Same logic on every referral |
| Changing the criteria | IT ticket and a development cycle | Text edit, live on save |
| Prioritization | Intuition and whoever called last | Conversion probability with reasoning |
| Audit evidence | Reconstructed after the fact | Timestamped at every step |
 What audit trail does the agent leave for a reviewer?
Every workflow step is timestamped against the patient record: the inputs pulled, the logic applied, the score produced, the decision written, and the notification sent. That gives you one consistent record per referral and removes the reviewer-by-reviewer variance that audits penalize.
Push those determinations into your reporting layer too. An audit-ready dashboard connects each compliance number to the patient-level evidence behind it, and our guide to building audit-ready dashboards for CMS reviews shows how to wire that up. When a records request arrives, your team answers from one screen.
What should a COO or CIO ask before choosing a hospice eligibility AI?
Some hospice AI tools read well and still fail in practice. They misread ambiguous clinical language, or they apply the wrong standard for your jurisdiction. A 2026 PLOS Digital Health study shows the right habit. Researchers used self-hosted language models to extract prognostic indicators from the notes of 2,708 lung cancer and 814 colon cancer patients, then validated the extracted features against structured EHR data and physician annotations. The study covered oncology notes. Its method transfers to hospice packets; its accuracy figures don’t.
| Question to ask | What good looks like | Red flag |
| Who writes the eligibility criteria? | Your clinical leaders, in plain language, with change history | Vendor-locked rules; changes need a ticket |
| How does it handle LCD variation by MAC? | Criteria mapped to your MAC and diagnosis, with a named owner and update process | One national template |
| Can it explain every score? | Factor-level breakdown on each referral | A single opaque number |
| How is extraction accuracy measured? | Tested on a sample of your own packets against clinician-confirmed values | Demo accuracy only |
| Where does the human sit? | A person approves; borderline cases route to Pending Review | Auto-admits or auto-declines |
| What protects PHI? | BAA, retention terms in writing, minimum-necessary access, audit logs | Verbal assurances |
| How does it connect to our systems? | Triggers from portal, API, or webhook; writes status back; no migration | Requires replacing your portal |
| What audit evidence can you export? | Timestamped inputs, logic, score, and decision per referral | A summary report only |
On safeguards, ask for the business associate agreement and the data-retention terms in writing. Caregence’s platform design applies minimum-necessary access, role-based permissions, and audit logging across its agents, and your contract should spell out how that applies to your data.
How do you connect the agent to your EMR and recertification workflow?
The agent is portal-agnostic. A button click, a form submission, an API call, a webhook, or a scheduled run can trigger it, and the result is written back to the hospice system and portal record, so intake staff keep working in the tools they know. That makes EHR and referral data integration the real project. Check that your billing, EHR, and referral data agree on patient identity and dates before go-live.
Data readiness decides how well any of this works. Most hospice AI projects stall without it, and a missing admission date or a duplicated patient record turns into a wrong determination.
Recertification follows the same pattern. Scheduled runs are a documented trigger, so a nightly sweep of patients approaching a benefit-period boundary can flag a missing face-to-face attestation or an absent recertification narrative before the claim goes out. Confirm that scope during scoping, since the published workflow centers on referral screening.
How do you measure the return on automated eligibility checks?
Start with the Inferenz-reported figures and your own volume. At 75 referrals a day and 30 minutes per manual review, your clinicians spend 37.5 hours a day on first-pass review. If the agent returns each determination in under five minutes and a clinician only reviews the score and the flags, that burden shrinks to a fraction. Measure the fraction in your own pilot. Our guide to referral intake delays lists six baseline metrics worth capturing first.
- Referral-to-determination time: hours from packet arrival to status.
- First-pass completeness: share of packets with CTI, narrative, and election statement in order on day one.
- Reviewer variance: score spread when two clinicians review the same packets.
- Pending Review rate and time to clear: how many packets need a clinician and how fast.
- Denial and ADR outcomes: documentation-related findings per quarter.
- Referral-source rework: requests back to hospitals and SNFs for missing documents.
How do you pilot a hospice eligibility agent in 90 days?
- Days 1 to 15: Pull one week of past referrals with the decisions your team made. Write the scoring criteria in plain English with your clinical leads.
- Days 16 to 45: Run in shadow mode. Compare agent determinations with past decisions, and have two clinicians score the same packets to measure human variance.
- Days 46 to 75: Go live on one branch or service line, with a person approving every determination.
- Days 76 to 90: Review the metrics, tune weights, record who owns each rule, and decide on rollout.
A strong data layer speeds all four steps. A post-acute care provider that worked with Inferenz unified multiple EMRs, a triage platform, and a state HIE on one governed Snowflake warehouse with a master patient index, and leadership recovered two hours a day from manual spreadsheet audits (Inferenz-reported).
Final thoughts
Eligibility decisions carry the most weight in hospice. They decide who gets care, and they decide what survives a review. An agent can read every packet the same way, every time, and tell your team exactly what’s missing. It can’t replace the physician’s judgment, and it shouldn’t try. The hospices that get this right will write their own rules, keep a person on every determination, and keep the receipts.






