







Medallion Architecture Explained: Bronze, Silver, and Gold Layers for Healthcare Data

Summary

Medallion architecture sorts healthcare data into three progressively cleaner layers, bronze, silver, and gold, so a hospice or health system’s leadership team can trust the number behind every clinical, compliance, and financial decision. This guide breaks down what happens at each layer, where PHI de-identification belongs, and what a real build costs.

Introduction

Your length-of-stay number is probably wrong. Not fraudulently wrong!

Quietly wrong: pulled from three systems, patched by hand where the columns didn’t line up, rounded where nobody had time to check. It ends up in the board deck anyway. Ask where it actually came from and watch the room go quiet.

That’s the real failure hiding inside most hospice data stacks. It’s not that the data is missing. It’s that nobody can say with confidence which version of it is true.

Medallion architecture is the fix. Databricks, Microsoft Fabric, and Snowflake have all landed on it as their default recommendation, a layered bronze, silver, gold pattern that turns scattered EHR exports, claims files, and referral forms into one number a COO can actually defend, whether that’s in a board meeting or in front of a CMS reviewer.

What medallion architecture actually means

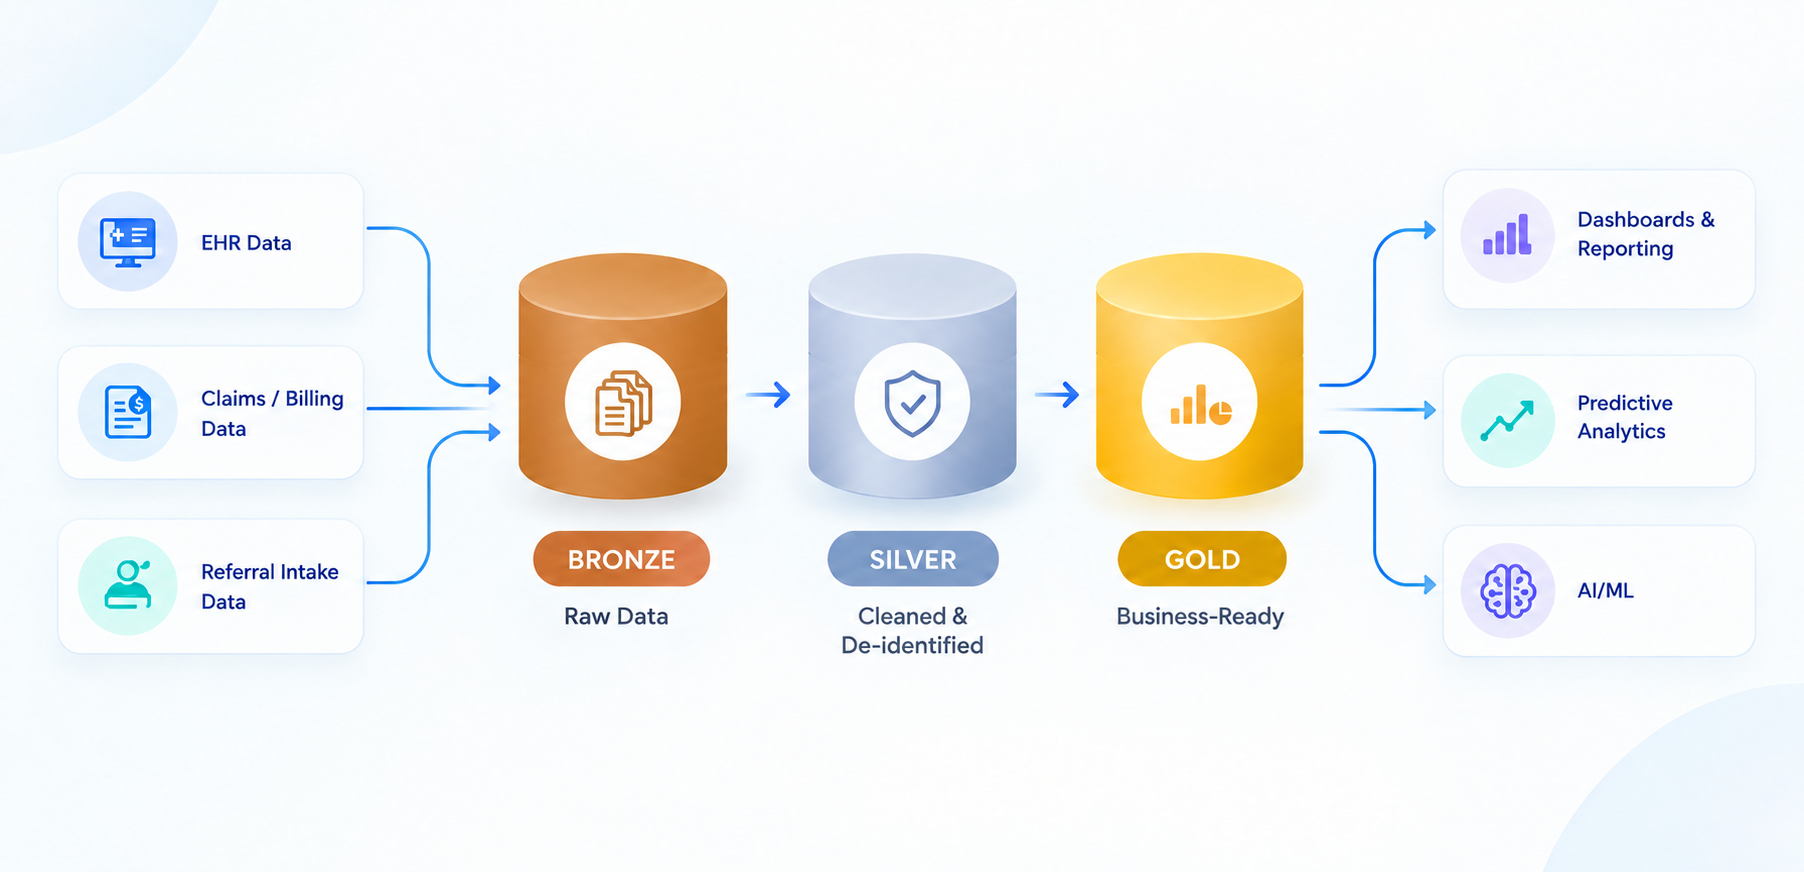
Medallion architecture organizes data into three layers, bronze, silver, and gold, where each layer represents a higher standard of trust than the one before it. Databricks popularized the pattern around 2019 as part of its data lakehouse approach. It’s since become the default design recommendation inside Microsoft Fabric’s OneLake and Snowflake’s dynamic tables, and that convergence across three competing vendors says something: this isn’t a one-vendor trend, it’s how the industry has settled on structuring data at scale.

The concept itself is simple, even when the engineering underneath isn’t. Raw data lands untouched. It gets cleaned and validated in a middle layer. It gets shaped into something a dashboard, a predictive model, or a CMS report can consume directly in the last layer. Each layer acts as a checkpoint, and a number doesn’t move forward until it clears the bar for that stage.

For a hospice organization pulling EHR records, claims data, referral intake forms, and HOPE assessment data out of a dozen disconnected systems, a familiar problem if you’ve read our breakdown of hospice EMR and referral data integration, medallion architecture is what turns that sprawl into one governed, explainable pipeline instead of a dozen separate one-off cleanup jobs.

Bronze, Silver, and Gold: what actually happens at each layer
Bronze, Silver, and Gold: what actually happens at each layer

Bronze: raw data, untouched

The bronze layer stores data exactly as it arrives, no cleanup, no validation, no reformatting. An EHR export lands here with its duplicate patient records still duplicated. A claims file lands here with its rejected line items still in it. Nothing gets fixed yet, and that’s deliberate.

Keeping an untouched copy means you always have a way to answer what the source system actually sent, without arguing about it later. If a downstream report looks wrong, bronze is where you go to check whether the error started upstream or got introduced during cleanup.

Silver: cleaned, validated, de-identified

This is where the real work happens. Silver takes the raw bronze data and applies the rules: drop the duplicate patient records, standardize date formats across systems that all format dates differently, reject line items that fail a validation check, and join related datasets, patient plus claims plus caregiver visit, for instance, into something coherent.

This is also, functionally, where PHI de-identification belongs in most healthcare medallion builds. The HHS Office for Civil Rights’ Safe Harbor guidance under 45 CFR 164.514(b) sets out 18 identifier categories that have to be removed or generalized before health data counts as de-identified.

Silver is the natural checkpoint for that removal, after raw data has been validated and joined, but before it reaches gold-layer tables that a wider set of analysts, vendors, or BI tools can query.

De-identification is one piece of a bigger picture. Access controls, retention policies, who’s allowed to query what, that’s a separate set of decisions worth its own conversation, which is why we’ve broken it out in our framework for data governance and CMS compliance for hospice care agencies.

Gold: business-ready, aggregated

Gold is what your COO actually looks at. Length-of-stay averages by team. HQRP compliance rates by facility. Referral-to-admission conversion by source. These are aggregated, curated tables built for a specific consumer, a dashboard, a predictive model, a CMS submission, not a general-purpose dump of everything the organization has ever collected.

The Databricks lakehouse documentation is explicit on this point: gold tables should be organized around named use cases with a clear owner, not treated as a shared catch-all for every possible metric. When two departments can’t agree on which gold table holds the real length-of-stay number, that’s usually a sign gold wasn’t scoped tightly enough to begin with.

Usually, that argument gets settled by tracing the number back through the pipeline, bronze to silver to gold, which is exactly what is built for: not just what a gold table says, but proof of how it got there.

Modernizing a Healthcare Data Platform from the Ground Up from bronze-to-gold?

Medallion Architecture vs. Data Mesh: Which One Do You Actually Need

Medallion architecture organizes data by quality stage, bronze to silver to gold. Data mesh organizes data by business domain, giving each team, clinical, billing, referrals, ownership of its own data products. They answer different questions, and for most single-organization hospice or home-based care networks, they’re not actually competing.

A mid-size hospice agency with one data team and a handful of source systems rarely needs the organizational overhead of a full data mesh: distinct domain teams, federated governance, a data product marketplace. Medallion architecture, applied inside a single governed platform, gets you a trustworthy, audit-ready gold layer without that overhead. Data mesh tends to earn its complexity at multi-facility health systems or larger networks, where a dozen departments are already fighting over who owns what data and no single team could realistically own a company-wide bronze-to-gold pipeline anyway.

Databricks, Microsoft Fabric, or Snowflake: How the Big Three Actually Differ
Databricks, Microsoft Fabric, or Snowflake: How the Big Three Actually Differ

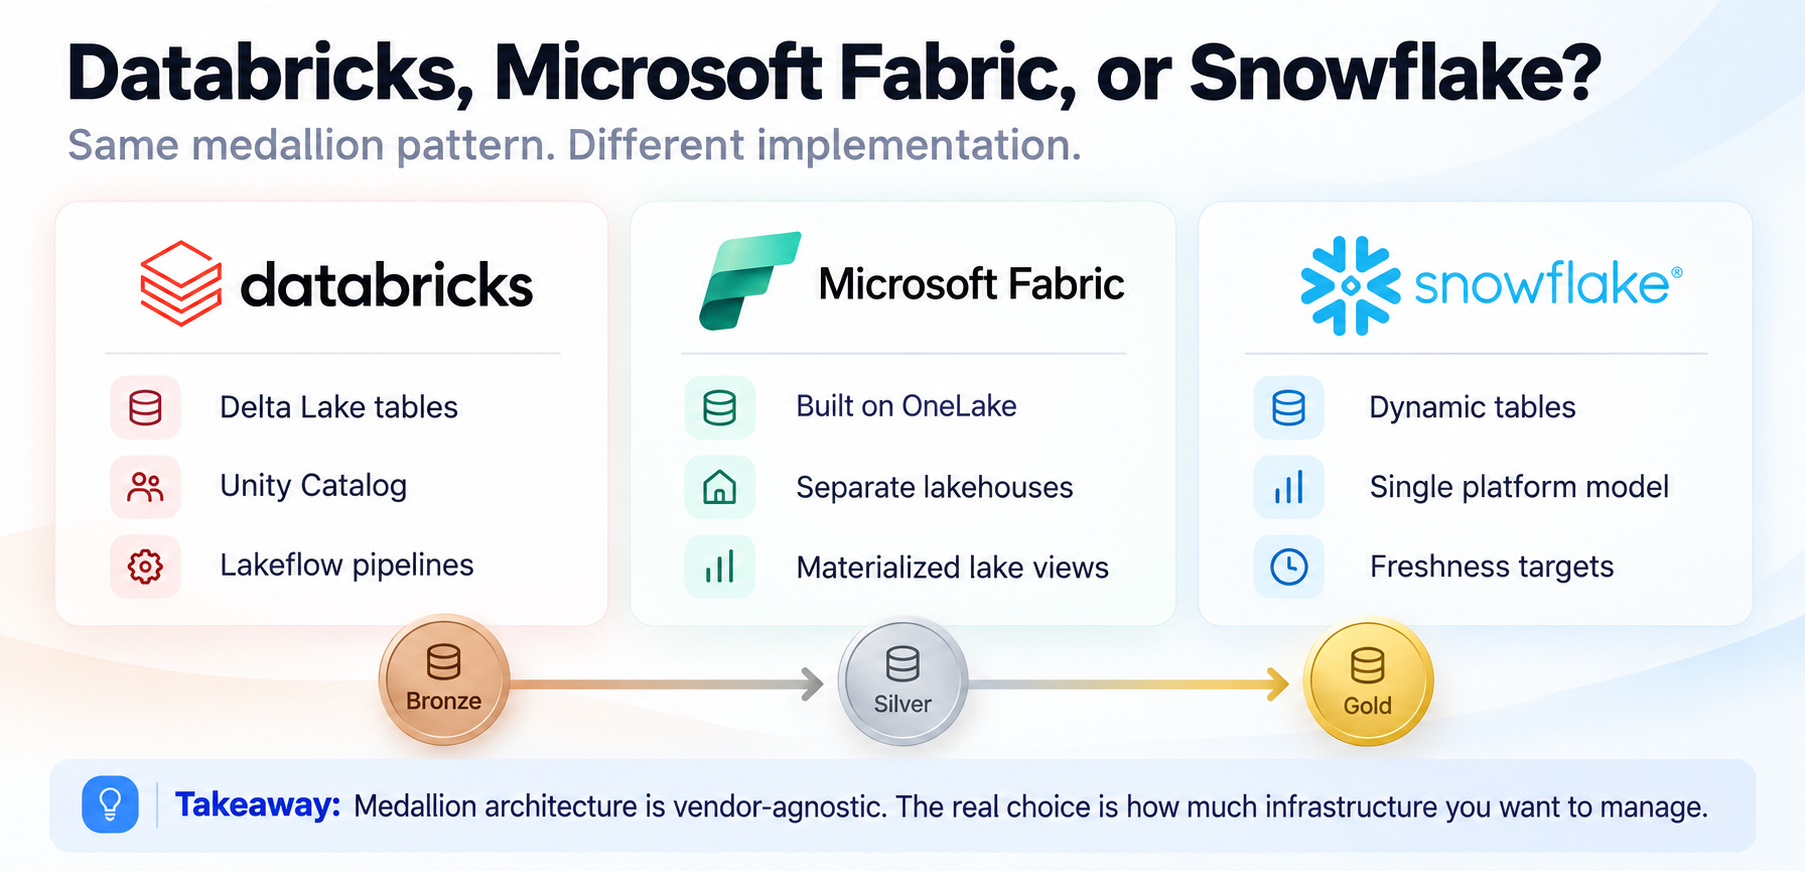
All three vendors now treat medallion architecture as a first-class, documented pattern, but the mechanics differ:

  • Databricks implements the layers as Delta Lake tables inside Unity Catalog, typically one schema per layer, and increasingly through Lakeflow’s declarative pipelines for the bronze-to-gold flow, per Databricks’ own lakehouse documentation.
  • Microsoft Fabric builds medallion directly on OneLake, its unified logical data lake, recommending either separate lakehouses per layer or materialized lake views for the silver-to-gold transformation, according to Microsoft’s own Fabric documentation.
  • Snowflake doesn’t require separate storage per layer. Its own documentation on dynamic table design patterns describes bronze as the raw landing table, silver as a cleaned dynamic table with a downstream-linked refresh target, and gold as an aggregated dynamic table with its own freshness goal, all inside one platform’s compute and governance model.

The practical takeaway for a hospice CIO evaluating platforms: the medallion pattern itself is vendor-agnostic. What changes is how much infrastructure you manage directly versus how much a managed service handles for you, and that’s a platform decision worth making with your data engineering partner, not one the architecture pattern forces on you.

What This Actually Costs: Team, Timeline, and Budget

A realistic bronze-to-gold build for a mid-size hospice care agencies typically needs a small dedicated team, one to three data engineers depending on source system count, plus a part-time data architect for the first phase, and runs for some weeks for an initial working pipeline covering your highest-priority source systems: EHR, billing, referral intake. Full coverage across every legacy system usually extends past that, as acquisitions and edge cases get absorbed.

That tracks with what we’ve seen in practice. Our work building an enterprise data platform from the ground up for a post-acute care organization unified EMRs, a patient triaging platform, the state HIE, and HR data into one governed warehouse, architected specifically so new EMRs, service lines, or acquired entities can onboard without rebuilding the foundation each time. The project shipped in a fraction of its planned 18-month timeline.

The heavy lift is building that foundation once. After that, onboarding a new source system becomes a repeatable process instead of a custom project.

Cost scales with source system count and data volume more than with the architecture pattern itself. Medallion architecture doesn’t inherently cost more than an ad hoc pipeline. It just makes the cost visible and predictable instead of hidden inside a dozen one-off scripts nobody understands months later.

Is Medallion Architecture Still Relevant in 2026?

The medallion pattern remains the default, not a close call. Databricks recommends it natively, Microsoft Fabric calls it the recommended design approach, and Snowflake has built native tooling around the same three-layer vocabulary in its own documentation.

At nearly six years old, it’s mature enough that the real question has shifted from whether to use it to how to enforce layer boundaries so gold doesn’t become a dumping ground, which for a healthcare organization sitting on scattered EHR, claims, and referral data is reason to adopt it now, not wait for a replacement that isn’t coming. And gold doesn’t just sit there for reporting: it’s what feeds the length-of-stay models, staffing projections, and capacity planning that become forecasts leadership can defend, not a hunch dressed up in a spreadsheet.

Building This on a Foundation That’s Actually CMS-Ready

None of this works in isolation. A gold layer is only as trustworthy as what’s holding it up, and that’s the full picture we walk through in our guide to building a CMS-ready hospice data foundation. Medallion architecture gives you the layers. That guide is where the rest of the foundation lives.


Starting with data modernization or evaluating your first medallion build? Our team can walk you through.

Frequently Asked Questions

Meta Muse Spark in Healthcare – What it Means for Clinical AI and Compliance

Executive Summary

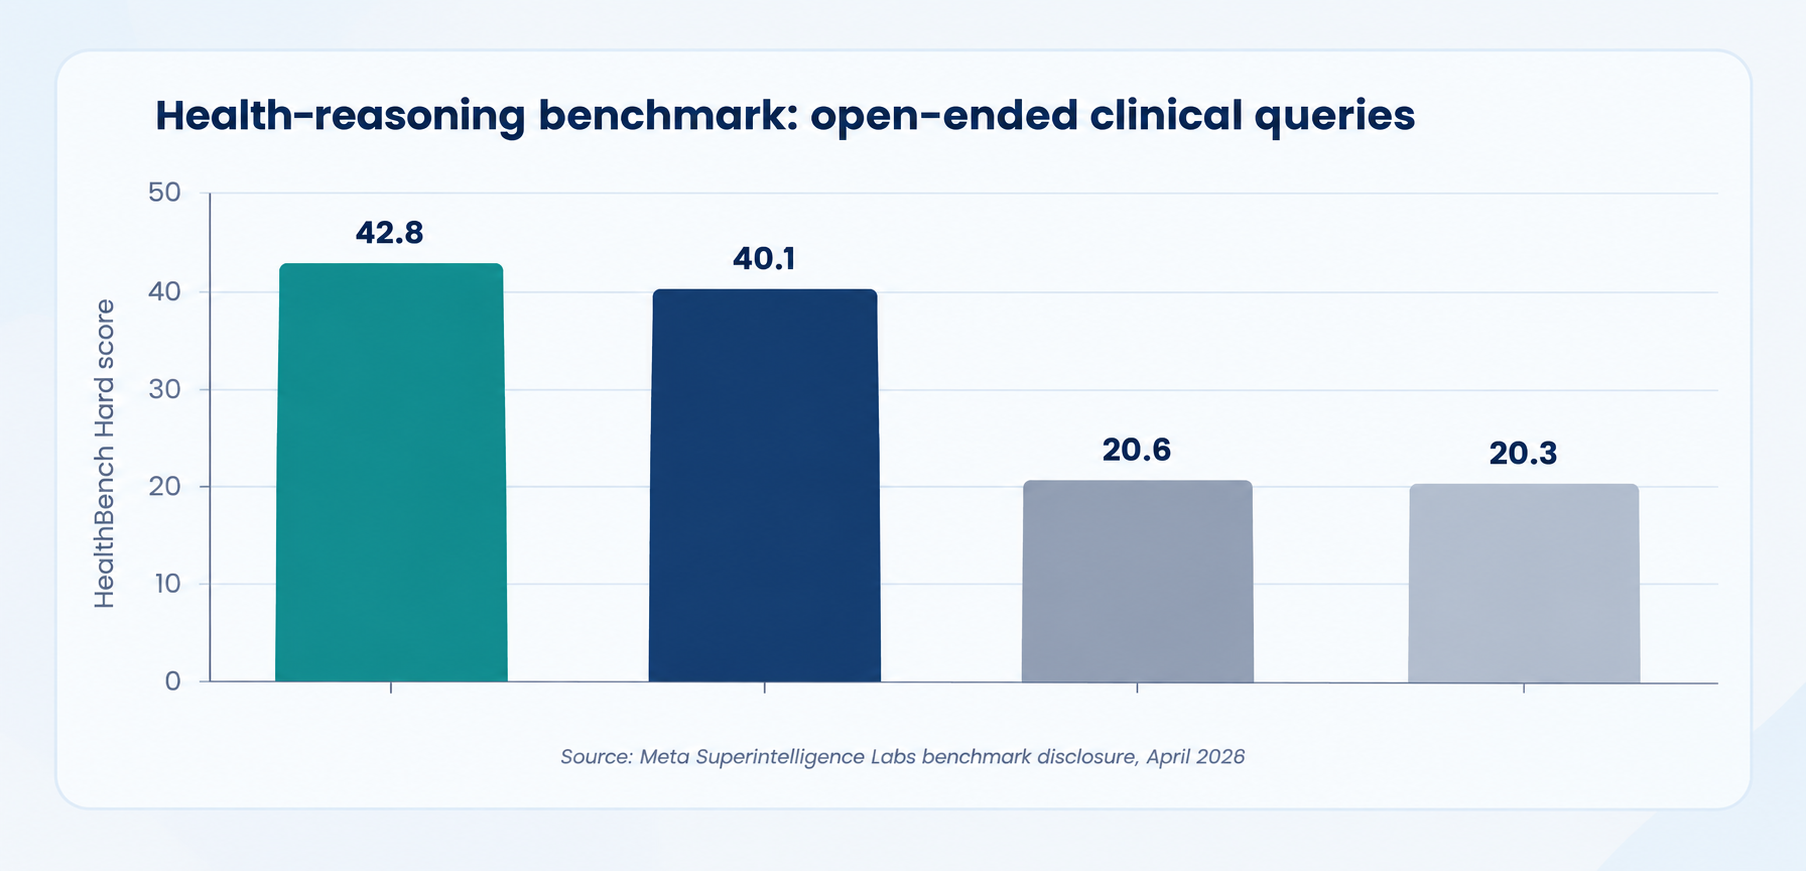
Meta entered consumer health AI on April 8, 2026, with the launch of Muse Spark, the first model to come out of its newly formed Meta Superintelligence Labs. It isn’t a healthcare product in any enterprise sense. It’s a general-purpose assistant, folded into Facebook, Instagram, WhatsApp, Messenger, and Ray-Ban Meta glasses, that happens to be unusually good at answering health questions. Meta says it worked with over 1,000 physicians to curate the health-reasoning training data. Independent benchmarks back that claim: Muse Spark scores 42.8 on HealthBench Hard, ahead of GPT-5.4 (40.1), Gemini 3.1 Pro (20.6), and Grok 4.2 (20.3). 

What is Muse Spark?

Meta describes Muse Spark as “small and fast by design, yet capable enough to reason through complex questions in science, math, and health.” It’s proprietary: no open weights, unlike the Llama line it replaces as Meta’s flagship effort. It ships with three interaction modes. Instant handles quick answers. Thinking works through multi-step reasoning. Contemplating orchestrates multiple agents in parallel for the harder problems, Meta’s answer to Gemini Deep Think and GPT Pro.

  • Built by Meta Superintelligence Labs, formed after Zuckerberg’s reported dissatisfaction with Llama 4’s progress and led by former Scale AI CEO Alexandr Wang, following a $14.3B investment for a 49% stake in Scale AI. 
  • Rolling out across the Meta AI app, web, WhatsApp, Instagram, Facebook, Messenger, and Ray-Ban Meta AI glasses, which means multimodal, “see what I see” health queries are a real near-term use case, not a roadmap slide. 
  • Free to use, with rate limits, and offered via private-preview API to select partners: a distribution strategy, not a licensing one. 

I personally believe that Meta isn’t trying to build a HIPAA-compliant AI. It’s trying to make the Meta AI app the place a billion people ask their first health question. That alone resets what people expect from every other health AI product, long before Meta ever touches an enterprise or provider workflow. Caregence by Inferenz on the other hand, helps build healthcare-specific autonomous AI agents on a HIPAA-compliant platform. 

Muse Spark’s HealthBench Hard score leads the frontier consumer-model field, per Meta’s own launch disclosure.

Use Cases This Opens Up

Consumer-facing

  • First-line health Q&A at massive scale, inside apps people already open dozens of times a day, which removes the step of seeking out a dedicated health app. 
  • Multimodal symptom and visual triage via Ray-Ban Meta glasses: “what is this rash,” “read this medication label,” “what does this lab report say,” using camera-based context instead of typed description. 
  • Biometric and lab-trend visualization. Muse Spark actively prompts users to “paste your numbers” (glucose, blood pressure, lab panels) so it can chart trends over time. 
  • Pre-visit preparation: drafting questions for a doctor, plain-language explanations of a diagnosis or procedure, digital patient engagement, medication interaction lookups. 

Where it does not extend (today)

  • No clinician-facing workflow: no EHR integration, no charting, no order entry. This is a consumer assistant, not a Dragon Copilot or Cortex Agents competitor. 
  • No regulatory clearance. Meta makes no FDA claims, and none of the frontier consumer models, Muse Spark included, are cleared as diagnostic tools. 
  • No enterprise or provider-side product announced. Unlike Google’s Med-Gemini via Cloud Healthcare API or Anthropic’s Claude for Life Sciences, there’s no B2B healthcare offering attached to Muse Spark today. 

See how Caregence™ scopes HIPAA compliance into every layer of the platform, not just a policy footnote

Compliance: The Part That Should Concern Healthcare Leaders

This is the section that matters most if you’re building compliance-first healthcare AI. Muse Spark’s health capability is arriving inside a company with an unresolved, material healthcare-privacy track record, and the model inherits that posture by default. 

The regulatory gap

  • Meta is not a HIPAA-covered entity, and Muse Spark carries no Business Associate Agreement. Clinicians interviewed by WIRED were blunt about it: handing clinical details to the tool is a genuine data-handling risk, not a theoretical one. 
  • Meta’s generative-AI policy allows chat data to be retained for training and to influence advertising. That’s the opposite of the data-isolation guarantee enterprise health platforms are expected to provide. 

 WHY IT MATTERS 

Every credible enterprise health AI vendor scopes HIPAA eligibility to a specific, contractually governed product tier. Muse Spark, as shipped today, has no such tier. It’s the free consumer assistant. Full stop. 

Recent history that makes this scrutiny warranted

Meta faces ongoing litigation over the Meta Pixel lawsuit allegedly transmitting protected health information (appointment scheduling, medical conditions, provider names) from hospital patient portals back to Facebook, without valid HIPAA authorization or a BAA in place with the hospitals involved. 

That exposure hasn’t cooled off. Through mid-2026, HIPAA Journal tracked a fresh wave of hospital settlements tied to pixel-based tracking tools, including an $800,000 settlement fund at Concord Hospital Health System, with plaintiffs’ firms now reaching smaller providers and specialty clinics rather than only the largest health systems. 

Independent testing by WIRED in April 2026 found that Muse Spark actively solicits raw lab and biometric data, and in at least one documented case produced clinically dangerous guidance: a near-starvation meal plan in response to an extreme-fasting prompt.

Muse Spark stands alone among major health-capable AI platforms in lacking a HIPAA-eligible, BAA-backed tier.

Where the rest of the market stands, for contrast

  • Claude and GPT-5.x/GPT-6 Astra: HIPAA-eligible under a signed BAA on enterprise and API tiers. PHI handling is a contractual, auditable commitment, not a policy footnote. 
  • Google Cloud Healthcare API (Med-Gemini) and Microsoft’s enterprise Copilot and Dragon Copilot tiers follow the same pattern: HIPAA eligibility is scoped to specific, governed enterprise products, never the free consumer assistant. 
  • MedGemma (Google, open weights) sidesteps the BAA question entirely by supporting fully on-premise, self-hosted deployment. No PHI ever leaves the customer’s environment. 

The pattern across every credible healthcare AI vendor is the same. Compliance is a property of a specific, contractually governed product tier, never the free consumer chatbot. Muse Spark, as shipped, sits entirely outside that boundary. And that’s not a gap Meta is likely to close quickly. Closing it would mean re-architecting the data handling, advertising, and identity systems that its entire consumer business model runs on. 

Competitive Landscape 

Platform Health strength HIPAA / BAA Primary audience 
Meta Muse Spark Strong on HealthBench Hard (42.8); trained with 1,000+ physicians Not HIPAA-eligible; consumer product, ad-linked data policy Consumers, via Meta apps & glasses 
Claude (Opus/Sonnet) Leads HealthBench Professional; strong calibration & uncertainty handling HIPAA-eligible with BAA on API/Enterprise; life-sciences MCP connectors Enterprises, providers, life sciences 
GPT-5.x / GPT-6 Astra Competitive HealthBench scores; large context for longitudinal records HIPAA-eligible via Azure OpenAI / enterprise tiers with BAA Enterprises, ambient scribing, developers 
Google Gemini / MedGemma Strong multimodal imaging; MedGemma open weights for on-prem builds Cloud Healthcare API HIPAA-eligible; MedGemma self-hosted, no BAA needed Developers, imaging, cloud-native health teams 
Microsoft Copilot / Dragon Copilot Deep clinical documentation heritage; large deployed scribe base HIPAA-eligible enterprise tiers; six-figure enterprise commitments typical Health systems, ambient documentation 
OpenEvidence Most-used LLM tool among physicians surveyed (HOMERuN) Purpose-built for clinicians; evidence-citation model Practicing physicians 

 Here’s the honest read. Muse Spark is benchmark-competitive on health reasoning, but it’s playing in a different lane than the enterprise and clinical AI market. It isn’t displacing OpenEvidence among physicians, Dragon Copilot inside health systems, or Claude and GPT-6 Astra in provider-facing platforms. It’s competing with WebMD, Google search, and asking a friend, just at a scale none of those can match. 

How This Shapes Healthcare Going Forward

The upside

  • Genuine democratization of first-line health information for populations with limited access to care. That’s a real, non-trivial public-health benefit, if the guardrails hold. 
  • Competitive pressure on Google, OpenAI, and Microsoft to keep improving consumer-facing health reasoning, which raises the baseline quality of free health information across the board. 
  • Multimodal, wearable-based health interaction through smart glasses becomes mainstream faster than it otherwise would have. This is a genuinely new interaction pattern, not an incremental one. 

The risk

  • A consumer AI with no HIPAA obligation, ad-linked data retention, and a documented history of soliciting sensitive health data at massive scale is a regulatory incident waiting to happen. Regulators (HHS/OCR, state attorneys general, EU regulators) are already primed by the Pixel litigation to scrutinize Meta’s health-data practices specifically. 
  • Clinically dangerous outputs at consumer scale, like the extreme-fasting example, create real patient-safety exposure well before any enterprise deployment. This is happening in production, today, to real users. 
  • The blurring of “consumer wellness chat” and “medical advice” in the public’s mind makes it harder for patients to tell a compliant, provider-sanctioned AI tool apart from a free assistant with no clinical accountability. That’s a trust problem the entire industry inherits, not just Meta. 

 The tension 

Muse Spark proves a consumer AI can be genuinely good at health reasoning. It also proves, through its own vendor’s litigation history, that being good at health reasoning and being safe to trust with health data are two completely separate engineering and governance problems. 

Bottom Line

Muse Spark is a serious model with real health-reasoning capability, built by a company with a real health-privacy problem it hasn’t resolved. Its near-term impact on the broader healthcare AI market is indirect but significant.  

The platforms that win the next phase of healthcare AI won’t be the ones that simply reach the most users first. They’ll be the ones that pair Muse Spark-level reasoning with a signed BAA, an auditable data trail, and a governance model built for PHI from day one. 

Muse Spark raises consumer expectations for what a health-aware assistant should feel like, and it sharpens the public compliance conversation by giving regulators and patients a concrete, litigated example of what “not HIPAA-eligible” actually costs.  

Building healthcare AI that has to be both clinically capable and provably compliant?

Frequently Asked Questions 

Hospice EMR and Referral Data Integration: Connecting EHR, Billing, and CMS Reporting Effectively

Summary

Most hospice care agencies don’t have a software problem. They have a data problem: EMR, billing, referral intake, and CMS reporting running as separate islands that staff bridge by hand. Here’s how to connect them with a real data integration layer, not a system replacement. 

Introduction

Every hospice CIO we’ve talked to this year has heard some version of the same pitch: rip out the old EMR, move everything to a shiny new platform, and the integration headaches disappear. They don’t. They just move to the new system, along with a nine-to-eighteen-month migration, a retrained staff, and a fresh set of interfaces you still must build from scratch. 

The actual fix is less dramatic and considerably cheaper. It’s connecting the systems you already have, EMR, billing, referral intake, and CMS reporting, so data moves between them automatically. That’s integration, not replacement, and for most agencies it closes the real gap faster than a rebuild ever would. 

The False Choice Between “Replace It” and “Live With It”

Ask a hospice COO how their EMR talks to their billing system and you’ll usually get one of two answers: “it doesn’t, someone keys it in twice,” or “we’re planning to switch platforms next year.” Both answers assume data integration itself is off the table and it’s the same for those trying to implement AI-powered solutions too. 

It isn’t. A hospice EMR, a billing system, and CMS’s iQIES submission system are all built to exchange discrete data, not just PDFs and faxes. The gap is almost always in the interface layer sitting between them, not in the core platforms themselves. Data integration services can help fix that layer, allowing the systems your staff already trust to start behaving like one connected environment instead of three separate ones someone must reconcile by hand. 

What a Bidirectional Hospice EMR Interface Actually Means

A bidirectional interface reads and writes data in both directions, close to real time. Update a medication order in the EMR and it shows up in the pharmacy system. Post a payment in billing and the EMR’s financial record updates on its own. 

That’s different from what a lot of vendors call “integration.” Plenty of connections only push data one way, usually EMR to a reporting tool, built for a compliance export. That’s a data feed, not an interface. It solves reporting. It does nothing for the daily double entry that eats staff time and introduces the transcription errors that later show up as billing denials. 

If you’re evaluating a vendor’s integration claim, ask directly: does data flow both directions through an API or HL7 interface, and does a change in System A show up in System B without a manual export step? “We can run a report” is not a bidirectional interface. 

We took a post-acute care organization from 32 disconnected source systems to one governed enterprise data platform.

The hospital-based hospice problem: when Epic or Cerner isn’t enough

Hospital-owned hospice teams run into a version of this problem free-standing agencies don’t. The hospital runs Epic or Oracle Health (formerly Cerner) for acute care. The hospice program runs a separate, certified hospice EMR, because HOPE, HQRP measures, and hospice-specific billing rules aren’t things a generalist acute-care platform is built to handle. 

That split creates a real documentation gap. A patient admitted to the hospital, then transferred to hospice care, generates ADT (admission, discharge, transfer) data in the hospital system that the hospice EMR needs and often doesn’t get automatically. Clinicians end up re-entering demographics, medication history, and diagnosis data that already exists two systems away. 

The fix isn’t asking the hospital to abandon Epic or asking the hospice program to give up a purpose-built hospice EMR for a generalist one. It’s building the ADT feed and clinical data exchange between them, so admission data lands in the hospice record the moment a transfer happens, not two days later when someone notices it’s missing. 

Closing the loop on billing and CMS reporting

CMS has been layering new data requirements onto existing hospice systems for over a decade, not requiring providers to replace them.  

Change Request 8358, issued in 2013 and effective in 2014, added general inpatient visit reporting, facility NPI numbers, post-mortem visit data, and infusion drug reporting directly onto existing hospice claims. Agencies didn’t swap systems. They added the data fields their claims software needed. 

That pattern hasn’t stopped. Starting April 1, 2026, CMS instructed Medicare Administrative Contractors to compare primary diagnosis codes on hospital claims against hospice claims for the same beneficiary, denying hospital claims that overlap with hospice-covered services. A second edit, effective April 6, 2026, rejects long-term hospice claims where the admission date and the billing “from” date match in a way that bypasses CMS’s length-of-stay checks. 

Both edits mean the same thing operationally: your billing data and your clinical documentation now have to agree, because CMS is actively cross-checking them against data from other providers. That’s a revenue cycle synchronization problem, not a “need a new EMR” problem, and it’s exactly what a properly built billing interface solves. 

There’s one more compliance wrinkle worth naming here: election statements and revocations need an audit trail that survives the trip between systems. If a patient revokes hospice election and that status doesn’t update everywhere at once, EMR, billing, and referral records can disagree about a patient’s current status, which is precisely the kind of mismatch CMS’s newer claims edits are built to catch. A real data integration layer keeps that status synchronized from one source of truth, not three. 

The same logic applies to HOPE and iQIES. CMS requires a 90% HOPE submission rate to avoid a 4% Medicare payment reduction, and iQIES has been the only accepted submission channel since HIS was fully retired on February 16, 2026.  

We cover the full HOPE and HQRP compliance mechanics in our guide to building a CMS-ready hospice data foundation, but the integration point that matters here is simpler: your EMR needs a clean, automated path into iQIES, not a manual export someone remembers to run before the deadline. 

Referral data without fragmenting HOPE records 

Referral intake is usually the first place integration breaks down in hospice care agencies. A referral arrives by fax, portal, or email, gets keyed into the EMR as a new patient record, and later turns out to duplicate a record already created through a different intake path. Now there are two partial records instead of one complete one, and HOPE data collected against either is incomplete. 

The fix is structural: referral and eligibility tools need to write into the same admission workflow the EMR already uses, not create a parallel record that gets reconciled after the fact. If referral intake delays are the bigger issue for your team right now, we’ve covered automated eligibility screening separately, but from a pure data-integrity standpoint, the goal here is one patient, one record, from the first referral touch through HOPE-Discharge.

https://inferenz.ai/blogs/why-most-hospice-ai-projects-fail-without-data-readiness/ The systems nobody plans for: Pharmacy and DME

Most integration conversations start and stop at EMR-to-billing. Pharmacy and durable medical equipment (DME) interfaces get left for later, and “later” usually means someone is still calling in medication orders and faxing DME requests while everything else runs automatically. 

That’s a real gap, not a minor one. Medication and equipment data feed directly into the same CMS quality measures and billing codes as clinical documentation. An EMR that talks to billing and iQIES but not to your pharmacy interface is still generating manual work and still creating room for the kind of data mismatch that trips CMS’s newer billing edits. 

Middleware, HIE, and TEFCA: the case against point-to-point

There are two ways to connect multiple systems. You can build a direct, point-to-point interface between every pair of systems that need to talk, which works fine until you add a fifth or sixth system and the number of connections you’re maintaining grows faster than your team can support it. Or you can connect through a middleware layer or a health information exchange (HIE) once, and let that hub route data everywhere else. 

The second approach has real momentum behind it now. The Trusted Exchange Framework and Common Agreement (TEFCA), the federal government’s national interoperability framework, moved roughly 10 million documents in the year before 2025, and 464 million by the end of that year, according to data published by ASTP/ONC. Healthcare trade coverage in early 2026 puts that figure at nearly 500 million records exchanged through TEFCA’s Qualified Health Information Networks (QHINs), overseen by the Recognized Coordinating Entity. 

For a hospice team connecting to a hospital system, a referral partner, and a payer all at once, joining an HIE or a QHIN through one connection beats building and maintaining three or four separate point-to-point interfaces by hand. 

What integration actually costs, versus replacement

A scoped interface project, connecting your EMR to billing and to iQIES, typically runs six to twelve weeks with no clinical downtime, because you aren’t touching the system staff already know how to use. A full EMR replacement runs closer to nine to eighteen months once you account for vendor selection, data migration, staff retraining, and the inevitable stretch of running two systems in parallel during cutover. 

The dollar comparison usually favors integration too, but disruption cost is where replacement really loses. A mid-size agency mid-migration is an agency with a higher error rate, a support ticket backlog, and clinicians filling out paper workarounds “just until the new system settles.” None of that shows up on a vendor’s price sheet. 

The questions that separate real integration from a reporting export 

Before signing with an integration vendor, or asking your current EMR vendor what they can actually deliver, four questions cut through most of the marketing. 

  1. Does data move both directions, automatically, without a manual export step? 
  2. Does the connection update in near real time, or only on a batch schedule someone has to remember to trigger? 
  3. Does it cover clinical, billing, and CMS reporting data, or just one of the three? 
  4. And can you see a working example with another hospice agency, not a hospital system, since hospice data requirements are specific enough that generalist healthcare integrations don’t automatically transfer over?

If you’re comparing what platforms like WellSky, Axxess, or HospiceSoft actually support natively versus what needs a third-party interface, we’ve broken that down separately. But any vendor conversation should start with those four questions, regardless of which platform you’re running today. 

Get a straight answer on what's fixable through data integration and what genuinely isn't, from our experts.

Frequently Asked Questions 

From Insight to Action: Why Dashboards Alone Don’t Reduce Length of Stay

Summary

Hospital dashboards make a problem visible, but visibility alone rarely explains why dashboards alone don’t reduce length of stay on their own. The hospitals actually shortening stays pair dashboards with workflow automation that assigns ownership, escalates unresolved barriers, and closes the loop between insight and intervention, turning a stuck discharge into a solved one instead of a well-documented one. 

Introduction 

Most hospitals have already solved the visibility problem. Bed boards, discharge-readiness screens, and command center displays show exactly where every patient stands at any given moment, and that data is usually accurate. What most hospitals haven’t solved is the follow-through.  

Six in ten hospital finance leaders are increasing investment in analytics and data-based insights this year, even as margins stay under pressure, and the honest question few of those budgets answer up front is what happens after the insight arrives. That gap, not a lack of visibility, is the real reason so many hospitals have invested heavily in analytics and still can’t move average length of stay. 
A patient flagged as discharge-ready at 9 a.m. and still occupying that bed at 4 p.m. isn’t proof the dashboard failed. It’s proof the dashboard did exactly what it was built to do: display the problem accurately, for seven straight hours, while nothing downstream was designed to act on it. Visibility and action are two different capabilities. Most hospital analytics investment still stops at the first one. 

That distinction sits at the center of the broader capacity problem hospitals are now under pressure to solve. The Hospital Throughput Crisis: How COOs Are Using AI to Cut Length of Stay and Discharge Delays laid out what that crisis costs in dollars and beds. This piece picks up the question that tends to land in a COO’s inbox next: the dashboard is already in place, so why hasn’t length of stay actually moved?

Visibility is not the same thing as action 

Ask a nurse manager whether she can see which patients are ready for discharge, and she’ll say yes, usually within seconds. Ask whether those patients actually left the building on time, and the answer gets longer. 

That gap is the whole story. A dashboard tells you what’s true right now: which beds are occupied, which patients are pending discharge, which labs are still outstanding. It’s a mirror. It shows the room exactly as it is. What it doesn’t do, on its own, is walk into the room and fix anything. 

Most hospital dashboard limitations trace back to a single design assumption: that a person with enough context will see the flag and act on it, every time, without being told twice. On a unit covering twenty patients with three case managers, that assumption breaks by mid-morning. The flag stays lit. The bed stays occupied. And the dashboard, doing its job faithfully, keeps reporting a problem nobody’s chasing anymore. 

The difference matters enough to earn its own vocabulary: data visibility vs data action. Visibility is what a dashboard sells. Action is what actually shortens a stay, and action needs an owner, a deadline, and an escalation path for when the owner doesn’t respond, none of which live inside a chart.

What the evidence actually shows about dashboards and Length of Stay 

Published research on hospital dashboards is more mixed than most vendor pitch decks let on. A 2026 peer-reviewed evidence on capacity command centers that were heterogeneous revealed that implementations pairing real-time dashboards with predictive tools and colocated teams report gains in boarding, transfers, and usable capacity, but the study designs are largely observational and rarely isolate which piece, the data, the team, or the escalation authority, actually drove the result. The strongest data point: a 2026 study across seven hospitals and 283,000 discharges tied shorter length of stay to process and ownership changes, not the dashboard alone. 

That nuance matters for a plain reason: the dashboard was never the whole intervention. In nearly every published success story, the screen sat inside a larger system that also included standard work, named escalation authority, and a team empowered to act on what the data showed. Strip out those three things and keep only the screen, and the healthcare dashboard ROI evidence gets thin fast. 

A patient is typically flagged as long stay once their days in-house exceed the geometric mean length of stay, or GMLOS, for their diagnosis-related group, the same benchmark hospital command centers already track for excess bed days. Dashboards are excellent at counting those days. They’re far less reliable at reducing them unless something downstream is built to act on the count, not just display it. 

Why dashboards stall: fatigue and the ownership gap 

Dashboard fatigue hospitals report looks a lot like the boy who cried wolf. Add enough real-time flags to one screen, sepsis risk, fall risk, discharge readiness, denial risk, readmission risk, and staff stop scanning for the ones that matter. They scan for the ones they’ve learned they can safely ignore, because ignoring most of them has never caused a problem before. 

Why Hospital Dashboard Adoption Stalls 

Root Cause What It Looks Like on the Floor 
No named owner The flag is visible to six roles and truly owned by none of them 
No escalation path A missed flag sits there until someone happens to notice, sometimes a full shift later 
No feedback loop Staff never learn whether acting on a flag changed anything, so it stops feeling worth acting on 

A genuine dashboard adoption failure hospital leadership can point to almost always traces back to one of those three gaps, not to the underlying data being wrong. The data is usually fine. What’s missing is the operational discipline that turns a correct flag into a resolved one, which is a change management problem wearing a technology costume. 

Descriptive, predictive, and prescriptive analytics: where most hospitals get stuck? 

Most hospital dashboards operate at exactly one analytical altitude: descriptive. They tell you what happened, or what’s happening right now. A smaller number add predictive analytics, forecasting which patients are likely to drift past their expected discharge date. Very few reach the third level, prescriptive, where the system doesn’t just predict a problem but recommends, or triggers, the specific next action to prevent it. 

Descriptive vs. Predictive vs. Prescriptive Analytics in Healthcare 

Analytics Type Answers This Question Hospital Example Acts Without a Human? 
Descriptive What is happening right now? Bed board showing current occupancy No 
Predictive What’s likely to happen next? Model flagging a discharge likely to slip past GMLOS No 
Prescriptive What should happen next, and who should do it? Barrier auto-routed to the case manager, escalated if unresolved in 2 hours Yes, within guardrails 

This is the real distinction behind prescriptive vs descriptive analytics healthcare debates, and it’s also where most hospital analytics budgets are still concentrated in the wrong place. Descriptive dashboards are mature, inexpensive, and everywhere. Prescriptive tools that close the loop are rarer, and they’re the layer that actually correlates with shorter stays in the deployments reporting real gains.

From insight to action: what a closed-loop workflow actually looks like 

From insight to action healthcare teams keep describing as the missing step usually comes down to four mechanics, in order: detect, route, escalate, confirm. 

Detect means the system identifies a discharge barrier the moment it appears, an unsigned form, a transport slot never booked, a family member who hasn’t called back, not the next time someone happens to check a report. Route means that barrier goes straight to whoever owns it, automatically, without a phone call or an email someone has to remember to send. Escalate means if that owner doesn’t act within a defined window, the system moves it up the chain on its own. Confirm means the loop closes only once the barrier is actually resolved, not when someone marks it acknowledged. 

That’s what a genuine closed-loop workflow healthcare AI platform does that a dashboard, by design, does not. The dashboard stops at detect. Everything after that, the part that actually shortens a stay, has historically depended on a person remembering to keep chasing it across a twelve-hour shift. Building workflow-embedded analytics that handle steps two through four is a bigger engineering lift than adding another chart, which is exactly why most hospitals still haven’t done it. 

Map your discharge barriers against 90 days of your data, before committing to a bigger command center layer.

Command center or a bigger dashboard suite? A decision framework 

When length of stay isn’t moving, the instinct is often to add more visibility: another dashboard, another KPI tile, another weekly report. That instinct usually makes the fatigue problem worse, not better, because it multiplies the number of things staff are expected to notice without adding anyone to act on them. 

Dashboard Summary: Expanding the Suite vs. a Command Center Model 

Dimension Expanding the Dashboard Suite Investing in a Command Center Model 
What it adds More views of the same underlying data An operating layer that routes, escalates, and tracks resolution 
Who benefits Whoever remembers to check the screen Whoever owns the barrier, whether they’re looking or not 
Typical outcome More reporting, similar length of stay Fewer bed days lost to nonclinical delay, tracked directly 
Implementation lift Low, mostly configuration Higher, needs defined ownership and escalation rules across departments 

Neither path is automatically wrong. A hospital with genuinely poor real-time visibility needs better dashboards first; you can’t route a barrier you can’t see. But for hospitals that already have solid healthcare dashboards and healthcare analytics dashboard coverage and are still watching length of stay sit flat, the honest next investment is usually beyond dashboards patient flow work: the command center layer, not another chart.

Assigning ownership: who’s accountable when a discharge barrier is flagged? 

Ownership is the piece most hospitals skip, because it’s organizationally awkward, not technically hard. A discharge barrier can touch case management, nursing, pharmacy, transport, environmental services, and the family, all in the same afternoon, and if the escalation rule doesn’t name exactly one accountable role per barrier type, the flag becomes everyone’s problem and therefore no one’s. 

The hospitals that get this right usually build a simple ownership map before they buy any software: who owns a pending insurance authorization, who owns an unbooked transport slot, who owns a family member who hasn’t returned a call. That last one deserves attention on its own, because questions about who engages with patients in inpatient for discharge process often expose the real bottleneck. It’s frequently not clinical staff at all. It’s whoever is responsible for reaching the family, confirming the post-acute placement, and closing the communication loop, and in a lot of hospitals, nobody owns that step explicitly. 

That’s also part of why patient engagement is important to this entire conversation: a discharge plan the patient and family don’t understand or haven’t agreed to is a discharge that stalls, no matter how strong the underlying patient engagement solutions or predictive model is. Ownership has to include the patient’s side of the conversation, not just the internal handoffs between departments. 

What KPIs actually belong on a hospital discharge dashboard 

Not every metric earns a place on a command center screen. Some are useful for monthly board reporting and worthless for a shift-level decision and mixing the two is part of what causes dashboard fatigue in the first place. 

Action-Ready KPIs vs. Reporting-Only Metrics 

Track in Real Time (Action-Ready) Track Monthly (Reporting-Only) 
Patients past expected discharge time today Average length of stay, trended over a quarter 
Barriers unresolved past their escalation window Case mix index and its effect on GMLOS targets 
Beds pending clean past a set threshold Year-over-year discharge volume by service line 
Discharges scheduled today, by readiness status Patient satisfaction scores tied to discharge experience 

The left column belongs on a live operational screen because someone needs to act on it within the hour. The right column belongs in a board deck, because it describes a trend, not a decision. Confusing the two is one of the quieter reasons hospital operations dashboard projects lose credibility with frontline staff: nobody wants to stare at a quarterly trend line while a patient sits in a bed they no longer clinically need.

The data foundation behind every closed loop 

None of this works if the underlying patient record is unreliable. A closed-loop workflow that routes a discharge barrier to the right owner is only as good as the system’s ability to know, with certainty, that the patient in bed 14 today is the same patient who had labs pending yesterday and a prior authorization pending the day before. 

That’s a Master Patient Index and Patient 360 problem before it’s an automation problem. Duplicate records, mismatched identifiers across departments, and a fragmented view of the same patient across the EHR, the lab system, and the post-acute referral platform are exactly the kind of silent failure that routes a barrier to the wrong person, or misses it entirely. Healthcare data integration services that consolidate those fragmented views aren’t a separate project from throughput improvement. They’re the prerequisite for it. 

This is also where the broader digital transformation in healthcare conversation and the length-of-stay conversation actually meet. A hospital doesn’t need every system replaced to close the loop on discharge delays. It needs a governed, accurate patient record that healthcare-ready AI agents can act on with confidence, because an agent escalating a barrier based on a duplicate or stale record does more harm than a dashboard that simply sits there, quietly, being wrong.

Choosing a platform that closes the loop, not just visualizes it 

Most hospitals already own capable visualization tools. Tableau, Power BI, and EHR-native reporting modules aren’t the gap; EHR-embedded alerts vs standalone dashboards is a real design decision, but either way, the visualization layer is mature technology. The gap sits one layer up, in whether anything downstream of the chart is designed to act. 

When evaluating a platform meant to close that gap, three questions tend to separate genuine actionable healthcare analytics from a dashboard with a new name attached: 

  • Does it route a flagged issue to a named owner automatically, or does it depend on someone checking a screen?  
  • Does it escalate on its own when the owner doesn’t respond within a defined window, or does the flag simply age in place?  
  • And after ninety days, can it show which specific barriers it resolved and how much bed time that recovered, or does it only show that the flags existed? 

This is the layer Inferenz’s Caregence HIPAA compliant healthcare native agentic AI platform is built to sit on top of an existing bed board, EHR, and transfer center, so a flagged discharge barrier gets routed and escalated automatically instead of waiting for the next huddle.  

It pairs with the predictive discharge and readmission models built on Inferenz’s data science and predictive analytics services to move a hospital from watching a problem to closing it.

Every hospital's closed-loop gap sits somewhere different. Know where the LoS problem lives and how to close the loop. Frequently Asked Questions 

An Overview of GPT-6 Astra in Healthcare

Executive Summary 

For healthcare CXOs weighing generative AI and agentic AI investments, GPT-6 Astra’s real story isn’t its benchmark score. It’s the 1.05-million-token context window, the prompt-caching economics, and the HIPAA compliance gate that decide whether a pilot survives contact with a real patient record. This brief breaks down what changes for clinical documentation, care coordination, and healthcare AI governance, and what still requires a signed Business Associate Agreement before any patient data goes near the model.

Why this release is different for healthcare 

OpenAI shipped GPT-6 Astra on September 3, 2026, in the same week Anthropic, Google, and Meta all pushed out their own frontier updates, a cluster of launches so tight that CNBC coined the term “model fatigue” to describe how hard it has become for buyers to keep the scoreboard straight.  

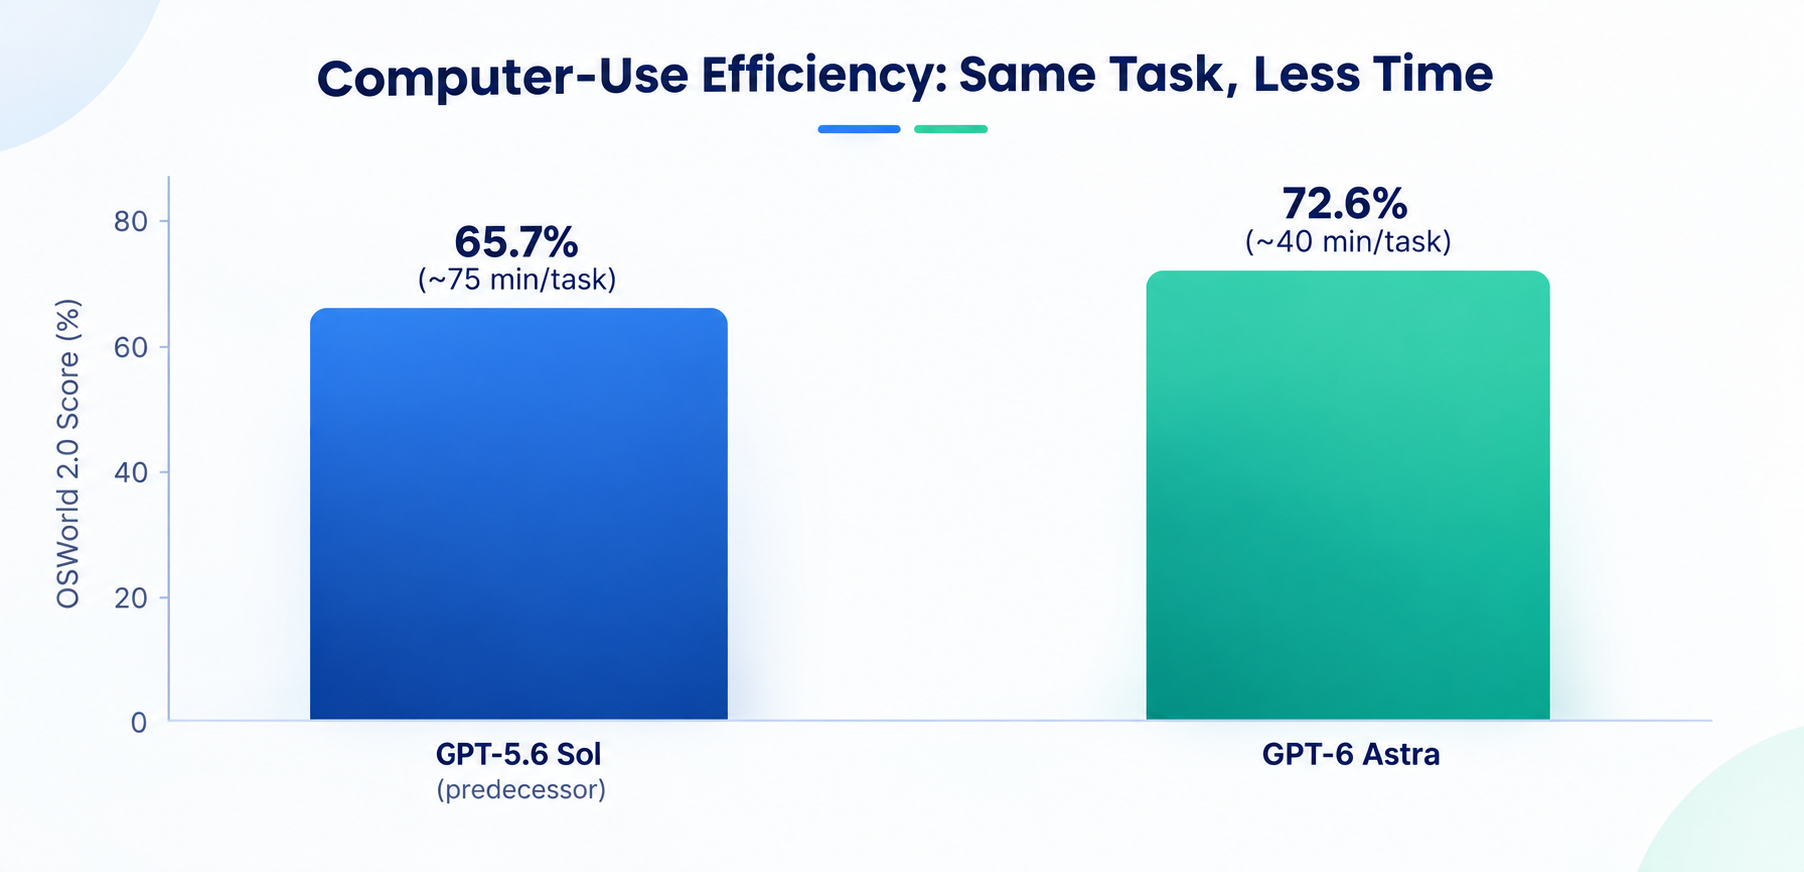
For a general audience, Astra’s headline numbers are the story: a context window of roughly 1.05 million tokens, near-saturated scores on FrontierMath and ARC-AGI-3, and the first OpenAI model to meet the “Critical” threshold for cybersecurity capability under the company’s Preparedness Framework. 

For healthcare, none of that is the interesting part. The interesting part is what changes operationally when a model this capable is dropped into a hospital’s documentation queue, a home-care agency’s referral pipeline, or a payer’s prior-authorization backlog, and what still, deliberately, doesn’t change. 

That operational lens, not the leaderboard, is what matters for healthcare AI governance and generative AI adoption at the health-system level.

Astra at a glance, healthcare-relevant numbers only. Bracketed numbers reference the Sources list.

The benchmark that actually matters here 

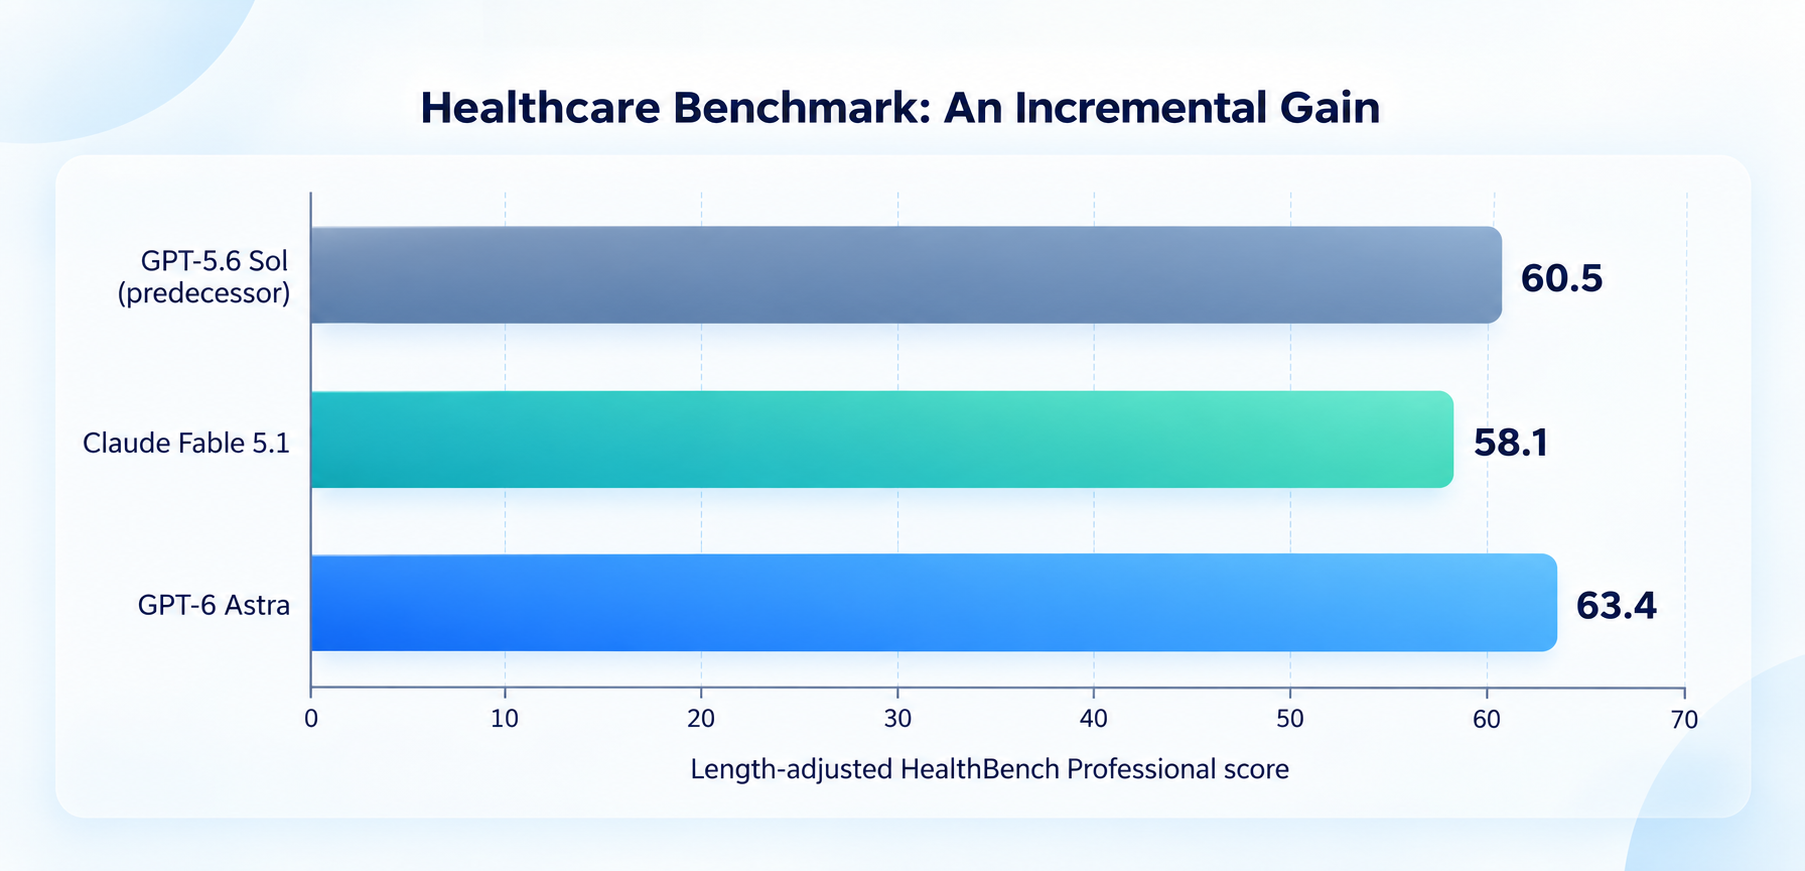
Astra scored 63.4% on the length-adjusted HealthBench Professional evaluation, up from 60.5% for its predecessor, GPT-5.6 Sol, and ahead of Claude Fable 5.1’s 58.1%. That comparison carries an important caveat: OpenAI graded all three models itself, using its own GPT-5.4 grader and an Opus 5 fallback for cases where Fable 5.1 declined to answer, this is not Anthropic’s self-reported figure. A real but incremental gain, and the wrong number to lead with regardless: length-adjusted scoring exists because a longer answer can satisfy more rubric checkboxes without being clearer or more clinically useful, the benchmark itself is warning readers not to over-read it.

The benchmark that actually matters here

None of this constitutes diagnostic accuracy, prospective clinical validation, or regulatory clearance. Astra is not a medical device, and OpenAI hasn’t positioned it as one; it’s a foundation model that healthcare products get built on top of, and that distinction carries real weight for anyone evaluating it for clinical use.  

For CXOs building a healthcare AI governance framework, that distinction between a foundation model and a regulated clinical device is the first line item in any vendor risk assessment. 

What actually changes: context, not cleverness 

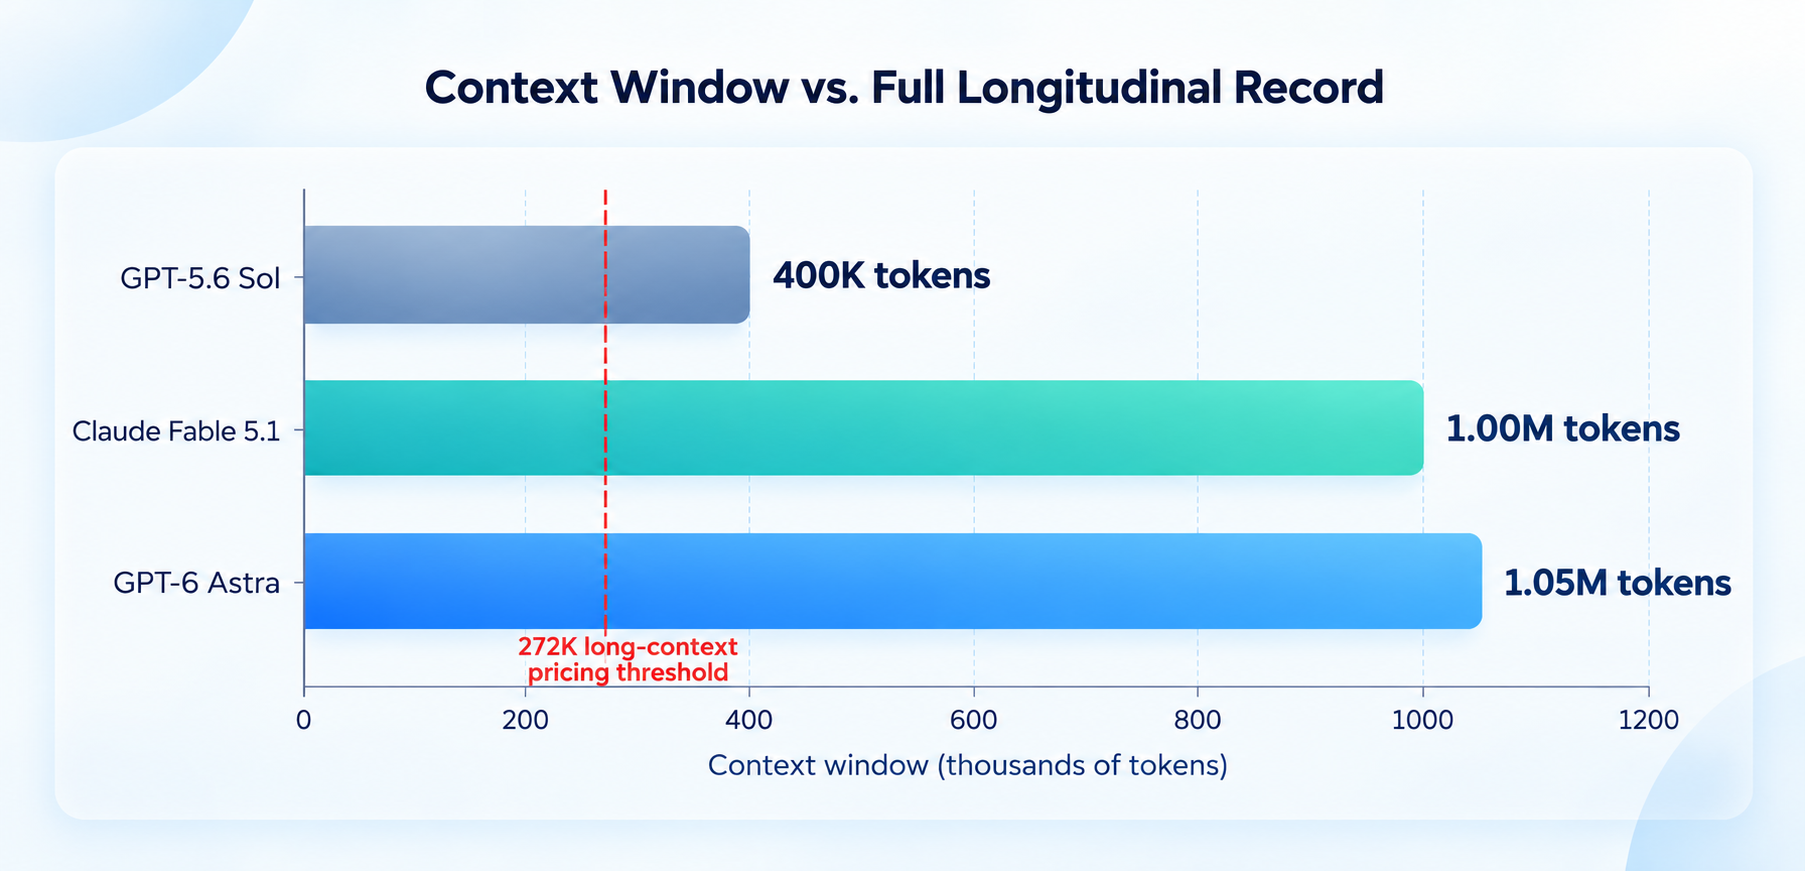
The single most consequential spec for healthcare isn’t a reasoning benchmark, it’s the roughly 1.05-million-token context window. A longitudinal patient record isn’t one document; it’s years of visit notes, lab trends, referral letters, discharge summaries, and imaging reports scattered across systems that don’t talk to each other. Previous-generation context limits forced aggressive summarization before a model could even look at the full picture. 

Context window growth, with the long-context pricing threshold marked [1,2,7]

At a million-plus tokens, an application can hand Astra genuinely comprehensive input in a single pass. That doesn’t fix the underlying mess of a real medical record, duplicated entries, inconsistent formatting, contradictory timestamps are still there, but it removes the artificial ceiling that used to force pre-summarization. Paired with native web search, file search, code execution, computer use, and tool-calling (MCP), Astra shifts from answering questions to doing structured, multi-step tasks like application development. That agentic capability is the actual product opportunity, more than any single point of benchmark improvement, per independent healthcare-AI analysis.

Where this shows up in real workflows 

Framed as applications rather than capabilities, here is what realistic healthcare use looks like, per independent clinical-AI analysis:  

Chart Review 

Synthesizes a fragmented, multi-year record into a usable pre-visit summary. 

Evidence Synthesis 

Builds a referenced briefing on a clinical question from literature and structured sources. 

Documentation 

Drafts referrals, discharge summaries, prior-auth requests, and patient letters. 

Care Coordination 

Reconciles referrals, results, and correspondence across disconnected systems. 

Research & Data Analysis 

Runs reproducible code across large structured health datasets. 

Health-Tech Development 

Builds and maintains the software healthcare workflows actually run on. 

Turning GPT-6 Astra's raw capability into a governed, HIPAA-ready healthcare workflow takes more than a system prompt.

What Astra should not be used for 

Keep the clinician in the loop, always. 

  • Autonomous triage: deciding a patient’s urgency or pathway without clinician review. 
  • Prescribing and order entry: generating a prescription or investigation order without a human decision-maker in the loop. 
  • Unreviewed patient communication: sending clinical information to a patient without a clinician checking it first. 
  • Acting beyond authorized scope: as agentic capability grows, what a system is permitted to do matters more than what it’s capable of doing. 

The Compliance Gate: BAA Before PHI 

Protected health information can only touch Astra if OpenAI has executed a Business Associate Agreement specific to that deployment, API, Enterprise account, whichever surface is actually in use, and the environment is confirmed HIPAA-eligible. Verify BAA coverage for the exact product surface before any pilot touches real patient data.  

 A signed BAA and a mapped data-flow diagram are the two artifacts most healthcare compliance software reviews ask for first, and the two most pilots skip. 

Cost and caching: what decides affordability at scale 

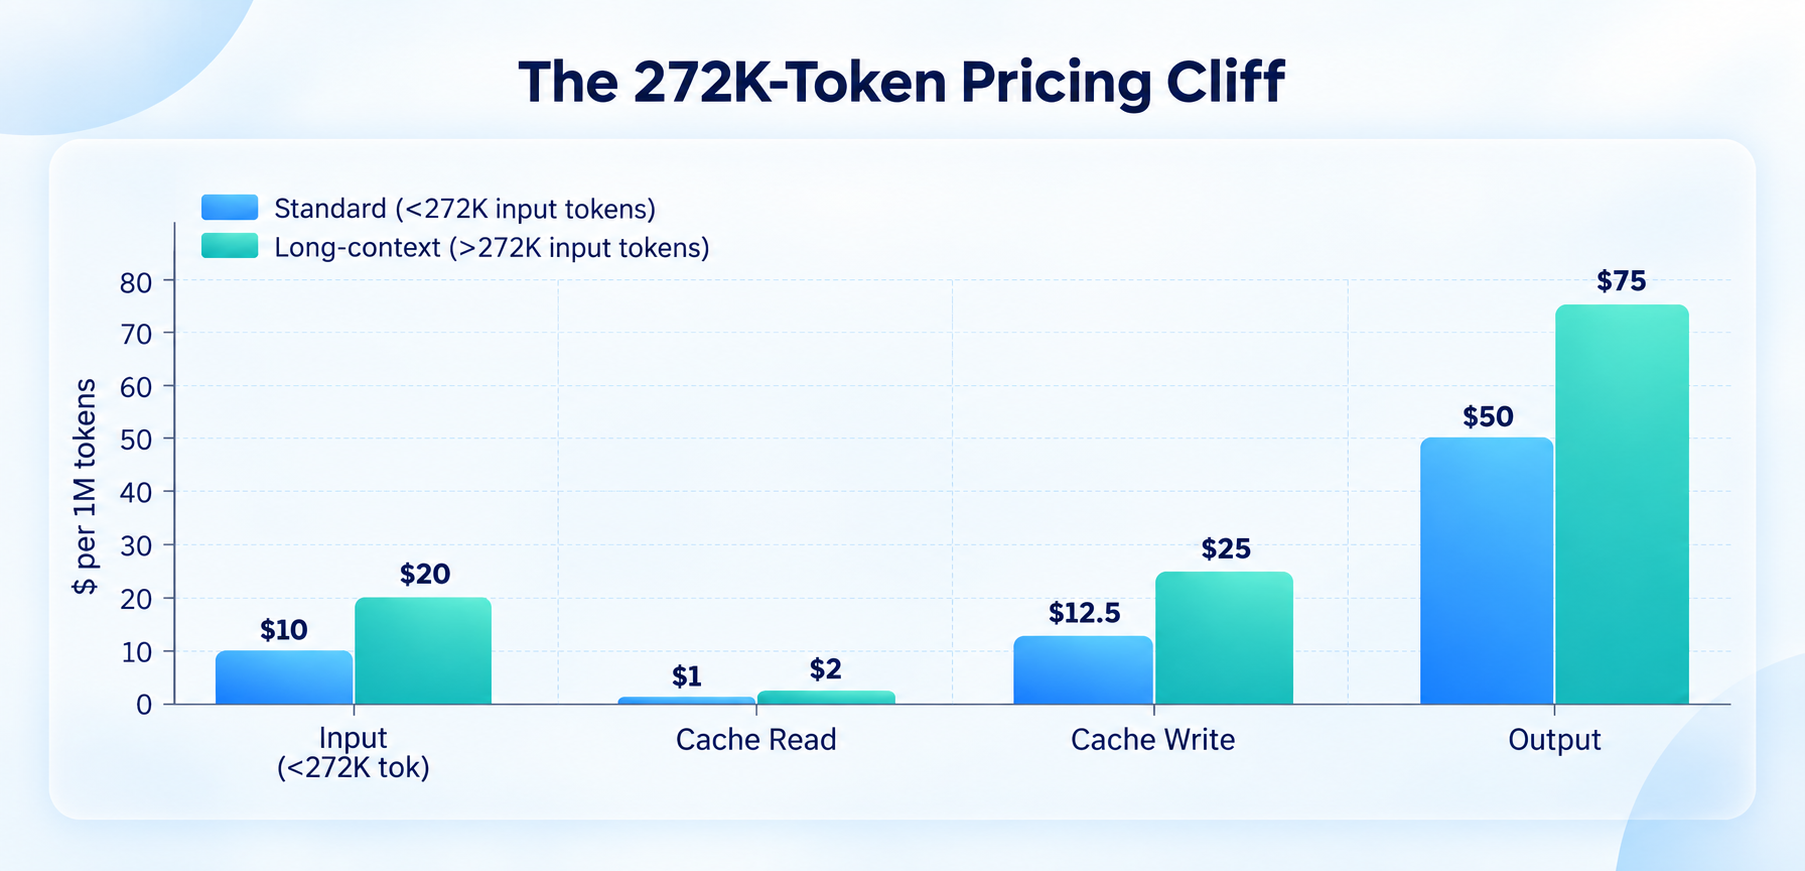
This is where the economics diverge sharply from a single chatbot query, and where a workflow orchestrator’s design choices matter as much as model choice. Astra’s OpenAI API standard rate is $10 per million input tokens and $50 per million output tokens. But cross 272,000 input tokens in a single request, trivially easy with a multi-year chart, and the entire request, not just the overage, reprices to OpenAI’s published long-context rate: $20 input, $2 cached input, $25 cache writes, and $75 output per million tokens, roughly double on input and cache, and 1.5x on output. 

Standard vs. long-context pricing per 1M tokens, from OpenAI's own pricing page 

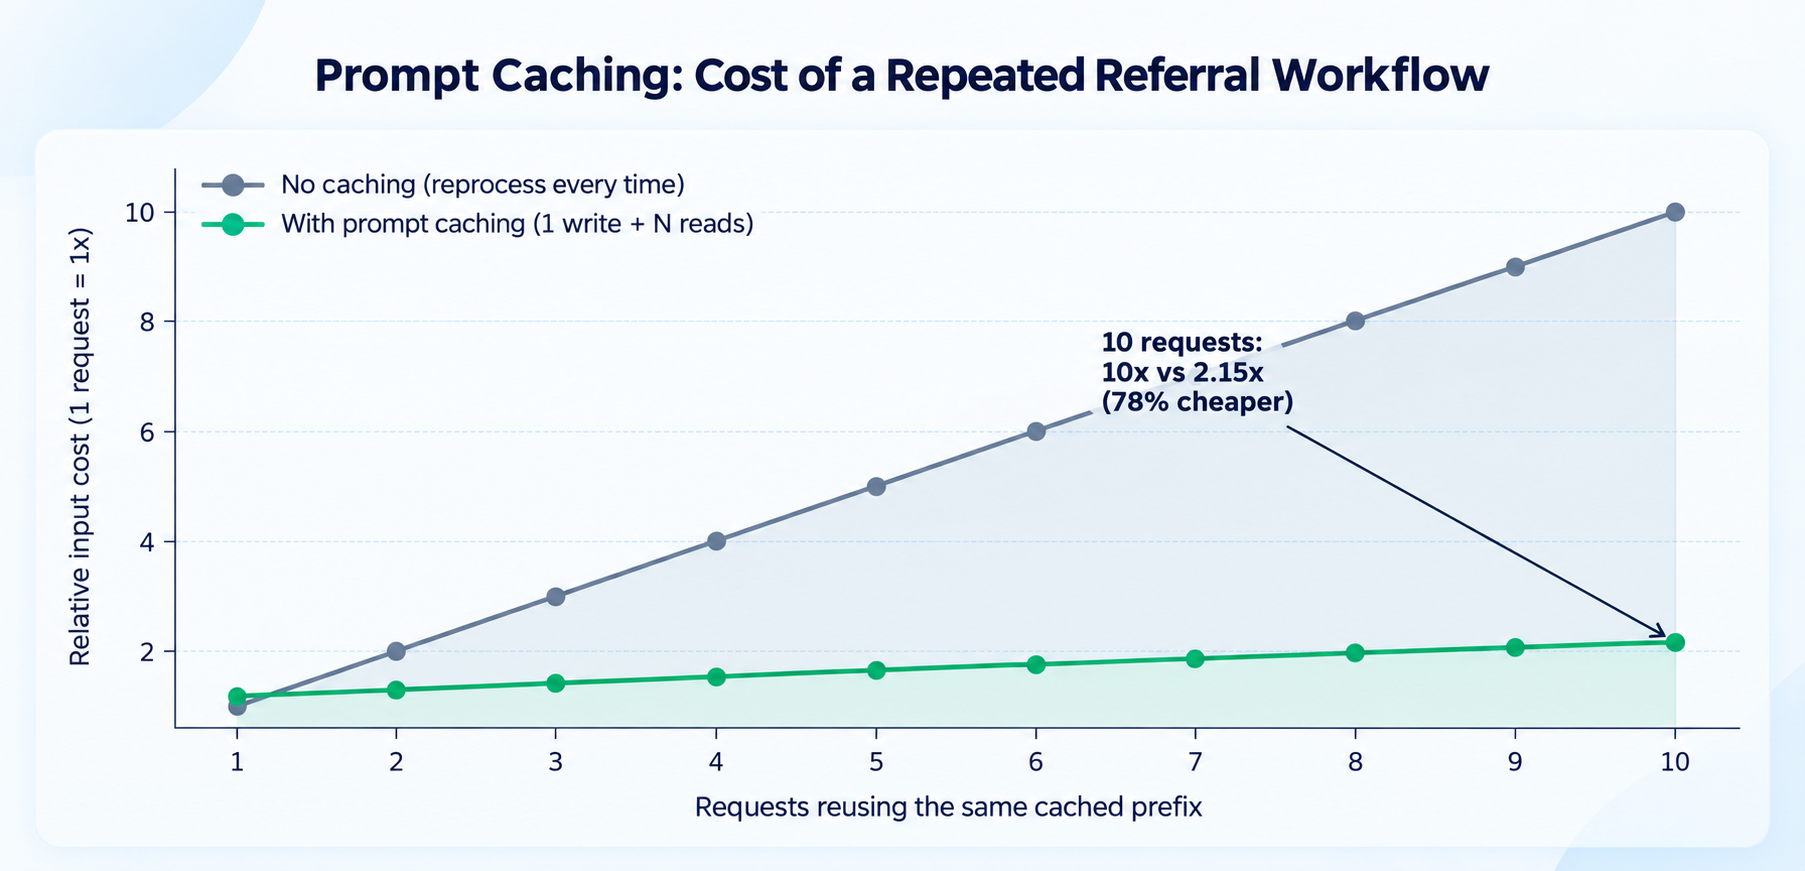
Prompt caching is what makes repeated, structured workflows economical rather than merely possible. A referral-intake or eligibility-screening pipeline reuses the same scaffolding on every case, the same guideline text, the same extraction schema, the same triage framework, while only the patient-specific data changes. Cached tokens on Astra cost roughly a tenth of the standard input rate, and Astra adds explicit cache breakpoints on top of the automatic implicit caching older models had, so a developer can pin exactly where the reusable guideline block ends and volatile per-patient content begins. 

Relative input cost across ten requests reusing the same cached prefix, modeled on OpenAI's published cache-write/cache-read multipliers

For a queue processing hundreds or thousands of referrals a day, that’s the difference between reprocessing an entire rulebook on every case and paying full price once, then a fraction of it forever after. 

That single design choice, caching reusable guideline text instead of resending it, is often what separates a healthcare AI platform or a pilot that scales from one that quietly blows through its budget.

How it stacks up: GPT 6 Astra vs. Claude Fable 5.1 

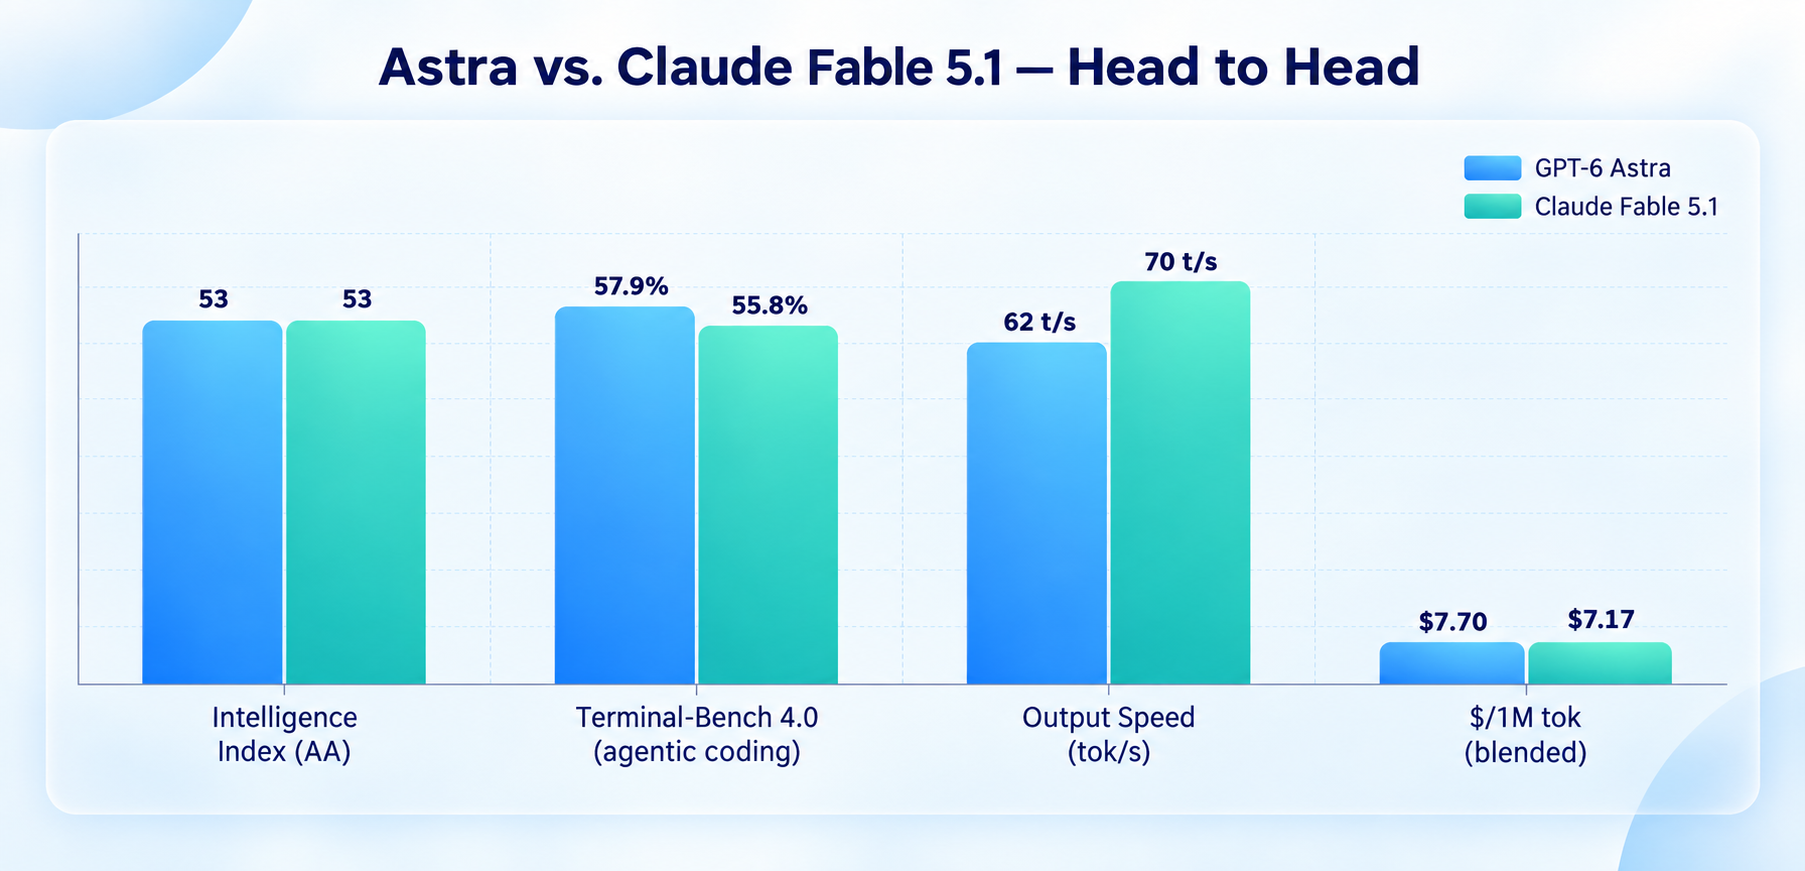
Against Claude Fable 5.1, Anthropic’s model released in the same launch window, the two are close enough on Artificial Analysis’s live head-to-head comparison that model choice for healthcare workflow automation should probably be decided by solution fit rather than benchmark bragging rights.

Head-to-head on intelligence, agentic coding, speed, and blended cost (bars normalized for visual comparison; real values labeled)

Metric GPT-6 Astra Claude Fable 5.1 
Intelligence Index (Artificial Analysis, live) 53 53 (tied) 
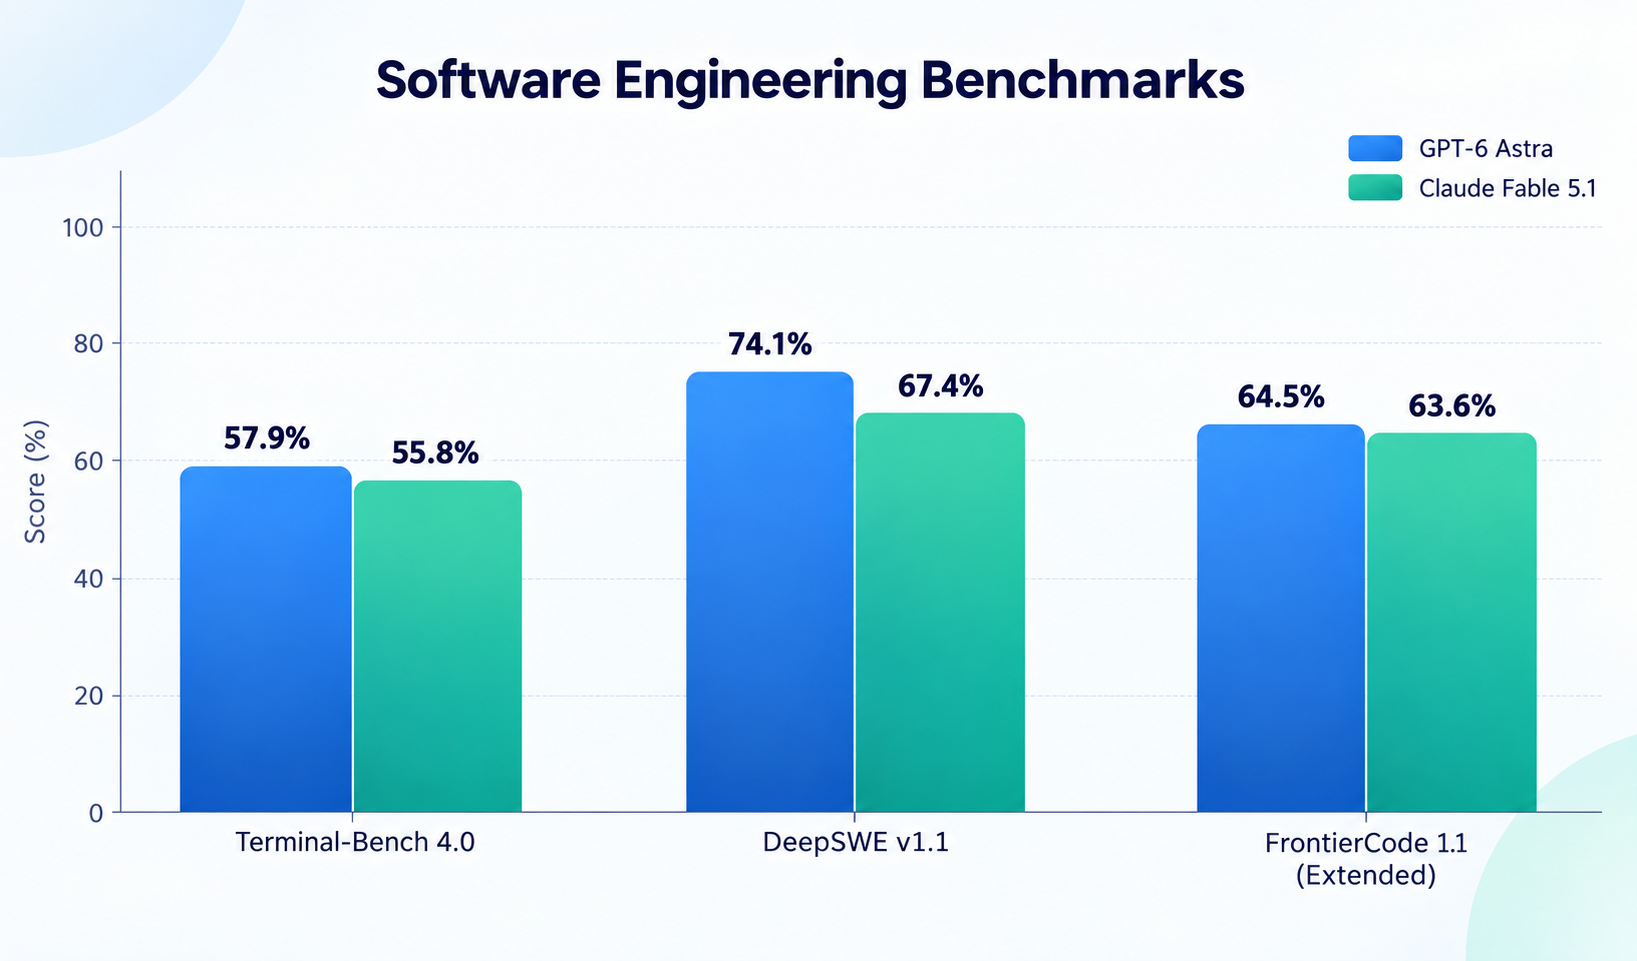
Terminal-Bench 4.0 (agentic coding, OpenAI-reported) 57.9% 55.8% 
Output speed (tokens/sec, Artificial Analysis) 62 70 
Blended cost per 1M tokens (Artificial Analysis) $7.70 $7.17 
HealthBench Professional, length-adjusted (OpenAI-graded) 63.4% 58.1% 
Context window ~1.05M tokens ~1M tokens 
Standout strength Research math, cybersecurity, computer use Multi-hour agentic coding, cache discount up to 45% 
Cloud availability at launch OpenAI API, Azure, AWS Bedrock AWS, Google Cloud, Microsoft Azure 
Enterprise default Off until admin enables 30-day retention required, not on Priority Tier 

Fable 5.1 is faster (70 vs. 62 output tokens/sec) and marginally cheaper on blended cost; Astra edges ahead on Terminal-Bench 4.0 agentic-coding tasks and on the OpenAI-graded HealthBench Professional comparison, and both are effectively tied on Artificial Analysis’s Intelligence Index. Fable 5.1’s own prompt-caching redesign is aggressive in its own right, Anthropic dropped cached-input pricing from $1 to $0.25 per million tokens, cutting typical workloads by roughly 25% and highly agentic workloads by up to 45%, which matters just as much as Astra’s caching story for anyone building a multi-step clinical workflow rather than firing single queries. 

The more relevant enterprise distinction is availability and rollout posture: Astra is off by default in enterprise workspaces until an administrator explicitly enables it, and its cloud footprint at launch, OpenAI API, Microsoft Azure, and AWS Bedrock, is narrower than Fable 5.1’s three-cloud availability. For a healthcare IT team already standardized on a particular cloud and compliance posture, that operational detail may decide the question before a single benchmark is consulted. 

The verdict 

Astra is a more capable clinical co-worker, not a more autonomous one. The context window and agentic tooling meaningfully expand what an application can do around a patient record, comprehensive review instead of forced summarization, drafted documentation instead of blank-page starts, reconciled referrals instead of manually stitched fragments. 

None of that reduces the need for clinical grounding, jurisdiction-specific guidance, human review of anything patient-facing, or a properly executed BAA before real data enters the system. The organizations that get the most out of this release won’t be the ones chasing the benchmark delta, they’ll be the ones that redesign their prompt structure around caching, respect the 272K-token pricing cliff, and keep the clinician firmly in the loop on everything the model drafts. 

For healthcare CXOs, the real decision isn’t GPT-6 Astra versus Claude Fable 5.1. It’s whether your organization has the AI governance, HIPAA-compliant infrastructure, and workflow design in place to capture either model’s agentic upside safely.

Picking a frontier model is the easy part. Building the HIPAA-compliant workflow around it is where most healthcare AI programs stall.Frequently Asked Questions 

Staffing and Demand Forecasting: How Hospitals Are Matching Nurse Capacity to Patient Flow

Summary

Hospital staffing and demand forecasting uses AI predictive staffing models to match nurse capacity to real-time patient flow, forecasting census, acuity, and skill-mix before shifts are built instead of filling gaps after they appear. This approach cuts agency staffing costs and reduces nurse burnout by pairing EHR-integrated staffing analytics with census-based demand forecasting and delivers measurable ROI. Governance guardrails for union rules, fatigue limits, and compliance, presents a clear solution to hospital staffing shortage.

Introduction 

Most nurse staffing shortages are not surprises. They are forecasting failures that surface weeks after the warning signs first appeared, buried in a census trend nobody tracked or a schedule built on instinct instead of evidence. By the time a unit is short two nurses on a Tuesday afternoon, the real failure already happened three weeks earlier. 

The math behind that isn’t going away on its own. The Health Resources and Services Administration’s most recent national workforce projections put the country roughly 8 to 10 percent short of the registered nurses hospitals will need through the back half of this decade, worse in rural areas, worse in behavioral health and long-term care. The Bureau of Labor Statistics still projects steady growth in RN demand, roughly 180,800 openings a year through 2035, largely because an aging population needs more care, not less. Put those two numbers side by side and the conclusion is blunt: hospitals cannot hire their way out of this gap. They have to get sharper about matching the staff they already have to the patients who are actually coming. 

This is the third piece in our series of articles related to the hospital throughput crisis, and it sits closer to the ground than bed capacity and discharge delays. Staffing decides whether a unit can actually absorb the patients those beds are holding. If your census forecast and your staffing plan get built separately, on different timelines, by different teams, you will always be reacting to demand instead of meeting it. 

For a transformation leader trying to prove AI can solve a defined operational problem rather than just look impressive in a demo, staffing and demand forecasting is one of the cleanest use cases in the hospital. The data already exists somewhere in your systems.  

The KPI is obvious:  

  • Fewer shifts filled by agency staff 
  • Fewer forced overtime hours 
  • Fewer nurse-to-patient ratios pushed past safe limits 

The failure mode is visible fast if you get it wrong. Real data is a measurable outcome combined with fast feedback. That combination is exactly what makes this a sound place to spend one of the one or two agentic AI initiatives a board could fund this year. 

How much can hospitals really cut from agency staffing spend with AI forecasting? 

Ask a vendor this question and you’ll get a round number, usually 20 percent, delivered with total confidence. You know it as much as I do that the trail usually goes cold when you try to point out a recent study to back it up. 

Here’s a number worth trusting instead.  

Researchers at Columbia Business School, working with Stanford and clinicians at Hackensack University Medical Center, built and tested a prediction-driven nurse staffing model for a real emergency department.  

The result: hourly nursing labor costs dropped by more than $160, which worked out to roughly $1.4 million in annual savings for a single ED, while wait times, treatment duration, and patient flow held steady.  

No quality trade-off buried in the fine print. A measured cost reduction sitting right next to stable clinical performance. 

That’s the standard to hold any staffing forecasting tool, or any AI initiative, to in a hospital. Whether you choose a vendor offering predictive analytics services or build the capability internally, insist on seeing cost and quality numbers together before you fund a rollout past a single unit.

The data you need before an AI predictive staffing model will work 

This is where most staffing AI pilots quietly die, and it happens before a single algorithm runs. 

An AI predictive staffing model in healthcare needs clean history. Here are some other basic requirements:  

Data Input What It Includes Why It Matters 
ADT data 12–24 months of admission, discharge, and transfer records, by unit Gives the model enough history to learn real patterns, not just recent noise 
Staffing ratios & skill mix Nurse-to-patient ratios and skill mix by shift, not just headcount Headcount alone hides whether the right staff were on the floor 
Patient acuity scores Acuity data tied to the actual staffing decisions made at the time Lets the model learn what drove a decision, instead of guessing from census alone 
Payroll & scheduling history Overtime patterns and agency/travel nurse fill history Shows where reactive staffing has been masking a forecasting gap 
External demand signals Local flu surveillance data, school calendars, elective surgery schedules Captures predictable volume swings the model would otherwise miss 

 Most hospitals have pieces of this scattered across the EHR, a separate scheduling platform, and payroll, with no shared identifier connecting them. That’s a data strategy problem before it’s a modeling problem. Our data strategy consulting services ensure that our experts map what you have, fix the identifiers that don’t match across systems, and build the pipeline before anyone talks about algorithms. Skip any of these steps and you get a model that falls apart the first week it meets real hospital data.

Deploy-predictive-models-that-help-your-hospital-to-anticipate-outcomes-and-make-smarter-decisionsForecasting Patient Volume and Staffing Together, Not in Sequence 

A common mistake: build a patient volume forecast, hand it to workforce planning, and let them build a staffing plan on top of it a week later. By the time the staffing plan is ready, the volume forecast is already stale. 

Census-based staffing models that actually work run both forecasts on the same clock, ideally the same data pipeline. Emergency department demand forecasting, seasonal patient volume prediction, and unit-level staffing recommendations need to update together, on a rolling basis, not as two separate reports reconciled manually every Friday.  

This is closer to what predictive modeling in healthcare should mean in practice: one model, or a tightly linked pair of models, producing a staffing recommendation that already accounts for tomorrow’s expected census, not last month’s average. 

The payoff shows up in surge planning. A hospital forecasting volume and staffing on the same cycle can flex float pools and agency requests days ahead of a predictable surge, flu season being the obvious example, instead of scrambling once volume spikes.

Differences between scheduling software and true predictive demand forecasting 

Both scheduling software and predictive demand forecasting solutions get sold as the same thing. They are not. 

A nurse scheduling optimization software takes a staffing template you already decided on and fills it efficiently. The nurse scheduling solution matches nurse preferences, certifications, and fatigue rules against open shifts. It’s a reactive staffing model wearing a modern interface. It usually answers “who works Tuesday” well. It doesn’t answer “how many nurses does Tuesday actually need” which could be addressed through a predictive nurse scheduling solution. 

Predictive demand forecasting answers that second question first. It reads historical and real-time signals, census trends, ED arrival rates, discharge velocity, seasonal patterns, to estimate the staffing level a unit will need before the shift is built, then hands that number to the scheduling layer. One tool optimizes a plan. The other decides what the plan should be. Hospitals that only buy the first one are still staffing reactively, just with better software. 

To explain this, here is a comparison table  

 Reactive Staffing Predictive Staffing 
Trigger An open shift or a census spike that’s already happened A forecasted census or acuity shift, days to weeks out 
Primary tool Scheduling optimization software Demand forecasting model + scheduling layer 
Typical fix Overtime or last-minute agency nurse Float pool or pre-arranged coverage 
Cost pattern Spikes unpredictably with agency premiums Smooths out, budgeted in advance 
Burnout impact High, driven by last-minute callouts Lower, staff get advance notice 
What it answers “Who works Tuesday?” “How many nurses does Tuesday need?” 

How accurate are AI staffing forecasts compared to a spreadsheet? 

Don’t accept an accuracy claim without asking how it was measured. “95 percent accurate” means very little without knowing the forecast window, the unit type, and what counts as a miss. 

The honest way to evaluate this: backtest the model against 6 to 12 months of your own historical census and staffing data before go-live, then track forecast error on a rolling basis afterward, comparing predicted versus actual need by unit and shift. A model that’s directionally reliable two to three weeks out, and tightens as the shift approaches, is far more useful than one claiming impossible precision a month in advance. 

Spreadsheet-based forecasting, by comparison, is usually built on last month’s average and a scheduler’s memory of what felt busy. It has no error tracking at all, which is exactly why it feels accurate right up until the week it isn’t. 

Why skill-mix and acuity matter more than headcount 

A unit staffed to the right headcount with the wrong skill mix is still understaffed. This is the gap pure census-based models miss. 

Patient acuity-based staffing accounts for the fact that ten stable post-op patients and ten high-acuity step-downs are not the same staffing problem, even at identical census. Skill-mix forecasting for hospitals needs to layer certification level, specialty competency, and acuity trends on top of raw patient counts, or it will recommend the right number of bodies and the wrong capability. A lot of “AI staffing” tools fall short here. They optimize headcount because headcount is the easy number to forecast. Acuity and skill mix are harder, which is exactly why they matter more. 

What it takes to connect a forecasting tool to your EHR and payroll systems 

This is the question that should come before a vendor demo, not after a contract is signed. 

Real-time bed occupancy forecasting and EHR-integrated staffing analytics depend on live or near-live feeds from your EHR’s ADT stream, your scheduling platform, and your payroll or HR system, each very likely built by a different vendor, on a different data model, at a different point in your hospital’s history.  

Integration effort here typically breaks into three buckets: pulling clean, structured data out of each source system; reconciling identifiers so a patient or a shift means the same thing across all three; and building the feedback loop that lets the model learn from what actually happened, not just what was scheduled.

Vendor Evaluation Checklist 

Ask the vendor Why it matters 
What’s your forecast error rate, backtested on our own data? Vendor-claimed accuracy without your data means nothing 
Which of the three integration buckets (data pull, identifier match, feedback loop) do you own? Tells you what becomes your team’s job 
Can you show cost savings and stable quality metrics together? One without the other isn’t proof 
Are union rules, fatigue limits, and audit trails built in or bolted on? Determines whether it survives a labor dispute 

 Evaluate vendors to walk through exactly these questions and what is expected from your team. Get the answers and you’re sorted. 

Building guardrails: union rules, fatigue limits, and compliance in an AI staffing model 

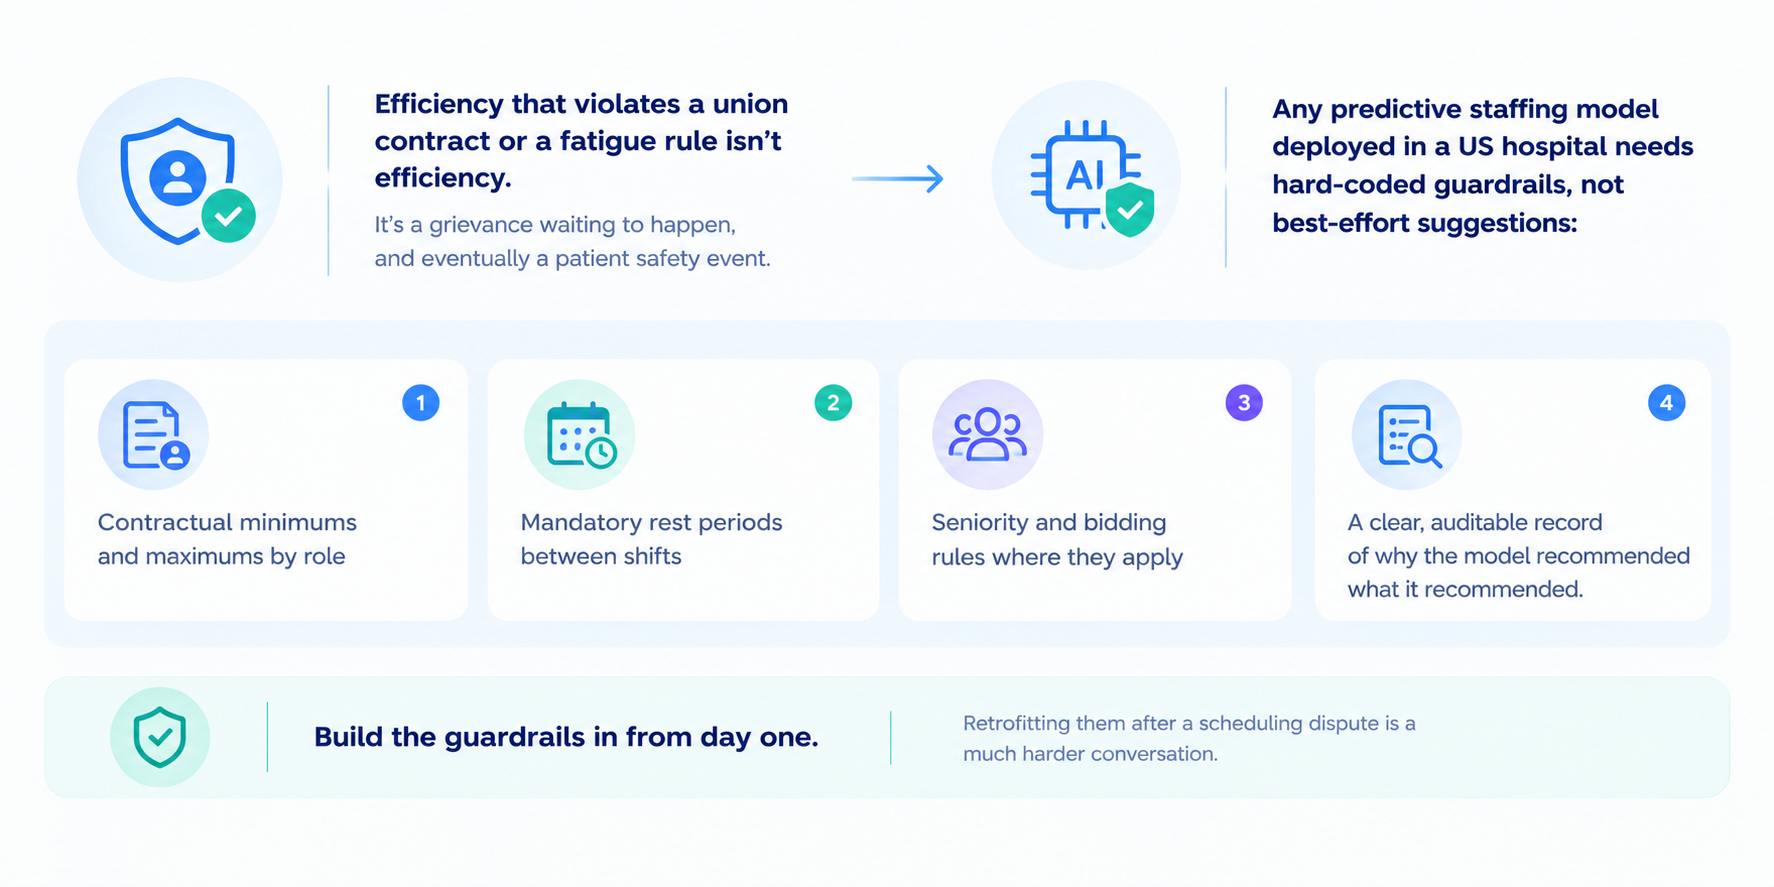
Building guardrails: union rules, fatigue limits, and compliance in an AI staffing modelEfficiency that violates a union contract or a fatigue rule isn’t efficiency. It’s a grievance waiting to happen, and eventually a patient safety event. 

Any predictive staffing model deployed in a US hospital needs hard-coded guardrails, not best-effort suggestions:  

  • Contractual minimums and maximums by role 
  • Mandatory rest periods between shifts 
  • Seniority and bidding rules where they apply, and  
  • A clear, auditable record of why the model recommended what it recommended.  

This is the governance work that turns a staffing forecast from a black box into something you can defend to a labor relations team, a compliance officer, and a board that just finished asking hard questions about your last AI pilot. Build the guardrails in from day one. Retrofitting them after a scheduling dispute is a much harder conversation.

The Bottom Line 

None of this requires betting the budget on a hospital-wide platform. Pick one unit, ideally the one with the worst agency spend or the most unpredictable census, and run the forecast against real data for one quarter before scaling anything. If the numbers hold, and they hold alongside stable quality metrics, that’s exactly what a board wants to see: a defined problem, a measured result, and a repeatable model for what comes next. 

See-what-Inferenz's-predictive-analytics-team-can-build-with-your-own-staffing-and-census-dataFrequently Asked Questions

The Hospital Throughput Crisis: How COOs Are Using AI to Cut LOS and Discharge Delays

Summary

A patient who’s medically cleared to go home but is still lying in a bed isn’t a staffing problem. It’s a coordination failure, and it quietly drains millions of dollars a year in beds that never reopen for the next admission. Hospital throughput AI closes that gap. It turns the moment a physician writes “discharge today” into the moment a bed is actually clean and ready, replacing whiteboards and 3 p.m. huddles with a live, predictive view of the entire patient journey. 

Throughput and Length of Stay are not the same problem 

Every hospital tracks length of stay like a scoreboard. Throughput barely gets a line on the report, and that blind spot is exactly where the money and the beds disappear. 

Length of stay counts the days a patient occupies a bed, admission to discharge.  

Throughput measures something harder to see how efficiently the whole system, beds, staff, transport, pharmacy, environmental services, moves that patient from the front door to the exit.  

Hospital and ambulatory data can often include a perfectly respectable average length of stay and yet bleed capacity in reality, every day. This happens because the real leak is usually what happens after the clinical decision to discharge has already been made. 

Operations teams have a name for that gap: the discharge-to-actual-discharge gap. It’s where most avoidable bed days live, and it’s nearly invisible on a standard length-of-stay report. We map exactly where that last mile breaks down in Why Beds Stay Occupied After the Clinical Decision to Discharge. 

What causes hospital discharge delays 

What causes hospital discharge delaysThe instinct is to blame acuity: sicker patients, more complex cases, an aging population. That’s part of the story, but not the biggest part. According to the American Hospital Association’s 2026 Costs of Caring report, hospital workforce spending rose 5.6% in 2025 alone, and hospitals spent $43 billion in 2025 simply trying to collect payment for care they had already delivered, chasing denials, prior authorization delays, and repeated documentation requests. 

None of those billions buy a single extra day of good clinical care.  

It buys time which patients spend waiting 

  • on insurance sign-offs 
  • for skilled nursing beds to open 
  • on transport 
  • for a family member to pick up the phone.  

Add ongoing workforce shortages at post-acute and behavioral health facilities, and a discharge that should take an afternoon stretches into two or three extra days. None of it shows up on a clinical chart. All of it shows up on the P&L. 

That’s why hospital solutions for discharge delays are worth budgeting for in 2026 starting with care coordination. Adding case managers to a broken handoff process just means more people waiting on the same missing information. 

The real price tag: what counts as an avoidable bed day 

An avoidable bed day is any day a patient stays in an inpatient bed after being clinically cleared to leave, for nonclinical reasons, with no reimbursement attached. Hospitals absorb the full cost, staffing, supplies, overhead, and collect none of the revenue. 

That’s the quiet part of the crisis. It’s rarely one catastrophic failure. It’s dozens of small delays compounding across a 300-bed hospital, every single day, at a cost that seldom reaches a board presentation until someone finally adds it up. This is the core of hospital capacity optimization AI: recovering capacity you already own instead of building or leasing more of it.

Build a hospital command center layer to ensure predictive discharge signals reach the people who can act on them.  From dashboards to decisions: what a hospital command center actually does 

A hospital command center AI platform isn’t a bigger screen on a wall. It’s an operating layer that pulls bed status, staffing, transport, and discharge readiness into one place, then tells someone exactly what to do about it before a backlog forms. 

The results are becoming hard to dismiss. Sutter Health ran a command center pilot across three hospitals through 2025 and, according to the American Hospital Association, cut ED arrival-to-departure time by 8%, grew transfers and direct admissions by 29%, increased discharges by 4%, and reduced net days above geometric mean length of stay by 27%, the equivalent of freeing up 12 beds a day without adding a single physical bed. 

Throughput Lever What It Actually Fixes Explored In 
Last-mile discharge coordination The gap between “cleared to leave” and “bed is open” Why beds stay occupied after the clinical decision to discharge 
Post-acute matching Out-of-network referrals draining revenue and outcomes Referral leakage to post-acute care 
Early risk flagging Patients likely to bounce back within 30 days Predicting readmission risk before it happens 
Census-based staffing Overtime cost and unsafe nurse-to-patient ratios Staffing and demand forecasting 

Baptist Health Arkansas took a comparable approach and, per Becker’s Hospital Review, saw a 32% reduction in discharge processing time, a 25% reduction in opportunity days, and a 34% reduction in geometric-mean-length-of-stay variance after standardizing predictive discharge data estimation (forecasts) and automated escalation inside its command center. 

That’s the difference between visibility and action. A dashboard tells a nurse manager that 11 patients are ready for discharge. A command center built on hospital throughput AI tells her which of them are stuck, why, and who needs to move next. 

A point to note, though. A command center is only as good as the patient view feeding it, which is why hospitals building real hospital throughput AI usually start with a Master Patient Index and Patient 360 view that reconciles bed status, case management notes, and post-acute referrals into one record instead of three. 

How AI Actually reduces Length of Stay 

Strategies that use AI to reduce length of stay rarely start with a new algorithm. They start with visibility into three things most hospitals still track separately: predicted discharge date, current discharge barriers, and who owns each barrier right now. 

Predictive discharge date estimation flags, often 24 to 48 hours out, which patients are trending toward a delay, so case managers can intervene before it happens instead of reacting the morning of. Real-time bed management software replaces the static whiteboard with a live view that updates the moment a bed is marked clean. And care coordination software ties case management, nursing, and physician rounds together, so a barrier surfaced on one unit doesn’t sit unaddressed for six hours because nobody outside that unit knew it existed. 

None of this works as a dashboard nobody owns. The hospitals seeing length of stay reduction strategies pay off are the ones pairing AI patient flow management with an accountable owner and a clock, not the ones that bought software and called it done.

ED boarding starts at the back door, not the front door 

It’s tempting to treat emergency department boarding as an ED problem. It usually isn’t. A patient boards in the ED because there’s no inpatient bed available, and there’s no inpatient bed available because a patient upstairs who’s ready to leave hasn’t left yet. 

Federal regulators have started treating that connection seriously. The Agency for Healthcare Research and Quality convened a national summit specifically because, in its own words, the causes of ED boarding “originate at the hospital or health system level and require solutions beyond the walls of the ED.” CMS has since moved to require hospitals to report ED boarding metrics as part of its quality measurement program, formally tying the two problems together. 

If your hospital is still tracking ED boarding and discharge delays on two separate dashboards, owned by two separate teams, you’re only solving half the equation. 

How to standardize discharge barrier escalation across units 

Discharge barrier escalation is what happens after a case manager identifies exactly why a patient can’t leave yet: pending labs, a family member who hasn’t been reached, an unsigned insurance form, a transport slot that was never booked. The barrier itself is rarely the hard part. The hard part is that in most hospitals, escalating it depends on someone remembering to make a call or send an email, and that someone is usually already covering twenty other patients. 

This is where agentic AI for healthcare earns its keep. Instead of a case manager manually chasing five departments, an agent can flag the barrier, route it to the right owner automatically, escalate it if nobody responds within a set window, and log the resolution, all without anyone having to remember to check a spreadsheet. It’s a meaningful piece of what Caregence, Inferenz’s HIPAA compliant agentic AI platform for healthcare was built to do for hospital operations teams. 

Nonclinical discharge delay causes account for a meaningful share of excess bed days, and they’re also the easiest to automate, because they rarely require clinical judgment. They require consistency. 

Who actually engages the patient during discharge, and why it matters? 

Who actually engages the patient during discharge, and why it matters?“Ask who ‘owns’ a patient’s discharge and most hospitals point to a case manager.  

In practice it’s a relay:  

  1. Nursing confirms readiness

  2. Case management builds the plan 

  3. A discharge navigator or a digital patient engagement platform, has to make sure the patient and family actually understand what happens next.  

That last handoff is where a surprising number of delays start. A patient confused about medication changes, or a family that couldn’t be reached to arrange a ride, turns a same-day discharge into a next-day one. This is why patient engagement matters in throughput conversations now, not just satisfaction scores. Platforms that text discharge instructions, confirm transportation, and flag confusion in real time give the care team a head start instead of a surprise. 

Where referrals, readmissions, and staffing fit into the bigger picture 

Throughput doesn’t end when a patient walks out the door. A discharge that sends a patient to an out-of-network skilled nursing facility, simply because the in-network bed wasn’t matched in time, isn’t just a coordination miss. It’s revenue and outcomes walking out with the patient. We break down exactly what that leakage costs in Referral Leakage to Post-Acute Care: The Silent Revenue and Outcomes Drain. 

Some of those same patients come back. Readmission risk doesn’t appear the day someone is readmitted, it builds during the stay, and the hospitals catching it early give their care coordination teams enough runway to actually intervene rather than react. Check out this article: Predicting Readmission Risk Before It Happens. 

How accurate are AI discharge date predictions, really? 

Case managers have always predicted discharge dates. The question isn’t whether AI guesses better than an experienced nurse, on its own, it usually doesn’t. The value shows up when the prediction runs continuously in the background, flagging patients drifting off-plan before a case manager would otherwise notice, and freeing up human judgment for the cases that actually need it. 

None of this holds together without the right people in the right place on the right day. Matching nurse staffing to predicted census, not last week’s census, is its own discipline, one that also shapes overtime cost and unsafe staffing ratios. We cover this topic in Staffing and Demand Forecasting: Matching Capacity to Patient Flow. 

Across integrated command center deployments, health systems including Baptist Health Arkansas and University Health in San Antonio have reported, per Becker’s Hospital Review, up to a 12-hour reduction in length of stay, a 2% increase in admissions, and a 5% increase in daily discharges, all without adding a single bed. AI discharge planning software doesn’t replace a case manager’s judgment. It gives that judgment a 24-to-48-hour head start.

Every hospital's throughput bottleneck built on the beds, discharges, and staffing data sits different.  Frequently Asked Questions

GPT-6 Astra vs Claude Fable 5.1: A Comparison of the Agentic AI Models

Summary

GPT-6 Astra and Claude Fable 5.1 are the two frontier agentic AI models setting the pace for computer use, agentic coding, and enterprise AI automation heading into 2027. Astra leads on computer-use accuracy, CAD and 3D reconstruction, and cybersecurity benchmarks; Fable 5.1 holds its own on output speed and blended cost. The right fit comes down to which tools, workflows, and governance model your team needs. 

At a Glance 

GPT-6 Astra, OpenAI’s flagship model released on September 3, 2026, and Claude Fable 5.1, Anthropic’s parallel release this quarter, are both built to finish work, not just answer questions. Astra pulls ahead on computer use, design and CAD reconstruction, and cybersecurity benchmarks. Fable 5.1 answers back with faster raw output and a lower blended cost. Here’s what each one does well, tool by tool, before we get into the numbers.  

Where Each Model Actually Wins

Skip the leaderboard for a second. In practice, the two models split along clean lines. 

Astra is the stronger pick for anything that touches a screen: filling out forms, running QA on a live frontend, reconstructing a 3D object from photos, or laying out a circuit board. It’s also the one OpenAI trusts, cautiously, with real offensive security work, since it’s the first model to cross the “Critical” threshold on the company’s Preparedness Framework. 

Claude Fable 5.1 answers with efficiency. Teams already inside the Anthropic ecosystem get comparable agentic coding results, a broader library of MCP Apps, and content-provenance features (a statistical watermark plus signed C2PA credentials) that Astra doesn’t publicly document yet. 

Both ship a genuinely broad toolkit rather than a single chat window. That’s the part most coverage skips, and it’s the part that actually decides whether a model fits your stack. 

What This Launch Is Really About

Most of the public conversation about GPT-6 Astra collapses it into one number: a benchmark score, a context-window size, a price tag. That misses the point. What OpenAI actually built Astra to do sits somewhere else: computer use, software engineering, design and CAD, legal work, business documents, and scientific research. https://openai.com/index/gpt-6-astra This piece covers the features, use cases, and built-in tooling that matter most across those six areas, holding the same head-to-head discipline against Claude Fable 5.1 throughout. 

Four numbers frame the launch outside pure chat benchmarks:  

  • 95.9% on BenchCAD (3D reconstruction to CAD code) 
  • 72.6% on OSWorld 2.0 (roughly 47% less time per task) 
  • 100% on ExploitBench (“Critical” cyber tier) 
  • 10+ built-in tool types via the Responses API. 
 GPT-6 Astra Claude Fable 5.1 
Launched September 3, 2026 Same launch window, 2026 
Strongest at Computer use, CAD/3D reconstruction, cybersecurity review Output speed, blended cost efficiency 
Headline benchmark 95.9% BenchCAD; 100% ExploitBench 84.3% BenchCAD; 30.4% ExploitGym 
Cybersecurity tier “Critical” (OpenAI Preparedness Framework) Not publicly documented at this tier 

Computer Use: The Biggest Single Capability Jump

Computer Use The Biggest Single Capability JumpAstra marks what OpenAI calls a new frontier in the speed, accuracy, and safety of computer use: filling out online forms, updating CRM records, organizing a calendar, drafting research summaries inside an email or document editor, and running frontend QA checks.  

In latency testing on OSWorld 2.0, Astra hit 72.6% in roughly 40 minutes per task, against 65.7% in about 75 minutes for GPT-5.6 Sol, its predecessor, a 47% cut in time for a higher score. 

Paired with an updated Codex harness, OpenAI reports 1.9x faster task completion on Mind2Web versus the prior GPT-5.6 Sol experience. For any business built around repetitive screen work (data entry, back-office operations, QA testing, research summarization), this is the feature with the widest reach across industries. It goes well beyond any single vertical. 

Agentic Coding: Long Sessions, Not Just Better Code 

Agentic Coding Long Sessions, Not Just Better CodeAstra posts real gains on agentic coding benchmarks against Claude Fable 5.1. Terminal-Bench 4.0, DeepSWE, and FrontierCode all favor Astra by several points. 

Two features matter more than the raw scores. 

Persistent notes across context windows. Rather than summarizing away detail every time a long coding session fills its context, Astra can keep searchable notes across windows in Codex. It can find a requirement or test result from an earlier message even if that detail never made it into a compacted summary. This is opt-in today and becomes the default in the coming weeks. 

Async tool calls. Astra can ask a clarifying question and keep working on an independent part of the task while it waits for a reply, instead of blocking entirely. If nobody responds, it proceeds on sensible assumptions for routine gaps but waits on consequential decisions, useful for any long-running automation where blocking on every ambiguity kills throughput.

Design, CAD and 3D: A Genuinely New Application Area 

Design, CAD and 3D A Genuinely New Application AreaBenchCAD tests whether a model can reconstruct 3D objects from multi-view renders by generating CAD code. Astra scores 95.9% with tools, well ahead of Claude Fable 5.1’s 84.3%, though Anthropic’s own system card notes that score reflects three modifications to the evaluation, worth keeping in view. 

OpenAI’s own demonstrations extend this into practical engineering and design work: laying out a printed circuit board in KiCad from a schematic, modeling a house in Blender and turning it into a walkable Unreal Engine 5 scene, and building playable games with accurate motion and graphics. 

Choosing between frontier models before a frontier model ever touches a live workflow? Business Documents, Legal Work and Scientific Research 

Astra is trained to match a business’s existing templates rather than produce generic output: slides, spreadsheets, and analyses that fit an organization’s writing and visual style, pulling only the context that matters into the final artifact. Executing complex creative workflows in videos used up to 20% fewer tokens than other models tested, which translates directly into higher-quality output for end customers. 

In early legal testing, Astra approached legal work “the way a discerning lawyer does”: distinguishing documents from established records, surfacing unsupported assumptions, and converting gaps into concrete drafting positions. On the scientific side, Astra contributed to two new results on prime-number gaps, improving a bound that had stood for more than 80 years, and it pairs scientific reasoning with computer use to inspect sequencing data and genetic variation directly inside specialized research software.

Cybersecurity: A Capability Jump with Guardrails Attached 

Cybersecurity A Capability Jump with Guardrails AttachedAstra is the first OpenAI model to meet the “Critical” threshold for cybersecurity capability under the company’s Preparedness Framework. With the right tooling, it can independently identify and develop exploits for previously unknown vulnerabilities across hardened systems. https://openai.com/index/gpt-6-astra On ExploitBench it scored 100% versus 78.5% for GPT-5.6 Sol; on ExploitGym, a harder benchmark, it scored 42.4% against Claude Fable 5.1’s 30.4%. 

Because of that jump, OpenAI is keeping the most advanced cybersecurity capability restricted to a limited group of testers through its Daybreak program rather than opening it broadly. The model is designed to refuse tasks like generating proof-of-concept exploits under standard deployment. For security teams, the more immediately usable value is defensive: secure code review, patching, and, with expanded access, vulnerability validation and malware analysis.

Built-In Tools, Side by Side 

Neither lab ships a single chat endpoint. Both ship a broad agentic toolkit. The table below lines up what’s documented for each as of this launch window; where a capability isn’t publicly documented for a model, that’s noted rather than assumed absent. 

Built-in tool GPT-6 Astra Claude Fable 5.1 
Web search Yes, native tool Yes, togglable feature 
File search / retrieval Yes, dedicated File search tool Via Files API + code execution 
Code execution / interpreter Yes, Code interpreter tool Yes, code execution tool 
Computer use (GUI control) Yes, native Computer use tool Yes, native computer-use tool 
MCP / external connectors Yes, MCP & Connectors, Secure MCP Tunnel Yes, MCP Apps 
Hosted / local shell Yes, Shell and Local shell tools Bash tool via agentic harness 
Image generation Yes, gpt-image-2 Via code execution tool 
Deep research (specialized mode) Yes, separate Deep research model Yes, Deep research feature 
Persistent output canvas Sites in ChatGPT Artifacts 
Output content provenance Not specifically documented on launch page Statistical watermark + signed C2PA credentials 

Where This Shows Up Across Industries 

  • Engineering & Manufacturing: Reconstructs 3D CAD models from multi-view renders and lays out PCBs in KiCad from a schematic. 
  • Legal: Distinguishes established records from unsupported assumptions and converts gaps into concrete drafting positions. 
  • Finance & Consulting: Produces slides, spreadsheets, and analyses that match a firm’s own templates and visual style. 
  • Web, App & Game Dev: Creates, hosts, and shares a website, web app, or game directly from a prompt. 
  • Scientific Research: Combines scientific reasoning with computer use to inspect data in specialized software; contributed to two new results on prime-number gaps. 

How the Two Models Actually Compare

On general intelligence parameters, the two are close. Astra is genuinely ahead on agentic coding, design and CAD, and cybersecurity benchmarks. Fable 5.1 stays ahead on raw output speed and blended cost. 

Both ship comparably broad tool ecosystems. Astra’s toolkit is more granular and explicitly named (tool search, async tool calling, apply patch as distinct primitives), while Fable 5.1 folds similar capability into fewer, broader features. Which one fits a given team depends far more on existing cloud commitments, tool-by-tool fit, and cost profile than on any single leaderboard position. 

Our data and AI engineering experts can help you know which model serves your needs best. Frequently Asked Questions 

Predicting Readmission Risk Before It Happens: A COO’s Playbook for Closing the Discharge Loop

Summary

A standalone readmission risk score doesn’t move a hospital’s numbers, the 2025 and 2026 evidence both say so. What works is scoring patients at three points around discharge, routing every flagged risk to a named owner with a deadline, and measuring intervention completion alongside the readmission rate itself. The piece closes with a 90-day pilot design and the three-part rule for deciding whether to scale it.

Introduction 

Every hospital COO has sat through the meeting set up for predictive analytics in healthcare. A dashboard lights up red with high-risk discharges, a task force gets formed, and six months later the 30-day readmission rate hasn’t moved. The score wasn’t wrong. Nobody built a workflow around it. 

That’s the gap most readmission-risk programs fall into. The real job isn’t predicting who comes back. It’s identifying which discharges need an intervention, assigning that intervention to a named person, and finishing it before the patient hits the next failure point. Get that right, and readmission risk prediction stops being a compliance exercise and starts closing one of the quietest leaks in hospital capacity: a bed that reopens three days later because a discharge bounced back was never actually freed. If length of stay and discharge delay are the front half of your throughput problem, as we cover in The Hospital Throughput Crisis: How COOs Are Using AI to Cut LOS and Discharge Delays, readmissions are the back half nobody puts on the same whiteboard. 

Predictive modelling in healthcare is not starting from zero here. Somewhere in the building, a predictive model is already scoring patients. What’s usually missing isn’t the math. It’s the workflow, the named owner, and the deadline attached to what the model finds. 

Why readmission risk prediction alone won’t move your numbers

Most vendor demos sell prediction as the finish line. The evidence says otherwise. A randomized evaluation of causal machine learning across 19 hospitals and 9,959 patients tested a sharper idea: instead of targeting patients with the highest predicted risk, target the ones most likely to benefit from outreach. The trial found a 30-day readmission rate of 7.7% for benefit-based targeting against 8.2% for standard care. That gap wasn’t statistically significant. 

The model itself worked fine operationally. What the study actually proved is less comfortable: a high AUC, the number vendors love to put on a slide, doesn’t tell you whether an intervention will land. Readmission risk stratification only pays off when it’s measured against preventability and available outreach capacity, not against how cleanly the model separates high-risk from low-risk patients on paper. Grade your program on discrimination alone, and you’re grading the wrong exam. 

Most hospitals aren’t starting this comparison from scratch, either. The LACE index, built on length of stay, acuity, comorbidities, and emergency-department visits, has been the default readmission screening tool for well over a decade, and it remains a fair baseline to test any newer model against. The honest question was never LACE versus a fancier algorithm. It’s whether either one, on its own, changes what a care team actually does before the patient leaves. A model that beats LACE on a validation set but doesn’t move a single workflow decision hasn’t improved anything a COO can put on a scorecard.

What the 2026 evidence actually shows

A more encouraging picture comes from a nine-hospital study published in 2026. Researchers compared 4,662 discharges supported by virtual nursing against 4,662 traditional discharges with similar baseline risk scores. Emergency-department readmissions within 30 days landed at 3.7% for the virtual-nursing group, versus 13.3% for the control group. 
That’s a real difference, and it’s still a retrospective implementation study, not a randomized trial. It shows what the workflow model can do, not that the algorithm alone caused the drop. The prediction was attached to a full discharge operating system: medication reconciliation, teach-back, follow-up scheduling, barrier resolution, and a structured post-discharge contact plan. A score sitting alone on a dashboard, with no closed-loop task behind it, is unlikely to touch outcomes at all. 

This is where the scoring engine must earn its place inside the workflow, not just inside a model registry. Inferenz’s Caregence™ Predictive Models, built on their data science and predictive analytics services embed this kind of risk model directly into clinical and operational workflows, so a discharge score triggers action instead of sitting in a report nobody opens until the next steering committee. 

Score at three moments, not once 

A single admission-time score is a snapshot from before the patient’s condition, medications, and discharge plan took final shape. Three checkpoints work better: 

  • At admission: establish a provisional risk and flag likely barriers. 

  • 24 to 48 hours before discharge: refresh the score using current labs, utilization data, medication changes, functional status, social needs, and discharge destination. 

  • At discharge and again 48 to 72 hours after: re-score or trigger a rules-based escalation the moment a patient misses a prescription fill, a follow-up visit, or a home-service connection. 

The second and third checkpoints carry more operational weight than the first, because they’re the only ones where the team can still change what happens to the patient. None of this works if a case manager has to log into four systems to see current labs, medications, and social-needs data in one place. That’s a real-time readmission risk dashboard problem before it’s a prediction problem, which is why MPI and Patient 360 matters as much here as the model itself. The use of predictive AI in discharge planning could include a risk assessment tool that refreshes on stale or fragmented data will confidently produce the wrong answer.

Three checkpoints and two lanes for responsesTwo lanes, not one risk list 

Treating every elevated score the same way guarantees alert fatigue. Split the response into two lanes instead: 

  1. High risk, high urgency: same-day case-management review, medication reconciliation, a follow-up visit booked before discharge, and resolved transportation, caregiver, food, housing, or equipment barriers.
  2. Moderate risk, high modifiability: a virtual nurse or transition coach, teach-back, a 48-hour call, a pharmacy and primary-care connection, and automated escalation if contact fails. 

The model should optimize for risk times preventability times available intervention capacity, not risk in isolation. That’s the same principle behind the benefit-based targeting study above, applied at the operational level instead of the modeling level. Case managers should keep override authority. They see context a model never will, and a program that strips out clinical judgment for the sake of algorithmic purity tends to lose clinician trust fast, which is its own kind of failure.

Turn every alert into an owned task 

A risk score without an owner is just anxiety with a percentage attached. Every alert needs three things: an owner, a deadline, and a disposition.

Turn every alert into an owned taskThis is intelligent automation in healthcare doing the unglamorous work it’s actually good at: not diagnosing anyone, just making sure a task doesn’t fall through a shift change. It’s also a clean example of agentic AI applications in healthcare done right, where the agent’s job is routing and follow-through, not clinical judgment. Inferenz’s Risk Analyzer Agent is built around exactly that pattern. It tracks vitals, visit patterns, and clinical events to flag deterioration early, routes the next best action to the right team automatically, and keeps tracking whether that action closed on time.  

Pair that with a structured post-discharge contact channel for the 48-hour call and teach-back steps, and the dashboard finally shows something more useful than a headcount of high-risk patients. It shows open tasks and how long they’ve been sitting there. 

See how a digital patient engagement layer unified post-discharge outreach for a national hospice provider.Read the case study

What COOs and CNOs should actually measure 

Two categories of metrics matter here and mixing them up is a common mistake.  

Leading indicators tell you if the workflow is running: the share of eligible discharges scored before the decision window closes, the share of high-priority patients with a named owner within four hours, medication reconciliation completed before discharge, follow-up appointments booked before discharge, successful patient contact within 48 hours, and alert acceptance, override, and closure rates by unit. 

Leading indicators (is the workflow running?) Outcome & balancing measures (did it work?) 
% of eligible discharges scored before the decision window closes 7-, 30-, and 90-day all-cause readmission 
% of high-priority patients with a named owner within 4 hours ED revisits without admission 
Medication reconciliation completed before discharge Time to first post-discharge contact 
Follow-up appointment booked before discharge Staff workload and after-hours burden 
Successful patient contact within 48 hours Mortality and observation stays 
Alert acceptance, override, and closure rates by unit Calibration by race, language, payer, disability, rurality, discharge destination 

There’s a hard financial backdrop to all this. CMS’s FY 2026 rule continues to publish Hospital Readmissions Reduction Program payment-adjustment factors for discharges beginning October 1, 2025, alongside hospital-level social-risk and behavioral-health diagnosis coding data. That turns readmission and equity monitoring into a standing operating concern for a COO, not a side project the data-science team reports on once a quarter. 

It also connects directly to whatever value-based or bundled-payment contracts your finance team is already tracking. A readmission avoided inside a bundled episode isn’t just a quality win. It’s margin your CFO can point to on the same call where HRRP penalties get discussed, which is usually the fastest way to keep a discharge-workflow program funded past its first budget cycle.

A 90-day pilot you can actually finish 

Pick one service line with real volume and a defined transition team, is what we suggest as part of our data quality, governance, and compliance services. Heart failure, COPD, general medicine, and oncology all work well as a starting point. Ninety days is short enough to keep executive attention and long enough to get past the noisiest weeks of any new workflow. 

A 90-day pilot you can actually finish The decision rule before you scale 

Fund the program past the pilot only if it clears three bars at once: a usable signal that calibrates well in your own population, operational conversion where alerts turn into completed actions inside your real staffing model, and clinical value where the intervention arm improves readmission or revisit outcomes without pushing workload, inequity, or safety risk onto your staff. 

The 2026 virtual-nursing results are encouraging, and they’re still observational, published as an early-access manuscript still working through peer edits. Pilot the workflow. Measure intervention completion, not just the risk score. Scale after your own data backs it, not after a vendor’s. 

None of this is really about the algorithm. A discharge isn’t finished when the patient walks out the door. It’s finished when they don’t come back for a preventable reason, and getting there is a staffing and workflow discipline with a model attached to it, not the other way around. This is where a digital patient engagement platform can extend the workflow beyond the hospital, helping care teams maintain meaningful patient engagement, follow-up, and communication after discharge.  

Treat readmission risk prediction as the entry ticket, not the finish line, and you’ve also closed one of the least visible drains on your throughput math, because every bed a readmission reopens is one your capacity planning already counted as free. 

Ready-to-turn-readmission-risk-into-a-working-discharge-workflow-Talk-to-us-todayFrequently Asked Questions

Referral Leakage to Post-Acute Care: The Silent Revenue and Outcomes Drain

Summary

Post-acute referral leakage quietly costs the average health system millions in margin every year, and CMS’s mandatory bundled payment model (TEAM) just turned that leakage into a direct financial and quality risk. This piece shows hospital COOs and CFOs how to measure referral leakage, build a preferred post-acute network, and close the loop with real-time data and agentic AI before the next board review turns up a number nobody can explain.

Introduction

Your discharge planner just placed a patient at a skilled nursing facility eleven miles outside your network. Nobody flagged it. Nobody will, either, not until your CFO’s quarterly review turns up a margin gap that takes three meetings to trace back to its source.

That gap has a name: referral leakage to post-acute care. It rarely shows up as a clean line item. It shows up as a slow erosion across margin, readmission data, and quality scores, and by the time finance connects the dots, the patient has already been discharged, readmitted, or lost to follow-up for months.

For a hospital COO or CFO in 2026, this stopped being a someday fix the day CMS made bundled payments mandatory. Under the Transforming Episode Accountability Model (TEAM), your organization now owns the cost and quality outcome for 30 days after a covered surgical discharge, regardless of which skilled nursing facility, home health agency, or rehab center the patient actually ends up at. Referral leakage used to be a marketing problem. It’s a balance sheet problem now.

What Referral Leakage Actually Means (and Why It Isn’t the Same as Patient Choice)

Post-acute care is the bridge between hospital discharge and full recovery: skilled nursing, inpatient rehabilitation, home health, and hospice services that pick up where the inpatient stay leaves off. Referral leakage happens when a patient who was a good fit for one of your preferred, high-performing post-acute partners ends up somewhere else instead, at a facility your system has no data-sharing agreement with, no outcomes visibility into, and often no quality track record on at all.

That’s a different problem from patient choice, and the distinction matters for compliance as much as for strategy. Federal discharge planning rules require hospitals to give every Medicare patient a list of certified home health agencies and skilled nursing facilities, along with relevant performance data, and to respect whichever provider the patient or family ultimately picks. You cannot, and should not, try to engineer that choice away.

What you can influence is which option looks easiest, fastest, and clearest on that list. A predictive matching AI agent can help discharge teams identify suitable post-acute providers based on patient needs, provider capabilities, availability, location, and relevant quality indicators. Most leakage isn’t patients actively rejecting your preferred partners. It’s a discharge planner on a Friday afternoon defaulting to whoever picks up the phone first, because nobody built a faster path to the provider who’s actually good.

The Real Number: How Much Revenue Is Leaking to Post-Acute Care, and How Do You Measure It

The Real Number: How Much Revenue Is Leaking to Post-Acute Care, and How Do You Measure ItAsk five people on your leadership team how much revenue leaks to out-of-network post-acute providers every year, and you’ll likely get five different guesses. That uncertainty is itself the finding, and it’s showing up at a moment when hospitals can least afford it.  

Fitch Ratings forecasts nonprofit hospital operating margins between just 1% and 2% for 2026, with the sector splitting into three tiers: the top 20% of systems using strong balance sheets to grow, the middle 65% expected to stagnate, and the bottom 15% losing ground.  

Against margins that thin, and that unevenly distributed, recaptured referral volume, care you’re already equipped to deliver, at reimbursement you’re already contracted for, is one of the few growth levers that can move the needle inside the same fiscal year. 

The mismatch shows up in the data wherever researchers have looked for it.  

The Medicare Payment Advisory Commission’s March 2026 report to Congress cites a peer-reviewed study finding that the discharging hospital itself had a measurably large effect on whether stroke patients were referred to an inpatient rehabilitation facility or a skilled nursing facility. The same report notes that industry stakeholders have told the Commission that inpatient rehabilitation facilities admit fewer than 40% of the patients referred to them in the first place, a gap that has little to do with network status and everything to do with a referral process that doesn’t reliably match patients to a setting that will actually take them. 

None of that variation is random, and none of it means the fix requires guessing better. It means the process determining where a patient lands, runs on hospital habits and default behavior. It is not connected to a system built to route patients to the best available fit and confirmed placement.  

If your organization doesn’t have a defined measurement approach in place, in-network capture rate, leakage rate by service line, and time-to-placement, tracked continuously through business intelligence & data visualization services instead of reconstructed after the fact once claims data finally surfaces the problem, you’re not managing referral leakage. You’re guessing at it. 

Building an Enterprise Data Platform from the Ground Up for a Post-Acute Care Organisation

Where the Leakage Actually Happens: The Discharge Planning Breakdown Points

Ask a discharge planner why a patient ended up at Facility B instead of your preferred Facility A, and the honest answer is rarely “the patient chose it.” More often, it’s one of a handful of operational failure points that repeat across nearly every health system, on nearly every shift.

Breakdown PointWhat It Looks Like on the FloorWhy It Drives Leakage
No real-time bed or capacity visibilityPlanner manually calls four or five facilities to check for an open bedWhoever answers first gets the patient, not whoever performs best
Fragmented scheduling workflowsReferral sent by fax, confirmed by phone, tracked in a spreadsheetThe loop closes late, or doesn’t close at all
Insurance and prior-auth frictionPlanner isn’t sure which post-acute partners the plan actually coversDefault becomes convenience, not network fit
No closed-loop confirmationOnce the discharge order is signed, no one confirms the placement happenedLeakage stays invisible until claims data surfaces it months later
Weekend and after-hours coverage gapsDischarge happens Friday afternoon; preferred partners don’t answerPatient goes wherever is reachable, network status aside

Table 1. Five recurring breakdown points across the post-acute referral process.

None of these are exotic problems. They’re the same five or six friction points, repeating on every shift, invisible until someone finally adds up the cost.

The Downstream Hit: Readmissions, Quality Scores, and the Beds You Can’t Turn Over

Once a patient leaves your network for post-acute care, you lose more than the placement. You lose visibility. There’s no shared data feed telling you whether that skilled nursing facility caught a medication issue early, whether the home health agency showed up for the first visit, or whether the patient is trending toward a readmission you could have prevented.

That matters more than it used to. Hospitals nationwide are now watching Medicare Advantage patients wait nearly twice as long to be discharged to post-acute care as traditional Medicare patients, a gap that has doubled since 2019, even as MA reimbursement to hospitals fell 8.8% over the same period. Hospitals are absorbing that mismatch directly: longer stays, no matching payment, and beds tied up by patients who are medically ready to leave but have nowhere confirmed to go.

Referral leakage and bed-turnover delay come from the same root cause: discharge planners without real-time visibility into which post-acute partner has capacity, takes the patient’s plan, and actually performs well on outcomes. Fix the visibility problem and both numbers move together.

The ROI Case: What a Preferred Post-Acute Network Actually Buys You

The ROI Case What a Preferred Post-Acute Network Actually Buys YouBuilding a genuinely high-performing, in-network post-acute panel, and steering referrals toward it, isn’t just a defensive move. It compounds.

  • Retained margin, at a moment when mandatory bundled payments put post-acute spend directly on your books.
  • Two-way quality data, so you can route future patients to partners who actually perform well, not just the ones with the fastest fax response.
  • Real negotiating leverage with skilled nursing facilities and home health agencies who want steady referral volume in exchange for shared outcomes accountability.
  • Faster, safer discharges, because planners choose from a short list of vetted partners instead of cold-calling down a directory.
  • A board-defensible measurement story, built on conversion rate and readmission data instead of anecdote.

CMS’s Mandatory Bundled Payments Just Raised the Stakes

If you’ve been treating post-acute referral strategy as a someday project, TEAM changed the timeline. The model has been mandatory since January 1, 2026, for more than 700 acute care hospitals across 188 geographic markets, covering five surgical episodes: lower extremity joint replacement, surgical hip and femur fracture treatment, spinal fusion, coronary artery bypass graft, and major bowel procedures. 

Here’s the part that should change how your team thinks about referrals. Each episode includes 30 days of post-acute care bundled under a single target price, covering skilled nursing, home health, and hospice. Come in under that target while hitting quality benchmarks, and the hospital shares in the savings. Let a patient leak to an out-of-network, uncoordinated, or lower-performing post-acute provider during that same window, and the hospital still owns the cost and the outcome, even though it lost control of where the patient went. 

Medicare Advantage plans add another layer of pressure, often steering patients toward their own narrow post-acute networks regardless of clinical fit or your existing partnerships. Between TEAM’s mandatory risk and MA’s narrowing networks, referral leakage has quietly become one of the more direct financial exposures on your books. Addressing that exposure requires data strategy consulting services that bring referral, payer, provider, network, and post-acute data together to give hospital leaders the visibility they need to make better-informed decisions. 

Real-Time Data and Interoperability: What Actually Closes the Loop

Most referral leakage isn’t a strategy failure. It’s a data-timing failure. The discharge planner needs to know, in the moment, which preferred partners have an open bed, accept the patient’s insurance, and have a real track record on readmissions and length of stay. Instead, that information usually lives in three different systems, none of which talk to each other, updated on three different schedules.

Closing the loop takes three things working together:

  1. A live feed of bed and capacity availability from your preferred partners
  2. Care transitions data that flows both directions between your EHR and the post-acute provider
  3. Closed-loop referral tracking that confirms a placement actually happened instead of assuming it did once the discharge order is signed.

Without that third piece, leakage stays invisible until claims data surfaces it, long after the decision that caused it.

Is Agentic AI for Referral Management Ready, or Still Overhyped?

Reasonable question, and worth a direct answer instead of a sales pitch.

Fully autonomous AI making clinical placement decisions on its own: not ready, and not something most compliance or clinical governance teams should sign off on yet. What is ready, and already deployed at scale in some health systems, is much narrower. AI agents that check real-time bed availability across your preferred network, verify insurance and prior-authorization fit, surface the best matching in-network option to the discharge planner within seconds, and automate the caregiver matching and scheduling steps that used to eat an entire afternoon.

The useful test for a COO or CFO evaluating vendors: does the AI make the decision, or does it hand the discharge planner a faster, better-informed decision to make themselves? The second version is mature technology, deployable now. The first version, mostly, is still a demo.

KPIs to Track (and How to Build Accountability Without Adding Headcount)

KPIWhat It Tells YouTarget Direction
In-network capture rateShare of eligible referrals placed with preferred, high-performing partnersHigher
Referral conversion rateShare of referrals that result in a confirmed, completed placementHigher, and faster
Time-to-placementHours from discharge order to confirmed bedLower
Readmission rate by post-acute partnerWhich partners actually perform once the patient leavesTrack continuously, route accordingly
Leakage rate by service lineWhere leakage concentrates, prioritized by TEAM-covered episodesLower, starting with highest-volume episodes

Table 2. Core KPIs for benchmarking post-acute referral performance.

You don’t need a bigger team to close this gap. You need visibility that already exists somewhere in your systems, surfaced at the moment a discharge decision gets made, with the friction stripped out. Automate the checking, the matching, and the confirming. Leave the judgment calls, and the relationships, to your discharge planners.

Where This Fits in Your Throughput Strategy

Referral leakage and bed-turnover delay are two symptoms of the same disease: discharge decisions made without real-time visibility into where a patient can actually go, safely and well. 

  • If your organization is measuring leakage for the first time, start narrow. 
  • Pick your highest-volume TEAM-covered episode and build a preferred panel of three to five post-acute partners with real outcomes data behind them. 
  • Track conversion rate for ninety days before scaling further. 

Your board doesn’t need a hundred-page strategy. It needs a number that moves, and proof of why it moved. Data engineering and integration services can connect referral, partner, placement, and outcomes data across disconnected systems, giving teams the visibility they need to identify leakage and improve throughput. 

Inferenz unifies hospital and ambulatory data into one governed foundation, building an AI-ready infrastructure for hospitals & ambulatory environments.

Frequently Asked Questions