







Hospice Eligibility Agents: Automating Intake Validation Against CMS Criteria

Summary

A hospice eligibility agent reads each referral packet, checks it against CMS eligibility criteria and your own scoring rules, and returns an Eligible, Pending Review, or Ineligible status with the reasoning attached. Your physician still certifies the prognosis. This guide shows COOs and CIOs where AI eligibility verification for hospice fits, which documentation gaps it can catch, and how to evaluate it before you buy.

Introduction

Picture a Friday, 4:40 p.m. A 38-page referral packet arrives by fax from a hospital discharge planner.

Half of it is scanned, the face-to-face note is buried on page 29, and your intake nurse has six more packets waiting. She has two bad options: rush the review and risk admitting a patient the chart can’t support or hold the referral until Monday and risk losing it to the hospice that answered first. The first option has a documented price. In a June 2026 audit, the HHS Office of Inspector General reviewed 100 initial hospice certification periods and found that 45 did not meet Medicare requirements. In 21, the clinical record didn’t support a terminal illness. In the other 24, the documentation fell short.

A hospice eligibility agent is built for that Friday. It reads the packet, checks it against CMS criteria and your own rules, and tells your team what’s missing in minutes. We are covering how AI agents improve hospice eligibility verification while staying CMS-compliant, which covers the agent layer that sits on top of a governed data foundation. This is the first of a series of articles focusing on hospice eligibility agents and how they can help in automating intake validation in line with CMS criteria.

COOs and CIOs at hospice care agencies who need answers before they sign anything will find a lot of value here. Know what the agent checks, where it stops and the physician starts, and what evidence it leaves behind for a reviewer.

Did you know?

What is a hospice eligibility agent?

A hospice eligibility agent is an AI workflow that reads a referral packet, extracts the clinical values that matter for Medicare hospice eligibility, scores them against criteria your clinical team defines, and returns a status with the reasoning attached. The status is Eligible, Pending Review, or Ineligible. A person approves the result.

A checklist needs someone to read the packet first. The agent does the reading. Referral packets arrive as scanned PDFs, faxed notes, and EHR exports, and optical character recognition (OCR) turns them into structured values such as the Palliative Performance Scale (PPS) score, hospitalizations, and documented decline. Manual packet review is one of the biggest drivers of referral intake delay, and two reviewers will often score the same chart differently. An agent applies one set of rules to every packet.

What is a hospice eligibility agent? A hospice eligibility agent is an AI workflow that reads a referral packet, extracts the clinical values that matter for Medicare hospice eligibility, scores them against criteria your clinical team defines, and returns a status with the reasoning attached. The status is Eligible, Pending Review, or Ineligible. A person approves the result. A checklist needs someone to read the packet first. The agent does the reading. Referral packets arrive as scanned PDFs, faxed notes, and EHR exports, and optical character recognition (OCR) turns them into structured values such as the Palliative Performance Scale (PPS) score, hospitalizations, and documented decline. Manual packet review is one of the biggest drivers of referral intake delay, and two reviewers will often score the same chart differently. An agent applies one set of rules to every packet. What do CMS hospice eligibility criteria require at intake? The federal rules at 42 CFR 418.22 set the documentation standard that most intake errors trace back to. The table maps each requirement to what an agent can check and who makes the call. Requirement What CMS expects What the agent can check Who decides Six-month prognosis Certification that life expectancy is six months or less if the illness runs its normal course Statement is present; supporting clinical findings are in the packet Certifying physician Who certifies For the first 90 days: medical director, physician designee, or an IDG physician, plus the attending physician if there is one Required signatures and dates are present Physicians Timing Written certification before the claim; oral certification within 2 calendar days if the written one isn’t in hand; up to 15 calendar days before the election date Certification dates against the election date Hospice admin staff Narrative Brief, patient-specific explanation of clinical findings. No check boxes or standard language. Signature and attestation in the right place Narrative is present, placed correctly, and signed Certifying physician Face-to-face encounter Required before the third benefit period and each recertification after it, no more than 30 days prior, by a hospice physician or nurse practitioner, with a signed attestation Dated, signed attestation is in the record Hospice physician or NP Election statement Names the hospice and attending physician, acknowledges care is palliative, carries the patient’s signature Each element is present Patient or representative, hospice staff Election statement addendum FY 2027 final rule: addendum on non-hospice service coverage for every beneficiary at election Yes or no field is complete Hospice staff Benefit periods Two 90-day periods, then unlimited 60-day periods, each needing certification Which period applies and what is due Hospice staff What is a certification of terminal illness (CTI)? A CTI is the physician’s signed statement that the patient’s life expectancy is six months or less if the illness runs its normal course. It needs a patient-specific narrative of the clinical findings, a signature and date, and the dates of the benefit period it covers. Who certifies hospice eligibility? Physicians do. OIG’s report notes that only a Doctor of Medicine or Osteopathy can certify or recertify a terminal illness. For the first 90 days that means the hospice medical director, physician designee, or an interdisciplinary group physician, and the attending physician if the patient has one. What is a face-to-face encounter, and when is it required? It’s an in-person visit by a hospice physician or nurse practitioner to gather clinical findings on continued eligibility. It’s required before the third benefit period and before every recertification after that, no more than 30 days ahead, with a signed and dated attestation. How do LCDs and MAC jurisdiction change the eligibility check? A local coverage determination (LCD) is a Medicare Administrative Contractor’s published criteria for when a service is reasonable and necessary. For hospice, LCDs define terminal status by diagnosis. Three MACs cover four home health and hospice jurisdictions: National Government Services (two), CGS Administrators (one), and Palmetto GBA (one), according to OIG. Their criteria differ. NGS keeps its terminal-status criteria in a single LCD (L33393), Palmetto publishes disease-specific ones, and as we covered in our look at why polished AI documentation still fails hospice audits, CGS and NGS diverge on conditions such as ALS and renal disease. Reviewers look for documented decline, and for dementia, heart failure, and COPD they look for diagnosis-specific findings alongside PPS. For a COO, that makes one national eligibility template a liability. Your scoring rules need to reflect the LCD language your MAC applies and the diagnosis in the packet. Caregence’s eligibility agent applies criteria that your clinical leaders write in plain English, so the LCD logic is yours to define and update. Ask every vendor, us included, who owns that mapping and how quickly it changes when a MAC revises an LCD. Where does the hospice eligibility agent stop and the physician start? The agent screens. The physician certifies. Under the federal rules, certification rests on the physician’s clinical judgment about the normal course of the illness, and the narrative has to be composed by the physician from the patient’s record. The agent prepares the evidence, checks it for completeness, and scores it. A human approves every determination. Task Who does it Why it sits there Read the packet and extract PPS, prognosis, hospitalizations, decline indicators Agent High volume, repeatable, and OCR handles scanned pages Check that the CTI, narrative, and election statement are complete Agent Rule-based and fully checkable Apply the scoring criteria to every referral Agent Same logic every time removes reviewer variance Write and update the scoring criteria Clinical leadership The platform never sets the clinical standard Judge the prognosis and write the narrative Certifying physician Required by 42 CFR 418.22 Resolve Pending Review cases Clinician Borderline packets need clinical judgment Approve the final status Human reviewer AI scores and explains; a person decides Pending Review is where the design matters. A borderline packet should land in front of a clinician with the gap named, and it shouldn’t be quietly scored up or down to fit a threshold. Which documentation gaps cause eligibility denials, and which can an agent catch? OIG’s June 2026 audit gives a clear breakdown of how initial certification periods fail. Its sample covered fiscal year 2021 claims, so the counts describe failure types and shouldn’t be read as today’s error rate. The same records are what a MAC asks for in an additional documentation request (ADR) or a Targeted Probe and Educate (TPE) review. Failure type in OIG sample (of 100 periods) Count Can an intake agent help? Clinical record did not support a terminal illness 21 Partly. It surfaces decline indicators and flags thin evidence. The physician judges. No supporting records provided 7 Partly. The stored packet and audit trail create a record to produce. Election statement missing 3 Yes. Completeness check at intake. Election statement missing required elements 7 Yes. Element-level check. Certification of terminal illness missing 5 Yes. Completeness check. Certification elements missing, such as signatures 2 Yes. Signature and date check. Seventeen of the 45 failures were election statements or CTIs that were missing or incomplete. A rule-based completeness check at intake addresses those directly. The 21 clinical-support failures stay with the physician, though an agent can pull the decline indicators out of the packet so the narrative has evidence to cite. OIG also flagged new enrollees with no inpatient or emergency room claim in the prior 18 months as a high-risk group, estimated Medicare could have saved $255.1 million had the MACs reviewed that group, and CMS concurred with the recommendation to consider it in eligibility reviews. The finding is claims-based, and a packet shows only what’s documented. Still, a configurable intake rule can route a packet with no recent hospital or ER use to a clinician for a closer look. The pressure is rising on the compliance side too. The CMS FY 2027 hospice final rule, issued July 30, 2026, requires an election statement addendum on non-hospice coverage for every beneficiary at election, and CMS now scores providers with the Service and Spending Variation Index, which uses nine claims-based measures. Each new required field is another item a reviewer can check across every admission. How does the Caregence Hospice Eligibility Agent work? The Caregence Hospice Eligibility Agent runs in five steps. It starts when a referral lands through your intake portal, EHR, or CRM, or through an API call, webhook, or scheduled task. Step What happens Output 1. Get data Pulls the physician certification, face-to-face notes, decline indicators, admission form, and clinical notes from the hospice system Complete referral packet in one place 2. Extract (OCR) Azure Document Intelligence parses scanned and unstructured PDFs Structured values: PPS, prognosis, hospitalizations, decline indicators 3. Score The intelligent agent applies your scoring logic and reasons over gaps Total score, determination, and the factors behind it 4. Update status Writes the determination back to the hospice system and portal record Eligible, Pending Review, or Ineligible 5. Notify Emails the recipients you configured Clinician sees score breakdown and notes Inferenz reports under five minutes per determination, against 30 to 90 minutes of manual clinical review. In the example Inferenz uses, a 25-person intake team can properly review about 75 referrals a day, and some days bring 500. Run the numbers on your own volume. What does the agent extract, and how transparent is the score? By default it scores terminal prognosis, PPS, documented functional decline, hospitalization history over the past six months, and documentation completeness. Each criterion carries a weight, the agent totals the points, and it returns the factors behind the total. A clinician can see why a packet landed in Pending Review without reopening all 38 pages. Can you set your own criteria, or are you stuck with vendor defaults? The defaults are a starting point. Clinical staff edit the weights, thresholds, mandatory documents, and routing in plain English, and a change goes live when saved, with no developer ticket. That speed needs a guardrail: every edit should have a named owner and a date, so you can show which rules were live the day a patient was admitted. What does the second workflow add? Eligibility tells you who qualifies. A second workflow scores eligible referrals on their likelihood of becoming admissions, using your own history: diagnosis fit, referral source, geography, caregiver availability, and documentation completeness. The coordinator still decides, and the score runs only on referrals already marked eligible. Caregence sits above your existing systems as an orchestration layer on the Caregence platform, so there’s no migration. Dimension Manual intake Caregence (Inferenz-reported) Time per determination 30 to 90 minutes Under 5 minutes Scoring consistency Varies by reviewer and by day Same logic on every referral Changing the criteria IT ticket and a development cycle Text edit, live on save Prioritization Intuition and whoever called last Conversion probability with reasoning Audit evidence Reconstructed after the fact Timestamped at every step Image suggestion Workflow diagram: referral arrives, five Caregence steps, human approval, status written back to the EHR, with the audit log running underneath. Alt text: Caregence hospice eligibility agent five-step workflow What audit trail does the agent leave for a reviewer? Every workflow step is timestamped against the patient record: the inputs pulled, the logic applied, the score produced, the decision written, and the notification sent. That gives you one consistent record per referral and removes the reviewer-by-reviewer variance that audits penalize. Push those determinations into your reporting layer too. An audit-ready dashboard connects each compliance number to the patient-level evidence behind it, and our guide to building audit-ready dashboards for CMS reviews shows how to wire that up. When a records request arrives, your team answers from one screen. What should a COO or CIO ask before choosing a hospice eligibility AI? Some hospice AI tools read well and still fail in practice. They misread ambiguous clinical language, or they apply the wrong standard for your jurisdiction. A 2026 PLOS Digital Health study shows the right habit. Researchers used self-hosted language models to extract prognostic indicators from the notes of 2,708 lung cancer and 814 colon cancer patients, then validated the extracted features against structured EHR data and physician annotations. The study covered oncology notes. Its method transfers to hospice packets; its accuracy figures don’t. Question to ask What good looks like Red flag Who writes the eligibility criteria? Your clinical leaders, in plain language, with change history Vendor-locked rules; changes need a ticket How does it handle LCD variation by MAC? Criteria mapped to your MAC and diagnosis, with a named owner and update process One national template Can it explain every score? Factor-level breakdown on each referral A single opaque number How is extraction accuracy measured? Tested on a sample of your own packets against clinician-confirmed values Demo accuracy only Where does the human sit? A person approves; borderline cases route to Pending Review Auto-admits or auto-declines What protects PHI? BAA, retention terms in writing, minimum-necessary access, audit logs Verbal assurances How does it connect to our systems? Triggers from portal, API, or webhook; writes status back; no migration Requires replacing your portal What audit evidence can you export? Timestamped inputs, logic, score, and decision per referral A summary report only On safeguards, ask for the business associate agreement and the data-retention terms in writing. Caregence’s platform design applies minimum-necessary access, role-based permissions, and audit logging across its agents, and your contract should spell out how that applies to your data. How do you connect the agent to your EMR and recertification workflow? The agent is portal-agnostic. A button click, a form submission, an API call, a webhook, or a scheduled run can trigger it, and the result is written back to the hospice system and portal record, so intake staff keep working in the tools they know. That makes EHR and referral data integration the real project. Check that your billing, EHR, and referral data agree on patient identity and dates before go-live. Data readiness decides how well any of this works. Most hospice AI projects stall without it, and a missing admission date or a duplicated patient record turns into a wrong determination. Recertification follows the same pattern. Scheduled runs are a documented trigger, so a nightly sweep of patients approaching a benefit-period boundary can flag a missing face-to-face attestation or an absent recertification narrative before the claim goes out. Confirm that scope during scoping, since the published workflow centers on referral screening. How do you measure the return on automated eligibility checks? Start with the Inferenz-reported figures and your own volume. At 75 referrals a day and 30 minutes per manual review, your clinicians spend 37.5 hours a day on first-pass review. If the agent returns each determination in under five minutes and a clinician only reviews the score and the flags, that burden shrinks to a fraction. Measure the fraction in your own pilot. Our guide to referral intake delays lists six baseline metrics worth capturing first. • Referral-to-determination time: hours from packet arrival to status. • First-pass completeness: share of packets with CTI, narrative, and election statement in order on day one. • Reviewer variance: score spread when two clinicians review the same packets. • Pending Review rate and time to clear: how many packets need a clinician and how fast. • Denial and ADR outcomes: documentation-related findings per quarter. • Referral-source rework: requests back to hospitals and SNFs for missing documents. How do you pilot a hospice eligibility agent in 90 days? 1. Days 1 to 15: Pull one week of past referrals with the decisions your team made. Write the scoring criteria in plain English with your clinical leads. 2. Days 16 to 45: Run in shadow mode. Compare agent determinations with past decisions, and have two clinicians score the same packets to measure human variance. 3. Days 46 to 75: Go live on one branch or service line, with a person approving every determination. 4. Days 76 to 90: Review the metrics, tune weights, record who owns each rule, and decide on rollout. A strong data layer speeds all four steps. A post-acute care provider that worked with Inferenz unified multiple EMRs, a triage platform, and a state HIE on one governed Snowflake warehouse with a master patient index, and leadership recovered two hours a day from manual spreadsheet audits (Inferenz-reported). Final thoughts Eligibility decisions carry the most weight in hospice. They decide who gets care, and they decide what survives a review. An agent can read every packet the same way, every time, and tell your team exactly what’s missing. It can’t replace the physician’s judgment, and it shouldn’t try. The hospices that get this right will write their own rules, keep a person on every determination, and keep the receipts.


What do CMS hospice eligibility criteria require at intake?

The federal rules at 42 CFR 418.22 set the documentation standard that most intake errors trace back to. The table maps each requirement to what an agent can check and who makes the call.

RequirementWhat CMS expectsWhat the agent can checkWho decides
Six-month prognosisCertification that life expectancy is six months or less if the illness runs its normal courseStatement is present; supporting clinical findings are in the packetCertifying physician
Who certifiesFor the first 90 days: medical director, physician designee, or an IDG physician, plus the attending physician if there is oneRequired signatures and dates are presentPhysicians
TimingWritten certification before the claim; oral certification within 2 calendar days if the written one isn’t in hand; up to 15 calendar days before the election dateCertification dates against the election dateHospice admin staff
NarrativeBrief, patient-specific explanation of clinical findings. No check boxes or standard language. Signature and attestation in the right placeNarrative is present, placed correctly, and signedCertifying physician
Face-to-face encounterRequired before the third benefit period and each recertification after it, no more than 30 days prior, by a hospice physician or nurse practitioner, with a signed attestationDated, signed attestation is in the recordHospice physician or NP
Election statementNames the hospice and attending physician, acknowledges care is palliative, carries the patient’s signatureEach element is presentPatient or representative, hospice staff
Election statement addendumFY 2027 final rule: addendum on non-hospice service coverage for every beneficiary at electionYes or no field is completeHospice staff
Benefit periodsTwo 90-day periods, then unlimited 60-day periods, each needing certificationWhich period applies and what is dueHospice staff

What is a certification of terminal illness (CTI)?

A CTI is the physician’s signed statement that the patient’s life expectancy is six months or less if the illness runs its normal course. It needs a patient-specific narrative of the clinical findings, a signature and date, and the dates of the benefit period it covers.

Who certifies hospice eligibility?

Physicians do. OIG’s report notes that only a Doctor of Medicine or Osteopathy can certify or recertify a terminal illness. For the first 90 days that means the hospice medical director, physician designee, or an interdisciplinary group physician, and the attending physician if the patient has one.

What is a face-to-face encounter, and when is it required?

It’s an in-person visit by a hospice physician or nurse practitioner to gather clinical findings on continued eligibility. It’s required before the third benefit period and before every recertification after that, no more than 30 days ahead, with a signed and dated attestation.

How do LCDs and MAC jurisdiction change the eligibility check?

A local coverage determination (LCD) is a Medicare Administrative Contractor’s published criteria for when a service is reasonable and necessary. For hospice, LCDs define terminal status by diagnosis. Three MACs cover four home health and hospice jurisdictions: National Government Services (two), CGS Administrators (one), and Palmetto GBA (one), according to OIG.

Their criteria differ. NGS keeps its terminal-status criteria in a single LCD (L33393), Palmetto publishes disease-specific ones, and as we covered in our look at why polished AI documentation still fails hospice audits, CGS and NGS diverge on conditions such as ALS and renal disease. Reviewers look for documented decline, and for dementia, heart failure, and COPD they look for diagnosis-specific findings alongside PPS.

For a COO, that makes one national eligibility template a liability. Your scoring rules need to reflect the LCD language your MAC applies and the diagnosis in the packet. Caregence’s eligibility agent applies criteria that your clinical leaders write in plain English, so the LCD logic is yours to define and update. Ask every vendor, us included, who owns that mapping and how quickly it changes when a MAC revises an LCD.

Where does the hospice eligibility agent stop and the physician start?

The agent screens. The physician certifies. Under the federal rules, certification rests on the physician’s clinical judgment about the normal course of the illness, and the narrative has to be composed by the physician from the patient’s record. The agent prepares the evidence, checks it for completeness, and scores it. A human approves every determination.

TaskWho does itWhy it sits there
Read the packet and extract PPS, prognosis, hospitalizations, decline indicatorsAgentHigh volume, repeatable, and OCR handles scanned pages
Check that the CTI, narrative, and election statement are completeAgentRule-based and fully checkable
Apply the scoring criteria to every referralAgentSame logic every time removes reviewer variance
Write and update the scoring criteriaClinical leadershipThe platform never sets the clinical standard
Judge the prognosis and write the narrativeCertifying physicianRequired by 42 CFR 418.22
Resolve Pending Review casesClinicianBorderline packets need clinical judgment
Approve the final statusHuman reviewerAI scores and explains; a person decides

Pending Review is where the design matters. A borderline packet should land in front of a clinician with the gap named, and it shouldn’t be quietly scored up or down to fit a threshold.

Which documentation gaps cause eligibility denials, and which can an agent catch?

OIG’s June 2026 audit gives a clear breakdown of how initial certification periods fail. Its sample covered fiscal year 2021 claims, so the counts describe failure types and shouldn’t be read as today’s error rate. The same records are what a MAC asks for in an additional documentation request (ADR) or a Targeted Probe and Educate (TPE) review.

Failure type in OIG sample (of 100 periods)CountCan an intake agent help?
Clinical record did not support a terminal illness21Partly. It surfaces decline indicators and flags thin evidence. The physician judges.
No supporting records provided7Partly. The stored packet and audit trail create a record to produce.
Election statement missing3Yes. Completeness check at intake.
Election statement missing required elements7Yes. Element-level check.
Certification of terminal illness missing5Yes. Completeness check.
Certification elements missing, such as signatures2Yes. Signature and date check.

Seventeen of the 45 failures were election statements or CTIs that were missing or incomplete. A rule-based completeness check at intake addresses those directly. The 21 clinical-support failures stay with the physician, though an agent can pull the decline indicators out of the packet so the narrative has evidence to cite.

OIG also flagged new enrollees with no inpatient or emergency room claim in the prior 18 months as a high-risk group, estimated Medicare could have saved $255.1 million had the MACs reviewed that group, and CMS concurred with the recommendation to consider it in eligibility reviews. The finding is claims-based, and a packet shows only what’s documented. Still, a configurable intake rule can route a packet with no recent hospital or ER use to a clinician for a closer look.

The pressure is rising on the compliance side too. The CMS FY 2027 hospice final rule, issued July 30, 2026, requires an election statement addendum on non-hospice coverage for every beneficiary at election, and CMS now scores providers with the Service and Spending Variation Index, which uses nine claims-based measures. Each new required field is another item a reviewer can check across every admission.

How does the Caregence Hospice Eligibility Agent work?

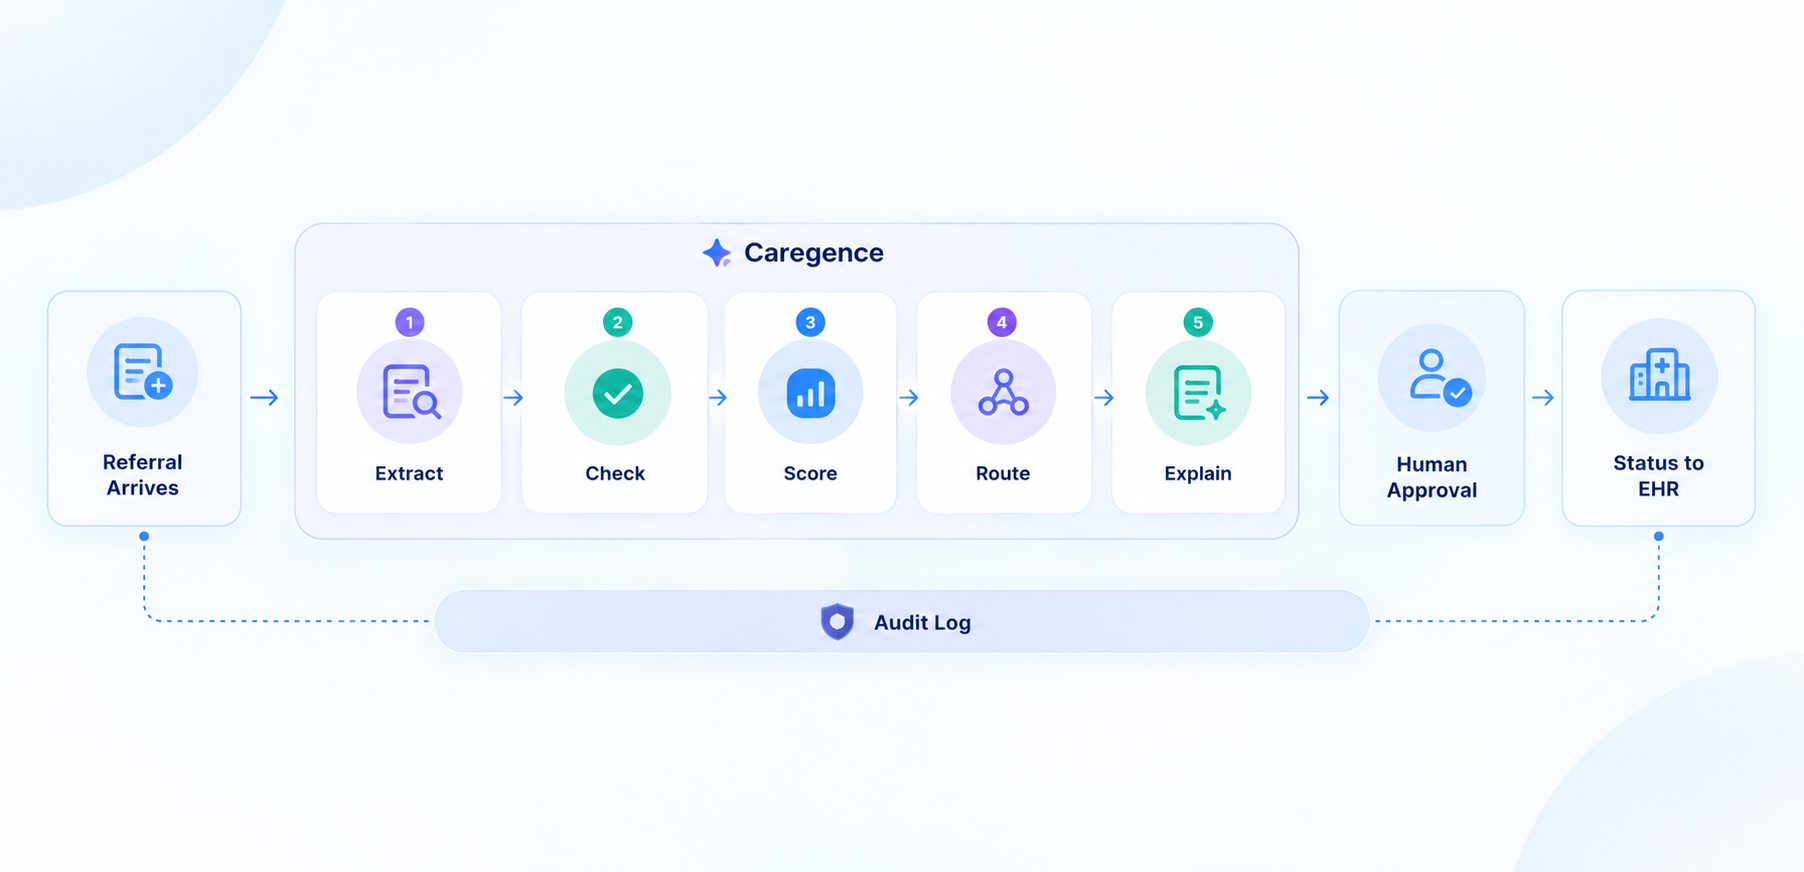
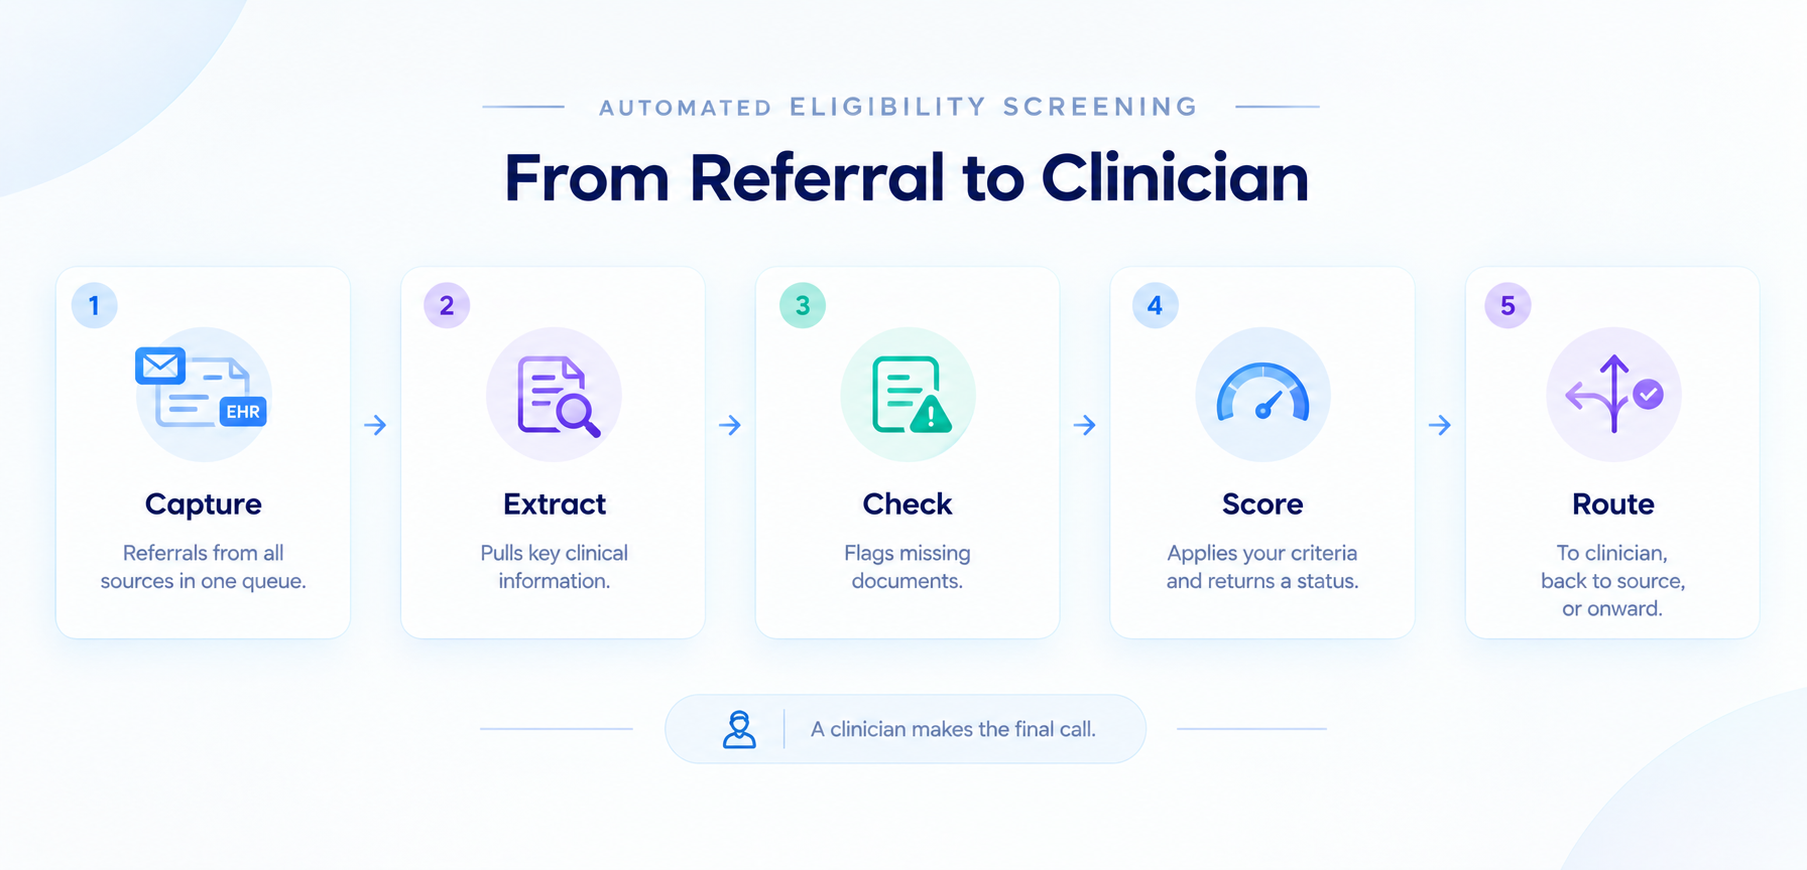
The Caregence Hospice Eligibility Agent runs in five steps. It starts when a referral lands through your intake portal, EHR, or CRM, or through an API call, webhook, or scheduled task.

StepWhat happensOutput
1. Get dataPulls the physician certification, face-to-face notes, decline indicators, admission form, and clinical notes from the hospice systemComplete referral packet in one place
2. Extract (OCR)Azure Document Intelligence parses scanned and unstructured PDFsStructured values: PPS, prognosis, hospitalizations, decline indicators
3. ScoreThe intelligent agent applies your scoring logic and reasons over gapsTotal score, determination, and the factors behind it
4. Update statusWrites the determination back to the hospice system and portal recordEligible, Pending Review, or Ineligible
5. NotifyEmails the recipients you configuredClinician sees score breakdown and notes

Inferenz reports under five minutes per determination, against 30 to 90 minutes of manual clinical review. In the example Inferenz uses, a 25-person intake team can properly review about 75 referrals a day, and some days bring 500. Run the numbers on your own volume.

What does the agent extract, and how transparent is the score?

By default it scores terminal prognosis, PPS, documented functional decline, hospitalization history over the past six months, and documentation completeness. Each criterion carries a weight, the agent totals the points, and it returns the factors behind the total. A clinician can see why a packet landed in Pending Review without reopening all 38 pages.

Can you set your own criteria, or are you stuck with vendor defaults?

The defaults are a starting point. Clinical staff edit the weights, thresholds, mandatory documents, and routing in plain English, and a change goes live when saved, with no developer ticket. That speed needs a guardrail: every edit should have a named owner and a date, so you can show which rules were live the day a patient was admitted.

What does the second workflow add?

Eligibility tells you who qualifies. A second workflow scores eligible referrals on their likelihood of becoming admissions, using your own history: diagnosis fit, referral source, geography, caregiver availability, and documentation completeness. The coordinator still decides, and the score runs only on referrals already marked eligible. Caregence sits above your existing systems as an orchestration layer on the Caregence platform, so there’s no migration.

DimensionManual intakeCaregence (Inferenz-reported)
Time per determination30 to 90 minutesUnder 5 minutes
Scoring consistencyVaries by reviewer and by daySame logic on every referral
Changing the criteriaIT ticket and a development cycleText edit, live on save
PrioritizationIntuition and whoever called lastConversion probability with reasoning
Audit evidenceReconstructed after the factTimestamped at every step

Caregence hospice eligibility agent five-step workflowWhat audit trail does the agent leave for a reviewer?

Every workflow step is timestamped against the patient record: the inputs pulled, the logic applied, the score produced, the decision written, and the notification sent. That gives you one consistent record per referral and removes the reviewer-by-reviewer variance that audits penalize.

Push those determinations into your reporting layer too. An audit-ready dashboard connects each compliance number to the patient-level evidence behind it, and our guide to building audit-ready dashboards for CMS reviews shows how to wire that up. When a records request arrives, your team answers from one screen.

What should a COO or CIO ask before choosing a hospice eligibility AI?

Some hospice AI tools read well and still fail in practice. They misread ambiguous clinical language, or they apply the wrong standard for your jurisdiction. A 2026 PLOS Digital Health study shows the right habit. Researchers used self-hosted language models to extract prognostic indicators from the notes of 2,708 lung cancer and 814 colon cancer patients, then validated the extracted features against structured EHR data and physician annotations. The study covered oncology notes. Its method transfers to hospice packets; its accuracy figures don’t.

Question to askWhat good looks likeRed flag
Who writes the eligibility criteria?Your clinical leaders, in plain language, with change historyVendor-locked rules; changes need a ticket
How does it handle LCD variation by MAC?Criteria mapped to your MAC and diagnosis, with a named owner and update processOne national template
Can it explain every score?Factor-level breakdown on each referralA single opaque number
How is extraction accuracy measured?Tested on a sample of your own packets against clinician-confirmed valuesDemo accuracy only
Where does the human sit?A person approves; borderline cases route to Pending ReviewAuto-admits or auto-declines
What protects PHI?BAA, retention terms in writing, minimum-necessary access, audit logsVerbal assurances
How does it connect to our systems?Triggers from portal, API, or webhook; writes status back; no migrationRequires replacing your portal
What audit evidence can you export?Timestamped inputs, logic, score, and decision per referralA summary report only

On safeguards, ask for the business associate agreement and the data-retention terms in writing. Caregence’s platform design applies minimum-necessary access, role-based permissions, and audit logging across its agents, and your contract should spell out how that applies to your data.

How do you connect the agent to your EMR and recertification workflow?

The agent is portal-agnostic. A button click, a form submission, an API call, a webhook, or a scheduled run can trigger it, and the result is written back to the hospice system and portal record, so intake staff keep working in the tools they know. That makes EHR and referral data integration the real project. Check that your billing, EHR, and referral data agree on patient identity and dates before go-live.

Data readiness decides how well any of this works. Most hospice AI projects stall without it, and a missing admission date or a duplicated patient record turns into a wrong determination.

Recertification follows the same pattern. Scheduled runs are a documented trigger, so a nightly sweep of patients approaching a benefit-period boundary can flag a missing face-to-face attestation or an absent recertification narrative before the claim goes out. Confirm that scope during scoping, since the published workflow centers on referral screening.

How do you measure the return on automated eligibility checks?

Start with the Inferenz-reported figures and your own volume. At 75 referrals a day and 30 minutes per manual review, your clinicians spend 37.5 hours a day on first-pass review. If the agent returns each determination in under five minutes and a clinician only reviews the score and the flags, that burden shrinks to a fraction. Measure the fraction in your own pilot. Our guide to referral intake delays lists six baseline metrics worth capturing first.

  • Referral-to-determination time: hours from packet arrival to status.
  • First-pass completeness: share of packets with CTI, narrative, and election statement in order on day one.
  • Reviewer variance: score spread when two clinicians review the same packets.
  • Pending Review rate and time to clear: how many packets need a clinician and how fast.
  • Denial and ADR outcomes: documentation-related findings per quarter.
  • Referral-source rework: requests back to hospitals and SNFs for missing documents.

How do you pilot a hospice eligibility agent in 90 days?

  1. Days 1 to 15: Pull one week of past referrals with the decisions your team made. Write the scoring criteria in plain English with your clinical leads.
  2. Days 16 to 45: Run in shadow mode. Compare agent determinations with past decisions, and have two clinicians score the same packets to measure human variance.
  3. Days 46 to 75: Go live on one branch or service line, with a person approving every determination.
  4. Days 76 to 90: Review the metrics, tune weights, record who owns each rule, and decide on rollout.

A strong data layer speeds all four steps. A post-acute care provider that worked with Inferenz unified multiple EMRs, a triage platform, and a state HIE on one governed Snowflake warehouse with a master patient index, and leadership recovered two hours a day from manual spreadsheet audits (Inferenz-reported).

Final thoughts

Eligibility decisions carry the most weight in hospice. They decide who gets care, and they decide what survives a review. An agent can read every packet the same way, every time, and tell your team exactly what’s missing. It can’t replace the physician’s judgment, and it shouldn’t try. The hospices that get this right will write their own rules, keep a person on every determination, and keep the receipts.

Test it on your own referrals

Frequently Asked Questions

Building Audit-Ready Dashboards for CMS and Compliance Reviews

An audit-ready dashboard ties every compliance number to the patient record behind it. Learn what CMS and OIG reviewers check in 2026, which KPIs to track, and how to build the trail.

CMS now publishes provider-level hospice scores. The Service and Spending Variation Index uses nine claims-based measures, so a reviewer can spot your pattern before you’ve pulled a single record.

This article is the reporting step in our series on predictive analytics for hospice operations, written for CEOs and COOs who need an answer ready when a reviewer asks.

An audit-ready dashboard connects each compliance metric to the patient-level evidence behind it. For hospice care agencies, that means the hospice team can answer a record request from one screen. The sections below cover what to track, how to trace it, and where AI-powered automation for hospice fits.

What is an audit-ready dashboard in healthcare?

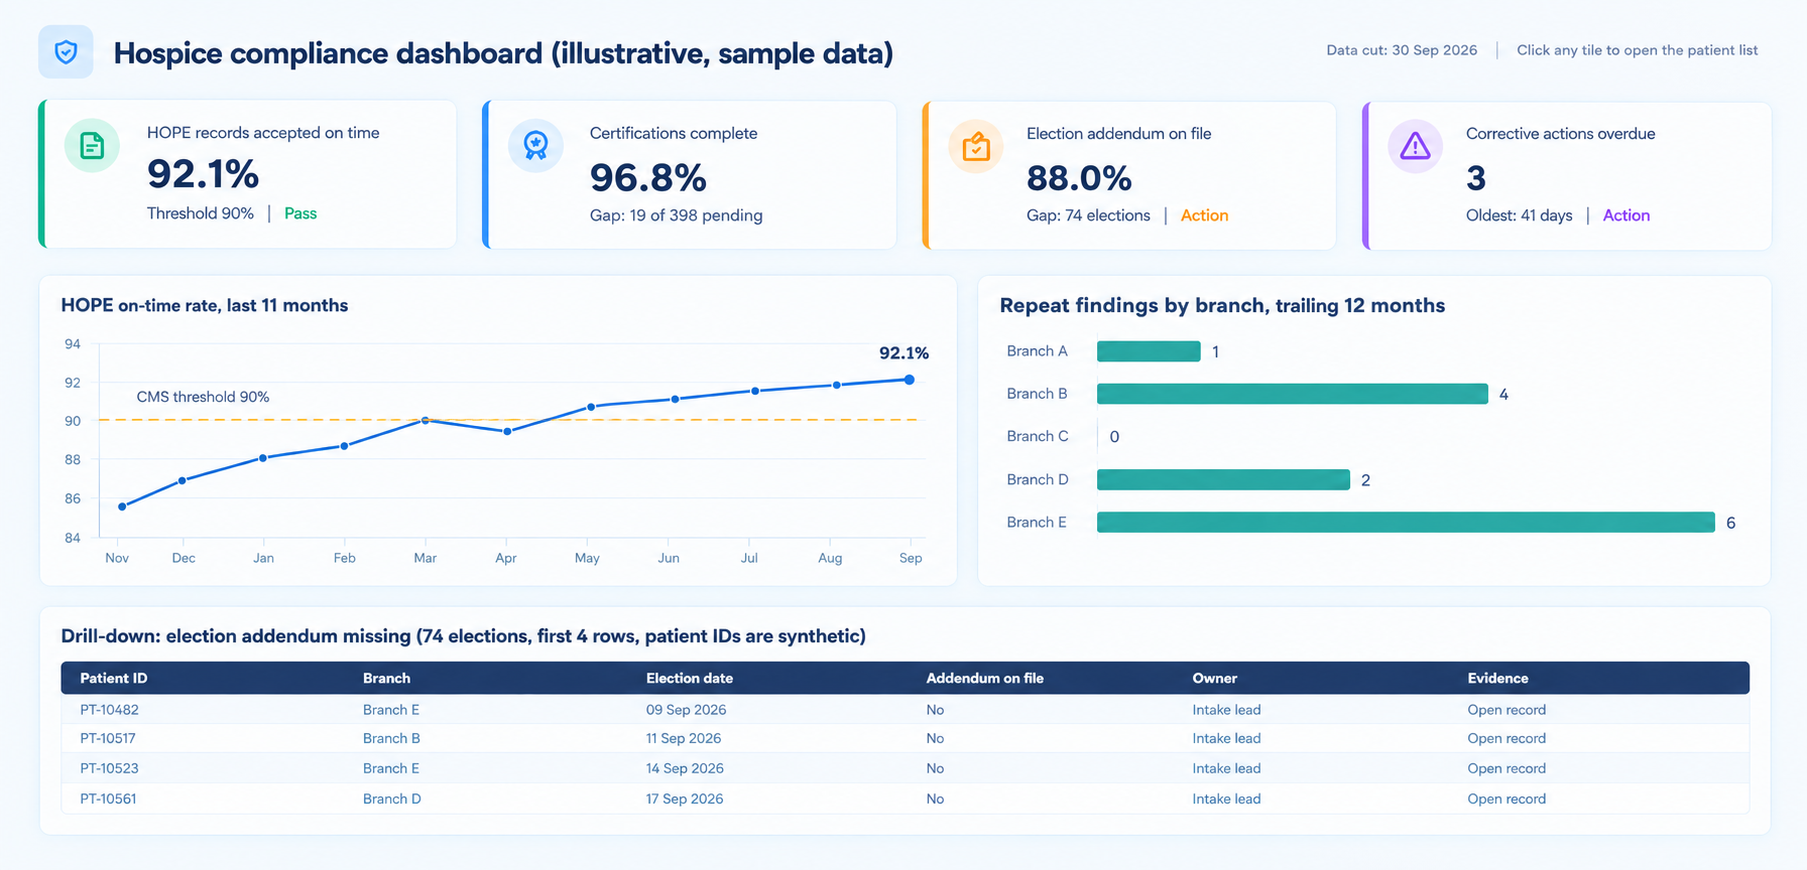
An audit-ready dashboard in healthcare is a reporting view where every tile opens to the patients, records, and rules behind the number. It carries a data cut date, a named owner, and a saved history. A reviewer can test it without asking your team to rebuild anything.

Summary dashboards show how you’re doing. Audit-ready dashboards show how you know. Continuous audit readiness means the dashboard holds that standard every month, including the months nobody is asking.

DimensionSummary dashboardAudit-ready dashboard
What a tile showsA percentage or a countThe percentage plus the list of patients behind it
Drill-downStops at the aggregateOpens to the source record
Data cut dateOften missingPrinted on every tile
DefinitionsDiffer by teamOne dictionary, versioned
HistoryOverwritten at each refreshMonthly snapshots saved
Who it satisfiesThe Monday meetingThe board, a reviewer, and a buyer

What are CMS and its contractors reviewing in 2026?

Four pressures shape hospice reviews this year. Each calls for a different tile.

Review pressureWhat reviewers checkWhat your dashboard needs
Claims pattern analyticsThe Service and Spending Variation Index (SSVI) scores utilization and non-hospice spending. Provider-level data is published, and a higher score signals potentially concerning patterns.Your own monitoring of non-hospice spending and utilization by branch and patient, run before CMS publishes its next update.
Eligibility and certification recordsWhether the chart supports a terminal prognosis and meets documentation rules.Certification completeness, a clinician review queue, and a flag for admissions with no hospital or emergency visit in the prior 18 months.

HOPE quality reportingAt least 90% of HOPE records submitted within 30 days of admission, update visits, and discharge.HOPE timeliness by branch and assessment type, with a countdown for records approaching day 30.

Billing compliance samplesA sample of claims, such as OIG’s 100-claim samples, tested against Medicare rules.Sampled claim accuracy by branch and error type, plus policy adherence.

The numbers behind these rows are specific. In FY 2026, 20.37% of hospices missed the HOPE reporting requirement, and the FY 2027 final rule adds a Care Compare icon for them, effective no earlier than FY 2028. Missing the requirement also cuts the payment update by four percentage points, which turns a 2.3% increase into a 1.7% reduction.

The same rule makes the election statement addendum mandatory for every beneficiary who elects hospice. Before, hospices issued it on request. That adds a yes-or-no field to every election, and a reviewer can check all of them.

Record-level review has teeth too. In a June 2026 audit, OIG reviewed 100 initial certification periods for new hospice enrollees and found that 45 did not meet Medicare requirements. In 21, the medical record did not support a terminal illness. In 24, the documentation requirements went unmet. OIG flagged new enrollees with no inpatient or emergency room claims in the prior 18 months as a high-risk group, estimated Medicare could have saved $255.1 million, and CMS concurred with its recommendation.

Why do dashboards that look fine internally fail when reviewers ask for patient-level evidence?

A rate can’t answer a records request. Reviewers sample patients, and a summary tile doesn’t say which patients sit behind it.

Sampling also multiplies small errors. In a July 2026 audit, OIG tested 100 claims from Hospice of the Valley West and found 15 non-compliant, worth $69,184 in overpayments over a two-year audit period. From that sample, OIG estimated at least $8.6 million in unallowable payments out of $86 million paid. The errors occurred primarily because the hospice did not always follow its own policies and procedures.

A dashboard that reports 94% compliance says nothing about which 6% failed or why. Three gaps cause most of the trouble:

  • No patient list behind the percentage, so nobody can find the failures.
  • No as-of date, so the number can’t be reproduced for a past period.
  • Definitions that differ from billing, so a reviewer who recomputes the metric gets a different answer.

One distinction matters for the OIG findings. A dashboard can automate completeness checks, such as whether a signature, a date, and a narrative exist. It can’t judge whether the narrative supports the prognosis. Build a clinician review queue for that second test and log who reviewed which record.

Eligibility evidence starts at intake

What KPIs should a hospice compliance dashboard include?

A healthcare compliance KPI dashboard works when each KPI has a definition, a source, and a reason a reviewer would ask about it. Ten KPIs cover the pressures above.

KPIDefinitionSourceWhy a reviewer cares
HOPE on-time rateRecords accepted within 30 days (admission, update visit, discharge). Aim above 90%.iQIES, EHRCMS threshold. Icon on Care Compare from FY 2028 at the earliest.
Certification completenessPeriods with signed certification, narrative, and required elements before the claim.EHR, billingOIG found 45 of 100 periods deficient.
Narrative review rateCertification narratives reviewed by a clinician against the prognosis.EHR review logTests clinical support as well as completeness.
Election addendum on fileElections with the addendum delivered at election.EHRMandatory for every election under the FY 2027 rule.
Non-hospice spendingMedicare spending outside hospice for patients on service, by branch.ClaimsA core concern behind the SSVI.
Live dischargesRate and reason mix by branch.EHR, claimsUnusual patterns draw questions.
Aggregate cap positionProjected payments against allowance. The FY 2027 cap is $36,174.75 per beneficiary.Claims, PS&RTies the dashboard to the forecast.
Corrective action closureShare closed on time, items reopened, repeat findings.Action registerShows whether fixes hold.
Policy adherenceSampled records that follow your own policy.Mock auditPolicy gaps drove the Hospice of the Valley West errors.
Evidence retrieval timeHours to assemble a full record set for one sampled patient.Mock auditReveals how scattered your evidence is.

The last four rows serve as compliance program effectiveness metrics. They answer whether the program works, which differs from whether policies exist.

How do you make every dashboard number traceable to source data?

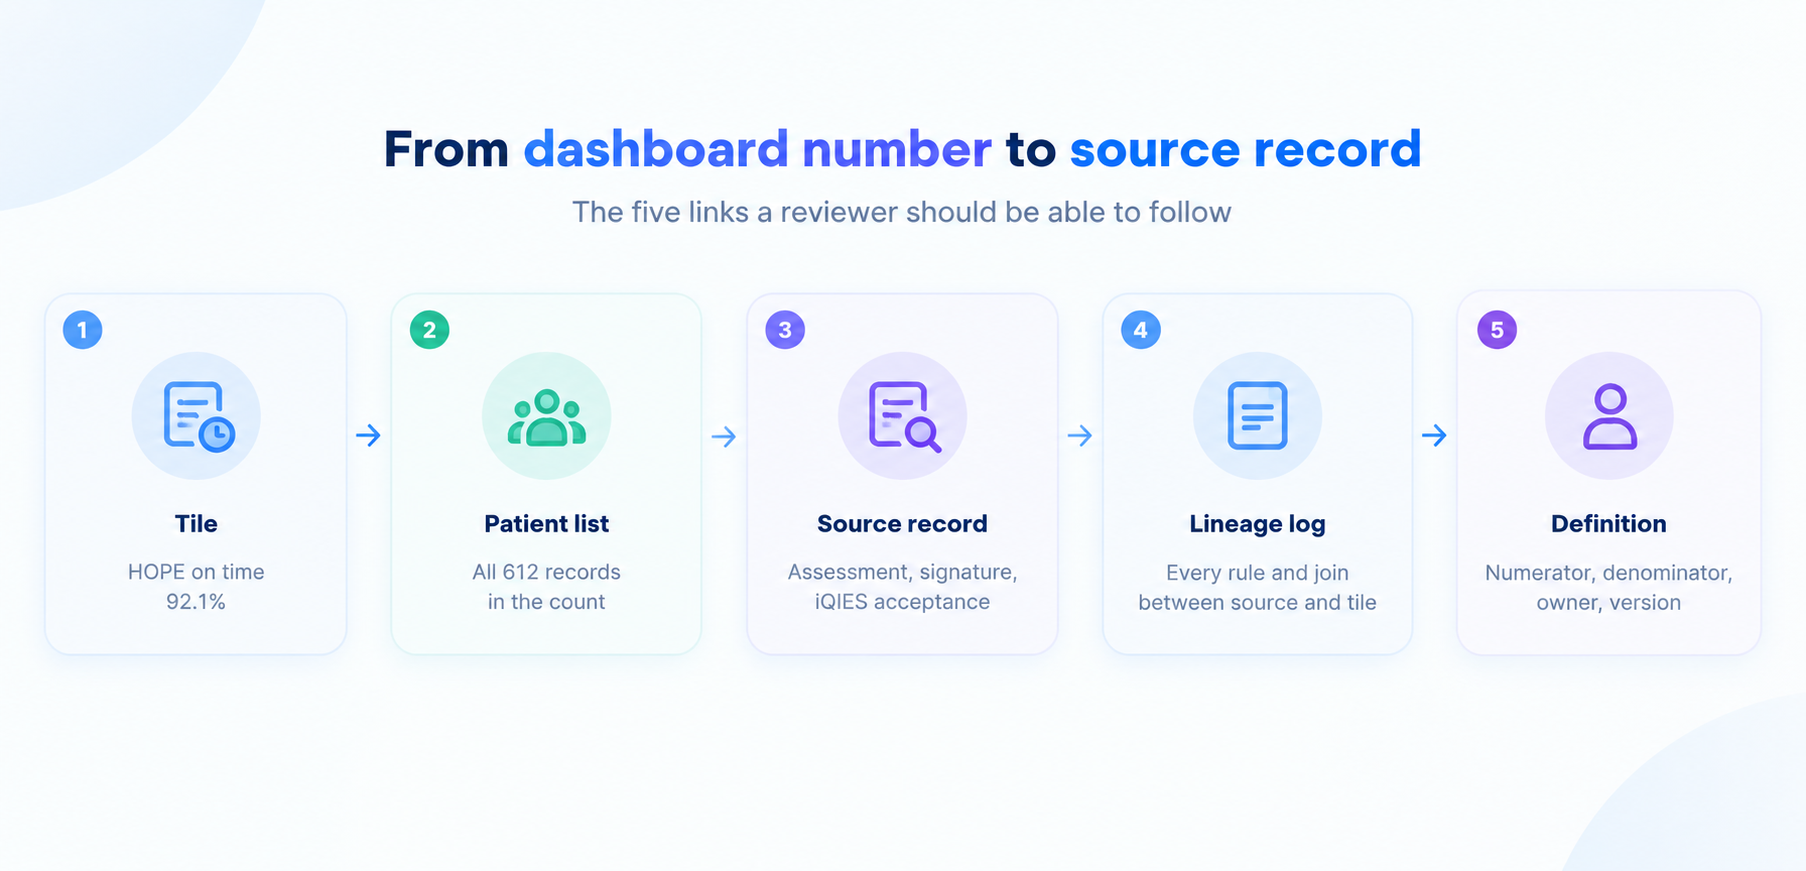
Give every tile a five-link chain. A reviewer should be able to walk it from the headline number to the document that proves it.

The five-link evidence chain behind each dashboard tile. Sample figures for illustration.

  1. Tile: the headline number with its as-of date.
  2. Patient list: every record counted, with exclusions listed separately.
  3. Source record: the assessment, signature, claim, or iQIES acceptance that proves the status.
  4. Lineage log: each rule, join, and correction between the source system and the tile.
  5. Definition: numerator, denominator, owner, and version.

The chain starts at referral intake, what vendors call the digital front door in healthcare, because election and certification paperwork begins there.

Data lineage behind dashboard metrics is the fourth link, and reviewers find it the hardest to improvise. Our guide to audit-ready data lineage shows how to record it without replacing your current systems.

Tracing doesn’t have to slow reporting. Store the patient-level detail table beside each aggregate in the gold layer and refresh both on the same schedule. Drill-down becomes a query, with no project attached.

What is the difference between a compliance dashboard and an audit-ready evidence system?

A compliance dashboard tells operations what to fix this week. An evidence system proves what was true on a given date. Reviewers ask the second question, usually about a period that closed months ago.

Point-in-time vs real-time compliance view

DimensionReal-time compliance viewPoint-in-time evidence snapshot
Question answeredWhat needs attention today?What was true on the date of service or submission?
RefreshContinuous or dailyFrozen monthly and at each submission
AudienceBranch managers and the compliance leadReviewers, the board, and buyers
Main riskNumbers change under youGoes stale without a live view beside it
Best forOperational fixesRecord requests and mock audits

Run both. Freeze a snapshot at month end, store the inputs and the rules, and let the live view keep working. The live view catches problems, and the snapshot proves the past. Together they deliver audit-ready reporting for CMS reviews.

An illustrative audit-ready dashboard using sample data. Every tile opens to the patient list behind it.

How should hospices track corrective action plans so repeat findings don’t become systemic?

Treat every finding as a record with an owner and a clock. A corrective action plan monitoring dashboard should pull findings from every source: internal audits, contractor letters, OIG recommendations, and survey results.

  1. Log the finding with its source, date, and the records affected.
  2. Name the root cause category, such as training, workflow, system, or policy.
  3. Assign one owner and a due date.
  4. Attach proof of the fix, such as a changed workflow or a retraining roster.
  5. Retest at 30, 60, and 90 days on a fresh sample and record the result.

Show open items by age, overdue items, reopened items, and repeat findings by branch and root cause. The Hospice of the Valley West report shows what the retest step guards against. Among its recommendations, OIG suggested internal audits of later claims to find similar overpayments and added training for clinical staff on validating the terminal prognosis.

How do multi-site hospices run one compliance view across branches and contracted providers?

A multi-site compliance dashboard works only when every branch uses the same definitions. Roll up to the organization, then let a leader click down to a branch, a team, and a patient. A branch with six repeat findings beside a branch with none shows where to look first.

Where contracted providers fit

Contracted providers belong on the same screen. Hospices keep professional management responsibility for care delivered under contract, so track credential currency, contract review dates, and any findings tied to those providers in the same register.

How early should a hospice run a mock audit?

Run one every quarter and run the first before you need it. A mock audit pulls a sample, tests whether the hospice team can assemble each record, and checks three things: whether the narrative supports the prognosis, whether certifications were complete before the claim, and whether the addendum reached the family at election.

Validate the record population first

Reconcile patient, claim, and day counts between clinical and billing systems each month, so the numbers tie before anyone asks. As a starting point, try 25 records per branch each quarter, then adjust to your risk. OIG’s 2026 audits each reviewed a sample of 100, so test your own records the same way.

Where do AI in hospice care and automation fit in an audit-ready dashboard?

AI in hospice care earns a place on the compliance side when it takes over repetitive checking and leaves judgment with clinicians. AI-powered automation for hospice can run these jobs every night:

  • Reconcile HOPE records against iQIES acceptance.
  • Flag missing addenda and incomplete certifications on the day they occur.
  • Assemble the evidence pack for a sampled patient from the five-link chain.
  • Draft the corrective action entry for a steward to review.

Keep a human at the final decision. Log each AI suggestion, the reviewer, the decision, and the timestamp, so the dashboard can show that a clinician confirmed eligibility and signed the certification. Reviewers ask who decided, and the log answers.

Should you buy an audit management platform or build on your existing data stack?

Both paths work. The test is whether the tool meets the standard above. Ask every option these six questions:

  • Does every tile open to a patient list?
  • Does it save dated snapshots?
  • Can it export a reviewer-ready evidence pack?
  • Can your clinicians edit rules without a developer ticket?
  • Does it restrict PHI access by role?
  • Does it log automated suggestions and human decisions?

Teams with a governed data layer often build on it, because the lineage already exists. Smaller teams may buy. Vendors that sell value based care software or quality reporting tools now add compliance modules, so ask each one to demonstrate the checklist on your own records. For in-house builds, a data partner offering business intelligence and visualization services can shorten the work.

How do you explain dashboard methodology to a board, an auditor, and a regulator in one document?

Write one metric card per KPI. Each card lists the definition, numerator, denominator, source system, owner, refresh time, version, and known limits. The board reads the headline and the trend, the auditor reads the definition and source, and the regulator reads the lineage appendix. One document serves all three at different depths.

A 90-day plan for your hospice team

  1. Days 1 to 30: Name an owner for each KPI, write the metric cards, and list where certification, election, and HOPE evidence lives.
  2. Days 31 to 60: Build patient-level drill-down for the top five KPIs and start monthly snapshots.
  3. Days 61 to 90: Run the first mock audit, open the corrective action register, and review results with your board or compliance committee.

Final Thoughts

Reviewers ask which patients are in the number. If your hospice team can answer from one screen, a CMS review becomes a records exercise your team has already rehearsed.

Start with the five-link chain for one KPI, HOPE timeliness, since the 90% threshold gives you a clear pass line. Add certifications next, then the election addendum.

Ready to make every dashboard number traceable?

Frequently Asked Questions

Home Health Staffing Analytics: Capacity Planning for Home-Based Care Networks

Summary

Home health staffing analytics shows home-based care networks where visit capacity leaks: turnover, scheduling friction, drive time, and documentation load. This guide covers capacity planning, workforce forecasting, burnout signals, and referral conversion, so COOs can match staffing to demand across home health, home care, and hospice.

Introduction

A hospital can count its empty beds. A home health agency has no equivalent, and neither does Medicare. MedPAC’s March 2026 report says no occupancy-style measure exists for home health care, so claims data can’t show whether an agency has room for one more patient.

Operators feel that gap every week. Homecare Homebase data reported by Home Health Care News shows referral conversion down 13%, with staffing-related rejections running about twice their pre-pandemic level.

Home health staffing analytics closes the gap. It joins scheduling, EVV, payroll, referral, and case-mix data into one view of how many visits your network can deliver next week and next quarter. It extends the staffing layer of predictive analytics for hospice operations to every line of a home-based care network.

This guide covers capacity, metrics, forecasting, burnout signals, payment scenarios, and shared hospice and home health nursing. Each section opens with a direct answer.

What is capacity planning in home health?

Capacity planning in home health estimates how many visits a network can deliver, compares that with expected referral demand, and closes the gap through scheduling, hiring, and training. It links three numbers: demand (referrals and census), supply (clinician and caregiver hours), and the share of those hours that reach a patient.

Why is time the real constraint in home health staffing?

Hiring can’t outrun churn. The Bureau of Labor Statistics counts 4.7 million home health and personal care aides in 2025 and projects about 760,500 openings a year through 2035. Most of those openings replace workers who leave the occupation or the labor force.

Capacity also leaks after the hire. Home Health Care News reported in July 2026 that documentation burden and scheduling friction drive home-based care turnover. Long drives and charting that spills into evenings take hours that a headcount number still counts as available.

Visit capacity = retained headcount × productive hours per head × share placed where demand sits. Recruiting feeds the first term. Analytics works on all three.

Will your next open shift fill with the right caregiver or whoever is free first?

What does the 2026 data say about home health staffing and referral conversion?

It shows rising demand, heavy churn, and falling conversion. The table collects the latest federal and trade figures in one place.

IndicatorLatest figureSource
Home health and personal care aides employed, 20254,677,100BLS, updated August 2026
Projected annual openings, 2025 to 2035About 760,500BLS
Home health RN turnover25.46%Homecare Homebase via Home Health Care News, July 2026
Home health aide turnover34%Homecare Homebase via Home Health Care News, July 2026
Personal care caregiver turnoverAbove 70% in many marketsHomecare Homebase via Home Health Care News, July 2026
Referral conversionDown 13%Homecare Homebase via Home Health Care News, July 2026
In-person visits per full 30-day period, FFS Medicare, 20248.4, down from 10.2 in 2019MedPAC, March 2026
Hospital discharges followed by a home health period, early 202418.0%, up from 15.8% in 2019MedPAC, March 2026

Sources: BLS Occupational Outlook Handbook; Home Health Care News (July 2026); MedPAC March 2026 Report to the Congress, Chapter 8.

Agencies deliver fewer visits per period than in 2019, while hospitals lean on home health more. The cause is mixed because payment design changed in 2020, so track visits per period by branch as your baseline.

How do referral conversion rates connect to staffing capacity?

A declined referral is a capacity signal. When an agency can’t staff a start of care inside the referral source’s window, the referral goes elsewhere and conversion falls. MedPAC adds that studies link delayed starts of home health care to adverse outcomes, so speed matters clinically as well.

Log every turn-away with a reason code: no clinician with the skill, no one inside the drive-time limit, authorization pending, or patient declined. Reason codes turn a lost referral into a forecast input. Our piece on referral leakage to post-acute care covers the revenue side.

Which metrics should leadership track to measure home-based care capacity?

Track visits per clinician per week, productive-hour share, travel time per visit, referral-to-first-visit time, turn-away rate, vacancy rate, first-year retention, and authorized-visit balance.

MetricWhat it tells youCommon trap
Visits per clinician per weekOutput per personIgnores acuity and case mix
Productive-hour sharePatient-facing hours divided by paid hoursNeeds EVV and payroll joined
Travel time per visitRoute and branch design qualityAverages hide rural outliers
Referral-to-first-visit timeWhether demand converts into careStart the clock at referral receipt
Referral turn-away rateUnmet demandUseless without reason codes
Vacancy rate by role and branchSupply gapCount unfilled hours, not only open positions
First-year retentionPipeline healthTrack by hire-month cohort
Authorized-visit balanceDemand ceiling for Medicare Advantage and Medicaid-funded careReview weekly, not at renewal

Productivity or staffing ratio: which tells you more about capacity?

Productivity tells you more. Ratios count people, and productivity counts completed visits per paid hour. A branch can hit its staffing ratio and still turn away referrals if drive time and documentation absorb the week. Use the ratio to set hiring targets and productivity to check that hires become visits. Weight each visit by acuity, because a wound care visit and a medication check take different time.

How do home-based care networks forecast demand and capacity across branches?

They forecast demand and supply on the same data and calendar, then rebalance every week. Demand comes from referral volume, hospital discharges, census, and case mix. Supply comes from clinician hours net of leave, vacancy, and ramp-up.

  1. Unify the inputs. Join EVV punches, scheduling history, HR and payroll, EHR case mix, the referral log, and authorizations.
  2. Forecast demand by branch and discipline on rolling 13-week and 12-month views.
  3. Forecast supply. Count clinician hours net of leave and vacancy, and treat first-year hires at partial productivity.
  4. Add constraints. Skills and licenses, drive-time limits, continuity of care, patient preferences, and overtime caps.
  5. Balance and review. Move work to where waitlists and idle hours coexist, compare forecast with actual visits weekly, and retrain the model.

Hospitals run the same forecast-then-schedule logic, and our piece on hospital staffing and demand forecasting shows the pattern. Home-based care adds drive time, visit continuity, and payer authorizations.

What data do you need before AI scheduling tools deliver results?

You need linked data from scheduling, EVV, HR, EHR, and referral systems, with one identifier per clinician and patient across all of them. Without it, a model optimizes a plan that never happened.

Data sourceWhy the model needs itWhat breaks without it
EVV punchesActual visit start, end, and travel gapsPlans built on times that never occurred
Scheduling historyWhat was planned, changed, and cancelledNo measure of schedule volatility
HR and payrollHire dates, hours, overtime, separationsNo retention curves by tenure
EHR and OASIS case mixAcuity and expected visit timeEvery visit looks identical
Referral logDemand and turn-away reasonsForecast reflects only accepted work

Agencies often hold these in separate systems with no shared key. That is a data engineering and integration job first, and models come second.

How do you balance capacity when some branches have waitlists and others have idle clinicians?

Treat the network as one pool with drive-time limits. Set rules for which clinicians can cover which zip codes, review waitlists and idle hours together each week, and move work before moving people. MedPAC notes that because home health isn’t delivered in a facility, agencies can adjust service areas as local conditions change. Remote options add headroom, yet telehealth or remote monitoring appeared in only 2.2% of FFS Medicare 30-day periods in 2024.

How should you plan hiring and training pipelines over 12 months?

Plan on four horizons, each with its own decision and method.

HorizonDecisionTypical method
DailyWho covers an open or new visitRule-based matching or AI ranking by skill, distance, and workload
WeeklySchedules and routes for the next one to two weeksOptimization such as mixed-integer linear programming (MILP)
QuarterlyHiring starts and training cohortsDemand forecast plus attrition by tenure
12 monthsHeadcount plan, branch openings, budgetScenario modeling across payment and referral cases

MILP picks visit assignments that minimize something, such as travel time, while obeying hard rules like skills, hours, and continuity. Demand and turnover come from separate forecasts, and the optimizer consumes both.

Plan hospice and home health capacity from one census forecast

Can predictive analytics identify burnout risk before clinicians leave?

Partly. Models can flag clinicians whose workload, schedule changes, and charting load resemble those of people who later left. They can’t see intent, and research shows that stated intent is an imperfect stand-in for actual exits.

A March 2026 study in the Journal of Occupational and Environmental Medicine followed U.S. nurses and nursing assistants. Burnout affected both turnover intention and actual turnover, while a sense of thriving at work affected intention without raising actual turnover. For modelers, that means training on actual separations from HR records.

Candidate signalWhere it comes fromWhy it matters
After-hours documentationEHR audit logsHome Health Care News cites documentation burden as a turnover driver
Schedule volatility (changes inside 48 hours)Scheduling systemScheduling friction is a named turnover driver
Weekly hours and overtimePayrollSustained overload
Tenure under 12 monthsHREarly exits concentrate among new hires
Declined shifts and call-outsScheduling systemEarly withdrawal

Candidate features. Validate each against your own separation history before acting on a score.

Use burnout scores to trigger support: rebalance a caseload, publish schedules earlier, or prompt a manager check-in. Keep a human decision-maker, log every alert, and test for bias across shifts and roles. Never tie a score to discipline. Our guide to building trusted agentic AI beyond HIPAA compliance covers these controls.

What does caregiver turnover cost, and how much can analytics prevent?

Turnover cost equals separations times direct replacement cost, plus the visit capacity lost while seats sit empty. Analytics can reduce the share tied to controllable causes such as schedule volatility and uneven workloads. No published benchmark gives a universal reduction rate, so measure yours in a pilot against the 2026 turnover rates above.

How do you evaluate vendor claims about staffing savings and turnover?

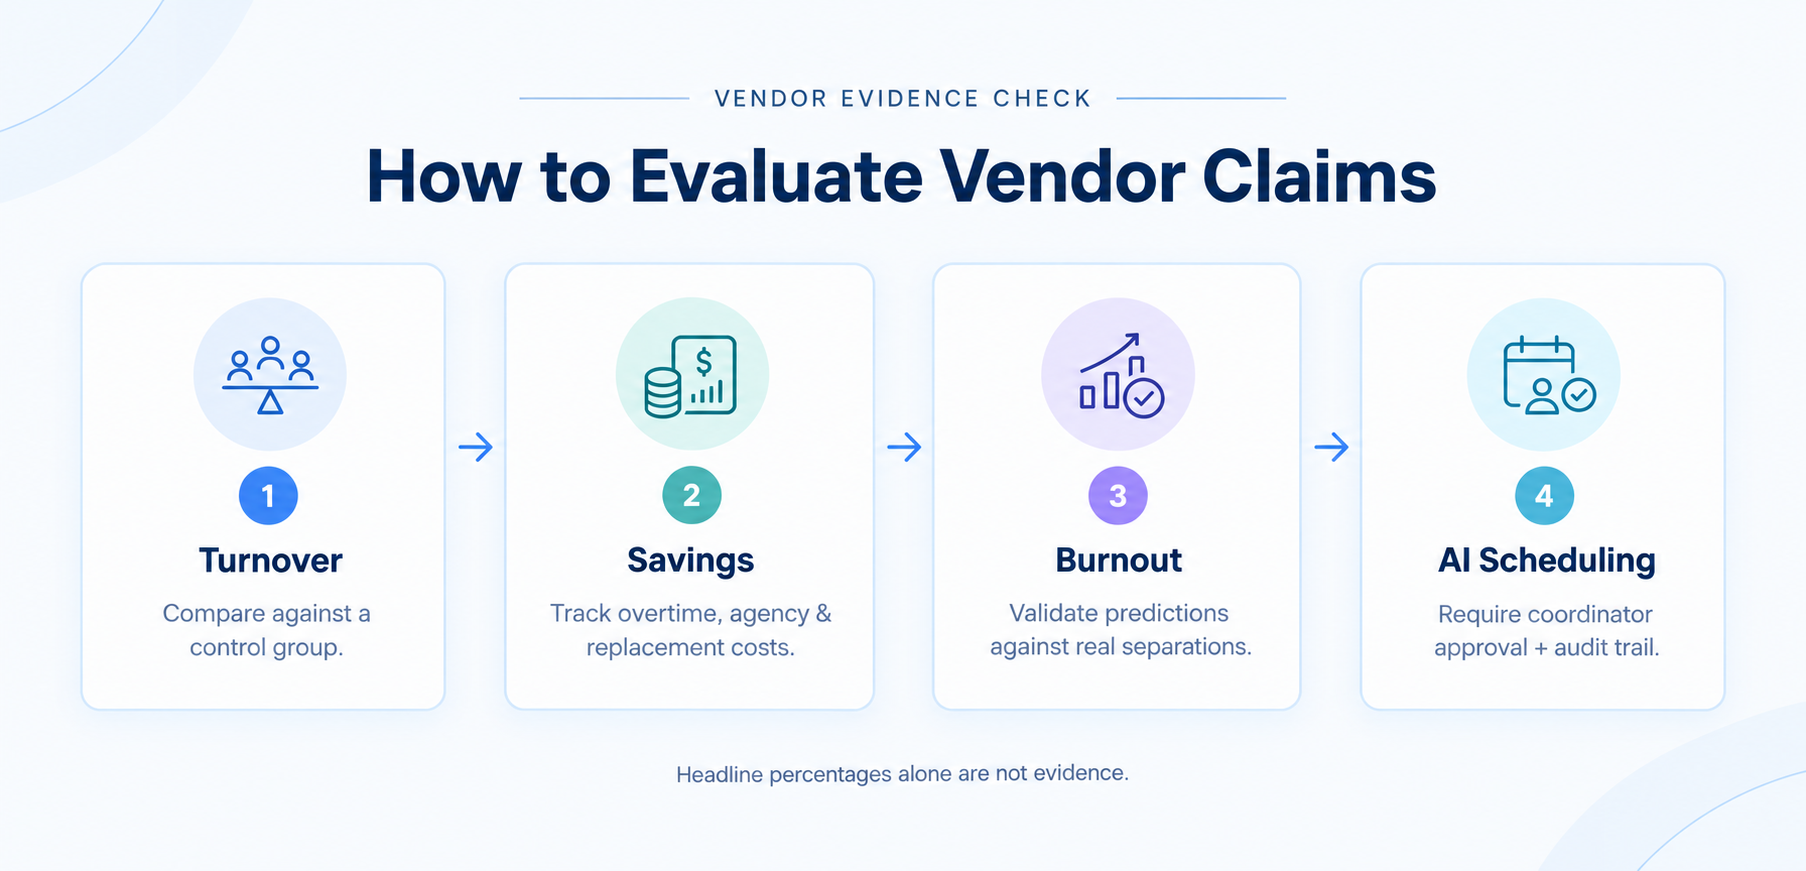
How do you evaluate vendor claims about staffing savings and turnover

Ask for a control group. Headline percentages alone don’t qualify as evidence.

  • Turnover cuts: compared with what, over what period? Look for matched control branches and separations from HR data.
  • Cost savings: which lines? Overtime, agency use, and replacement cost should be tracked separately.
  • Burnout prediction: validated against what? Ask for a backtest on your own separations.
  • AI scheduling: who approves assignments? Expect coordinator approval and an audit trail for each override.

How does AI scheduling reduce caregiver turnover in home care?

It targets churn drivers an agency controls: last-minute changes, mismatched assignments, long drives, and uneven workloads.

  • Predictive scheduling in home health: publish schedules one to two weeks ahead, built on the demand forecast.
  • Better matches: rank caregivers by skill, language, distance, and continuity with the patient. Our write-up on AI-powered patient-caregiver matching shows how this works in home care.
  • Shorter drives: cluster visits by geography.
  • Fair load: balance acuity and hours so no single clinician absorbs the hard cases.

Agents can draft schedule options and flag conflicts while coordinators approve each change, the model described in our framework for agentic AI in home care operations. Evidence for turnover reduction is still mostly vendor-reported, so pilot with a control branch before you scale.

How do Medicare payment changes and Medicare Advantage affect staffing forecasts?

Payment sets the labor budget, and Medicare Advantage shapes visit volume. Build forecasts on scenarios, because the CMS proposal and MedPAC’s recommendation point in different directions.

ItemStatusPlanning implication
CY 2027 payment updateCMS proposes a 2.4% aggregate increase, about $420 millionBase case for the labor budget
Temporary base-rate reductionCMS proposes a 3.0% reduction again for 2027Keep recoupment in margin assumptions
MedPAC recommendation7% cut to the 2026 base rate for 2027, which needs CongressDownside scenario
Palliative careCMS seeks comment on palliative care under the home health benefitNew demand source and overlap with hospice teams

Sources: CMS CY 2027 Home Health PPS Proposed Rule Fact Sheet (July 1, 2026); MedPAC March 2026 Report to the Congress. The rule is proposed, so check the final rule when it publishes.

Read the CMS proposed rule fact sheet for the full detail before you lock a budget. For Medicare Advantage, forecast approved visits and not referred patients, and monitor authorization balances weekly. Quality scores add a second link between staffing and revenue, because timely starts and consistent caregivers drive both.

How do hospice and home health teams plan shared nursing capacity?

Plan both from one workforce model with separate demand curves. Hospice demand follows census and stay-length bands. Home health demand follows referrals and 30-day payment periods.

Agencies that run both services can pool nurses and aides. BLS notes that aides in certified home health or hospice agencies must complete formal training and pass a standardized test, so credentials already overlap. CMS’s interest in palliative care under the home health benefit pulls the two services closer.

Start from the hospice census forecast. Our guide to hospice length of stay forecasting shows how stay bands set visit demand. Feed those bands and the home health demand forecast into one scheduling model, so two teams never promise the same clinician hour twice.

Forecasts earn their keep when each one routes to a named owner. A visit-demand spike should reach the scheduler with a proposed coverage list, and the scheduler approves it.

How do you start a home health staffing analytics program in 90 days?

Start with two or three branches and one question: where does visit capacity leak?

  1. Days 1 to 30, build the baseline. Join EVV, scheduling, HR, and referral data. Write one data dictionary for productive hours, vacancy, and turn-away.
  2. Days 31 to 60, size the leaks. Report productive-hour share, drive time, schedule volatility, and first-year retention by branch. Pick the biggest leak.
  3. Days 61 to 90, pilot one lever. Test predictable schedules, matching, or caseload rebalancing in one branch, with a control branch alongside.
  4. After day 90, decide with data. Compare pilot and control on separations, visits per clinician, and referral conversion. Scale what worked.

Workforce planning software helps when it reads from governed data and leaves scheduling authority with your coordinators. A predictive analytics partner can build the models, and your team should own the definitions and the approval step.

Final Thoughts

Networks that treat capacity as a measured, forecast number make better hiring, scheduling, and payer decisions. Start with one branch, one leak, and one control group. The next referral your team declines will then trace back to a cause you can fix.

This article is part of our series on predictive analytics for hospice operations, which extends the same governed data foundation from hospice to the wider home-based care network.

Ready to see where your network's visit capacity goes?

Frequently Asked Questions

Predictive Analytics for Hospice Operations: How Governed Data Becomes Forecasts Leadership Can Defend

Summary

Hospice predictive analytics works only when census, claims, and cost report data share governed definitions. This guide shows hospice care agencies how to forecast cap exposure, census, staffing, and payment updates on data that a board, auditor, or buyer can trace.

Introduction

Picture the Monday leadership meeting. Finance projects a cap liability of $380,000. Clinical operations reads the same census and sees no exposure at all. Billing counts beneficiaries differently from Medicare’s own reports. FY 2027 began on October 1 with a cap amount of $36,174.75 per beneficiary, so the gap between those three answers now carries a fresh number.

Predictive analytics for hospice operations starts with governed data. This article builds on the foundation in How Hospice Organizations Build a CMS-Ready Data Foundation and shows what becomes possible once that foundation exists: forecasting, eligibility screening, staffing models, and reporting that stands up to questions.

It’s written for CFOs, COOs, and CEOs at hospice care agencies who have to stand behind a number in front of a board, an auditor, or a buyer. Each section ends with a practice you can start this quarter.

Why do hospice forecasts fail when data definitions differ across teams?

Each team measures a different thing under the same name. A hospice forecast pulls from the clinical record, the billing system, HOPE submissions, the cost report, and Medicare’s own cap reports. Every source defines census, beneficiary, and length of stay a little differently, and the forecast inherits each disagreement.

MetricClinical recordBilling systemGovernance fix
CensusPatients on service at midnightPatients with paid days in the periodOne published definition of average daily census, with the source named
Beneficiary countAdmissions logged in the EMRUnique patients on submitted claimsReconcile to the Medicare PS&R and hospice cap reports before use
Live dischargeReason chosen by the clinicianDischarge status code on the claimMap both to one reason list and have a steward review exceptions
Length of stayDays since admissionDays billed per electionLabel every chart as current-election or lifetime stay

Typical definitions. Your own data dictionary should record the exact version each team uses.

Timing adds a second layer. Claims settle slowly, and MedPAC waits 15 months after a cap year ends before it estimates cap results. A forecast built on the first claims run will move as claims mature. Lineage is the third layer. When the number lives in a spreadsheet that three people edit, nobody can say which version the board saw.

A hospice data governance framework settles these arguments once. It names one steward per metric, writes the definition down, and runs the check inside the pipeline. Publish the cleansed result in the gold layer, and every team pulls the same number.

What is the hospice aggregate cap, and how is it calculated?

The aggregate cap limits total Medicare payments to a hospice in a cap year. Multiply the beneficiaries a hospice served by the cap amount and you get the most it can keep. Anything above that returns to Medicare. For the FY 2027 cap year the amount is $36,174.75, up 2.3% from $35,361.44 in FY 2026. A hospice that counts 1,000 beneficiaries has a ceiling of $36,174,750.

Two details shape every forecast. The cap applies across the whole patient population, so short stays create room for long ones. MedPAC calculates that the 2026 cap equals about 178 days of routine home care at a wage index of 1.0, and its worked example shows half a hospice’s patients staying 30 days while the other half average up to 335 days before the hospice crosses the line. The cap also carries no geographic adjustment.

The calendar matters as well. The FY 2026 cap year closed on September 30. CGS Administrators, a Medicare administrative contractor, tells hospices to file a self-determined cap three to five months after year end, which puts the window between December 31 and February 28. Beneficiary counts for that filing come from CMS’s PS&R and hospice cap reports, so those reports belong in your forecast pipeline from day one.

How do you forecast aggregate cap exposure every quarter?

How do you forecast aggregate cap exposure every quarter

Project total Medicare payments for the cap year, project the cap allowance from your beneficiary count, and compare the two. Then repeat it on a fixed schedule. Five steps keep the process repeatable:

  • Anchor on reconciled actuals. Start from paid claims and PS&R beneficiary counts to date, matched to the clinical census.
  • Project admissions and discharges by stay band. Short, typical, and long stays behave differently, and they move cap allowance in opposite directions.
  • Apply current rates and level-of-care mix. Use the published payment rates and the wage index for your area.
  • Compare payments with allowance. Report the gap in dollars and as a share of the allowance.
  • Freeze the snapshot. Save the inputs and assumptions with each run so anyone can reproduce the number later.

How often should a hospice project its cap liability?

Quarterly is the floor. Move to monthly in the last two quarters of the cap year, and run one more projection after the year closes and before the self-determined filing goes out. The reopening rule is the reason to keep every snapshot, because contractors can reopen a cap calculation for up to three years, according to MedPAC.

How do length of stay and live discharges change cap risk in a forecast?

Length-of-stay mix drives cap risk more than any other input, and the distribution is wide. In CMS’s April 2026 hospice monitoring report, 55.5% of FY 2025 stays ended within 30 days while 17.6% ran past 180. Medicare hospice payments reached $30.3 billion that year, so the long tail carries real money.

Lifetime hospice stay, FY 2025Share of Medicare fee-for-service beneficiaries
1 to 4 days20.4%
5 to 10 days16.4%
11 to 30 days18.7%
31 to 60 days10.9%
61 to 90 days6.0%
91 to 180 days10.0%
181 days or more17.6%

Source: CMS Hospice Monitoring Report, April 2026. Beneficiaries whose hospice stays had ended.

That spread is why hospice length-of-stay forecasting works best by band and diagnosis group, with survival probabilities at set horizons. A single average hides both the short stays and the long ones, and each pulls the cap in a different direction. Length-of-stay forecasting turns the distribution into a patient-level view that finance can roll up.

Live discharges belong in the same model. CMS reports a live discharge rate of 19.1% for FY 2025, and revocations (35.8%) plus patients no longer deemed terminally ill (31.1%) made up two-thirds of live discharges and transfers. Each one changes the beneficiary count and the payments that follow. MedPAC adds that above-cap hospices show longer stays and higher live discharge rates than below-cap hospices, even for patients with similar diagnoses, so reviewers read the two patterns together.

Cap projection starts with patient-level stay forecasts

How should a hospice forecast treat the FY 2027 payment update?

Treat it as a scenario, because three outcomes sat on the table this year. In its March report, MedPAC recommended 17 to 0 that Congress eliminate the FY 2027 update. In July, CMS finalized a 2.3% update, worth an estimated $755 million across the benefit. A hospice that misses quality reporting requirements takes four percentage points off that figure, which leaves a 1.7% reduction.

Reporting failures are common enough to model. CMS found that 20.37% of hospices were non-compliant in FY 2026, and HOPE records with 2026 target dates drive the FY 2028 update. That ties your revenue forecast to HOPE timeliness data. The cap amount also moves with the update percentage, so the same assumption touches both revenue and cap room.

ScenarioPayment updateEffect on $20 million in Medicare payments
Full update finalized by CMS2.3% increase$460,000 increase
Zero update (MedPAC recommendation)0%No change
Quality reporting miss1.7% reduction$340,000 reduction

Hypothetical hospice with $20 million in annual Medicare payments at prior-year rates. The gap between the first and last rows is $800,000.

How do you connect HOPE, claims, and cost report data into one forecast?

Start with the sources and name an owner for each:

  • Clinical record: census, visits, level of care, diagnosis, and HOPE assessments.
  • Billing and claims: paid days, payments, and PS&R reconciliation.
  • iQIES submission status: accepted and late HOPE records, which feed the payment update scenarios.
  • Cost report: cost per day and margin by service line.
  • CMS publications: payment rates, the cap amount, and the wage index.

The cost report deserves extra scrutiny. MedPAC says irregularities in how some hospices report revenue and expenses on cost reports keep it from calculating reliable all-payer margins. Medicare margin forecasts depend on the same fields, so hospice cost report data accuracy is a governance task with a named steward.

Integration comes first. If EMR, billing, and CMS reporting data never meet in one place, every forecast starts with a manual merge. Our guide to connecting EHR, billing, and CMS reporting covers that layer and shows how existing systems can feed it.

How do hospices forecast census and revenue?

Census forecasting combines three moving parts: new admissions, the survival curve of patients already on service, and discharges. Revenue follows from census days, level-of-care mix, and the payment rates in force. Admissions are the least governed part of that chain. A referral that waits days for a manual eligibility check and a physician signature becomes an admission on a different date, and that date can land in a different month, or a different cap year, than the forecast assumed. Teams that cut referral intake delays with automated eligibility screening hand the forecast cleaner admission dates, so intake noise stops showing up as census error.

Can predictive models improve census forecasting, or is data quality the real bottleneck?

Both matter, and the order matters more. A model trained on conflicting census definitions produces confident, wrong numbers. Once definitions and lineage are in place, healthcare predictive analytics adds real value: survival probabilities by horizon, stay-length bands, and live discharge risk roll up into a monthly census and cap projection. The benefit is earlier warning, and in hospice that means seeing a cap gap in June while there’s still time to act.

AI in hospice care follows the same sequence. Predictive modeling earns trust when each prediction carries a source, a date, and an error band that leadership can read. AI-powered automation for hospice can then run the routine checks, such as reconciling beneficiary counts to PS&R each month and alerting a steward when the cap gap crosses a set threshold. The model proposes, and people decide.

How do staffing and capacity plans fit into the forecast?

A census forecast doubles as a workload forecast. Stay-length bands show which patients will need heavier nursing and social work visits in their final days and which will need steady aide hours for months. For networks that run hospice alongside home health and personal care, staffing and capacity planning analytics ties caregiver supply to that demand curve, so a scheduler sees a shortfall weeks before a shift goes unfilled. The inputs are the same governed census and stay forecasts, so no second data build is needed.

Which data governance controls make a hospice forecast defensible?

Which data governance controls make a hospice forecast defensible

When CMS, an auditor, or a buyer questions an assumption, six controls decide whether you can answer in an hour or need a month:

  1. A metric dictionary with named owners. Every KPI has one definition, one steward, and a version history.
  2. As-of dates on every input. Each forecast run saves the data cut it used, so last quarter’s number can be rebuilt exactly.
  3. Reconciliation before release. Beneficiary counts and payments tie to PS&R and claims before any cap figure leaves finance.
  4. An assumption register. Payment update, stay-length mix, live discharge rate, and admissions each get an owner, a source, and a date.
  5. Lineage from dashboard to source. Anyone can trace a board-pack number through every transformation, as we describe in our piece on audit-ready data lineage.
  6. Independent re-performance. Someone who didn’t build the model reruns it twice a year and signs off. It’s the test of whether a new CFO or an outside reviewer could reproduce your numbers.

Scenario models leadership should run for FY 2027

Run at least four: the full 2.3% update, a quality reporting miss, a shift in stay-length mix toward longer diagnoses, and a rise in live discharges. The cap amount is set at $36,174.75 for the year, which makes it the one input you can lock.

How should forecasts reach the board?

Compress the results into one page: projected cap position, average daily census trend, margin, and the three assumptions that move them most, with the data cut date printed at the top. Add utilization and non-hospice spending metrics so directors see what CMS sees, since CMS now publishes provider-level Service and Spending Variation Index scores. Audit-ready dashboards carry the source and data cut date on every tile, so a number shown in the boardroom can be defended in a CMS review.

How does an unaccrued cap liability affect hospice valuation in due diligence?

Buyers re-perform the cap calculation from claims, and they usually treat any shortfall in your accrual as a debt-like item. The result is typically a lower price, an escrow, or an indemnity. The exposure also reaches backward, because contractors can reopen cap calculations for up to three years.

What margins should a forecast be tested against?

MedPAC projects an aggregate fee-for-service Medicare margin of about 9% for hospices in 2026, and it cited strong margins when it recommended no update for FY 2027. An average hides the spread. For a hospice with a high share of long stays, the cap can take back most of that margin, which is why the forecast should show margin before and after repayment.

Forecast the full repayment as owed. Diligence teams ask for the cap workpapers, the PS&R reconciliations, and the assumption history. If those exist as dated, governed files, the conversation gets shorter. If they live in someone’s inbox, expect the buyer to build a worst case on your behalf.

What does a mature hospice forecasting process look like?

DimensionSpreadsheet-based processGoverned process
DefinitionsEach team keeps its ownOne dictionary with named owners
Data refreshManual exports, merged by handScheduled loads reconciled to PS&R and claims
AssumptionsCell comments and memoryRegister with owner, source, and date
TraceabilityFile names like final_v7Lineage from board number to source
ReproducibilityDepends on the authorAny reviewer can rerun from a saved snapshot

Hospice budgeting and forecasting software works best when it reads from the governed column, because a faster tool on conflicting data produces conflicting numbers faster.

Final Thoughts

Your next forecast will be questioned by a board member, a reviewer, or a buyer. The open question is whether you can answer in an afternoon. The FY 2027 cap year opened on October 1, and the self-determined filing for FY 2026 comes due by February 28. That leaves roughly four months to reconcile beneficiary counts, freeze assumptions, and write the methodology down.

Start with one number, the cap projection. Make it traceable from the board page to the claim. Every other forecast you build, from census to staffing, will follow the same pattern.

Ready to trace every number in your forecast?

Frequently Asked Questions 

Cutting Hospice Referral Intake Delays with Automated Eligibility Screening

Summary

Most hospice referral intake delays trace back to manual eligibility checks, scattered referral channels, and slow physician signatures. Automated eligibility screening lets your team check every referral against the same criteria in minutes. It flags gaps early. This guide shows where the time goes, what to automate first, and what the 2026 research supports.

Introduction

Hospice referral intake delays are the time between a referral arriving and a patient being admitted. This article shows how automated eligibility screening shortens that window for hospice care agencies. It’s written for COOs and intake directors. You’ll see what slows admissions, which fixes you control, and what the evidence says.

The stakes show up in federal data. The median hospice stay for Medicare decedents was 19 days in 2024. MedPAC reports that more than one in four enrolled only in the last week of life. Every day lost at intake comes out of a stay that’s already short.

This is the second article in our series on predictive analytics for hospice operations. The main article of this series, How Hospice Organizations Turn Governed Data Into Forecasts Leadership Can Defend, explains and extends the process of how clean referral and admission data feeds leadership forecasts.

Where hospice referral intake delays come from

Delays start in two places: at the referral source and inside your own intake process. You control the second directly and can influence the first.

CauseWhere it sitsWhat it looks likeTypical fix
Late hospice conversationsReferral sourceHospice comes up only when death is nearLiaison outreach, referral feedback loop
Scattered referral channelsYour intakeFax, email, portal, and EHR referrals are keyed in by handOne intake queue
Manual eligibility reviewYour intakeA nurse reads each packet and results vary by reviewerAutomated screening
Missing documentsBothGaps surface after the first review, then phone calls startCompleteness check on arrival
Certification delaysYour team and the physicianThe patient is ready and the signature is still pendingDigital workflow with reminders
Coverage checksYour intakePayer eligibility is confirmed by hand, late in the processReal-time verification
Family decision timePatient and familyThe family needs time before electingEarly education, staff support


The referral side

MedPAC points to physicians who wait until death is near and families who prefer regular care first. Your intake team can’t remove those causes. It can make sure no referral waits once it arrives.

What the 48-hour hospice admission timeline covers

The 48-hour rule sets the deadline for the registered nurse’s initial assessment after election. Eligibility certification runs on its own clock.

RequirementDeadlineRule
Initial assessment by the hospice RNWithin 48 hours after election of hospice care is complete, unless the physician, patient, or representative asks for sooner42 CFR 418.54(a)
Comprehensive assessment by the IDGNo later than 5 calendar days after election42 CFR 418.54(b)
Written certification of terminal illnessBefore the hospice submits its claim42 CFR 418.22(a)
If written certification isn’t readyOral certification within 2 calendar days, and written before the claim42 CFR 418.22(a)(3)
Early certificationAllowed up to 15 calendar days before the election takes effect42 CFR 418.22(a)(3)
  • Early certification means your team can request signatures ahead of election day for patients who already screen as eligible.
  • The physician’s narrative has to reflect the patient’s individual circumstances. Check boxes and standard language don’t meet the rule.

What automated eligibility screening does

What automated eligibility screening does

Automated eligibility screening reads a referral packet and pulls out the clinical signs that matter. It scores them against criteria your clinical leaders wrote. Then it returns a status for a clinician to confirm.

  1. Referrals from fax, email, portal, and EHR land in one queue.
  2. Document processing pulls diagnosis, functional status, hospitalizations, and decline indicators from the record.
  3. The system flags missing documents right away and requests them.
  4. Your written criteria produce a status with the reasons attached.
  5. Eligible referrals move on, borderline ones go to a clinician, and incomplete ones go back to the source.

A clinician makes the final call. The tool gives every packet the same review, whatever the day or the reviewer.

Intake Automation vs. Eligibility Screening

Vendors use both terms loosely, so separate them before you buy.

DimensionReferral intake automationAutomated eligibility screening
What it doesMoves referral data between channels and systemsScores clinical indicators against your criteria
OutputA complete record in your EHR or CRMA status with reasons for a clinician to confirm
Saves time onKeying, routing, acknowledgmentsPacket review and follow-up calls
Needs clinical rulesNoYes
Weak spotSpeeds up referrals nobody has screenedDepends on complete, accurate source data

Payer verification belongs in the same workflow

Hospice eligibility verification automation also covers payer checks for Medicare, Medicare Advantage, and Medicaid. Run them in the same workflow so coverage and clinical status come back together.

Speed needs accuracy

MedPAC reports an aggregate live-discharge rate of 19.1% in 2024. It says high rates can signal a hospice admits patients who don’t meet eligibility criteria. Consistent, documented scoring protects your admissions as well as your timeline.

See how an eligibility agent scores a hospice referral packet

What the 2026 research says about automated screening

A 2026 meta-analysis in npj Digital Medicine pooled seven randomized trials covering 125,666 patients. The trials tested algorithms inside hospital and clinic EHRs that flag patients who may need palliative care. They did not test hospice-side intake screening.

FindingResultWhat it means for you
Palliative care consultationsRelative risk 2.19 for non-cancer patients and 5.31 for cancer patientsAlgorithms prompt earlier conversations at the referral source
Hospice useRelative risk 0.97 (95% CI 0.95 to 1.00) across two trialsNo clear lift in hospice enrollment overall
Timing of hospice startOne included trial found usual-care patients more likely to start hospice in the last 3 days of lifeThe authors suggest timing can improve even when totals stay flat
Staff capacityIn one included trial, fewer than half of eligible patients received a consultation, largely due to workforce limitsFlags only help when someone can act on them quickly

The authors also report high variation between trials and note that all of them ran in the United States.

What this means for your hospice

  • Referral-source algorithms run inside other organizations’ EHRs. You can support them through liaison relationships, and you don’t control them.
  • Hospice-side screening sits in your hands. The review didn’t test it, so your own baseline is the evidence that matters.
  • Capacity decides results. Pair automation with staff who answer flags the same day.

Baseline these six metrics before you automate

You can’t judge ROI without a starting point. Pull these from the last 90 days.

MetricHow to measureWhat it tells you
Referral-to-decision timeHours from receipt to eligibility statusWhere manual review slows you down
Referral-to-admission conversionAdmissions divided by eligible referralsWhether faster decisions turn into census
Time to admissionHours from referral to electionTotal delay, including physician and family steps
Missing-document rateShare of referrals incomplete at first reviewChannel and referral source quality
Certification turnaroundHours from request to signaturePhysician workflow friction
Median stay by referral sourceDays, grouped by hospital, SNF, and clinicWhich relationships send patients late

Fix the channel problem first: fax, email, portal, and EHR

Referrals that arrive through four channels get four different levels of care unless one workflow sits underneath them. Good hospice referral management technology starts there.

  • Route every channel into one queue and time-stamp each handoff.
  • Use one required-fields checklist, whichever channel the referral used.
  • Send an automatic acknowledgment so the referral source knows you have it.
  • Return incomplete packets with a specific list of what’s missing.

To automate the referral intake process without creating new data silos, connect it to your EHR and billing systems. Our guide to hospice EMR and referral data integration shows how.

Build a feedback loop with hospitals and SNFs

  • Send each referral source a monthly summary: volume, time to decision, share of complete packets, and median stay.
  • Flag sources whose volume is falling or whose referrals are arriving later.
  • Review the pattern with your liaisons, since they own the relationship.

Those drops add up fast. Our look at referral leakage to post-acute care explains the revenue side.

Close the certification gap

A referral can be screened, covered, and ready, and still wait on a signature.

  • Trigger the certification request the moment screening returns eligible.
  • Give the physician a one-page clinical summary drawn from the record.
  • Let the physician write the narrative. The rule bars check boxes and standard language.
  • Use e-signature, automatic reminders, and escalation to the medical director.
  • Track hours from request to signature every week.

What one day of intake delay costs

For patients with a short prognosis, the date of death is fixed. Each day lost at intake is a day of care that never happens.

Revenue at risk

Days lost × average daily payment × referrals affected

MedPAC puts the average Medicare hospice payment at about $191 per day in 2024. If 40 referrals a month wait an extra 1.5 days, that’s about $11,460 a month in unbilled care (40 × 1.5 × $191). Treat the number as an illustration. Your rates, levels of care, and delay data will change it.

The figure leaves out the harder losses. Families get fewer days of support. Referral sources send the next patient to a faster hospice.

How to choose hospice intake automation software

Ask every vendor to demonstrate these capabilities on your own referrals. Intake is one of several workflows where AI-powered automation for hospice now delivers value, and our overview of AI in hospice care covers the rest.

CapabilityAsk the vendor to show
Live payer verificationDoes it check coverage against the payer in real time, or only route paperwork?
Editable clinical rulesCan your clinicians change criteria without a developer ticket?
Visible reasoningDoes every score list the source documents and values behind it?
Audit trailAre inputs, rules, scores, and confirmations time-stamped and exportable?
Clinician in controlDo borderline cases route to a person who confirms eligibility?
Channel coverageDoes it take fax, email, portal, and EHR referrals?
EHR write-backDoes the status land in your hospice EHR without re-keying?

A 90-day plan for your hospice team

  1. Days 1 to 30: Baseline the six metrics and map every referral channel.
  2. Days 31 to 45: Write screening criteria with your medical director. Give non-cancer diagnoses such as heart failure, COPD, and dementia their own checklists. The 2026 meta-analysis notes palliative care delays are especially common there.
  3. Days 46 to 90: Pilot on one channel or one referral source and compare against baseline each week.
  4. Day 90: Decide whether to extend, using conversion and time to decision as the deciding numbers.

Ready to shorten your referral-to-admission window?

Frequently Asked Questions 

Hospice Length of Stay Forecasting: Building Models Leadership Can Defend

Summary

Hospice length of stay forecasting estimates how long each patient will stay on service, so COOs can see cap exposure, staffing strain, and live discharge risk early. This guide covers what the models predict, the data they need, how accurate they are, and how to validate one before leadership relies on it.

Introduction

Ask most hospice leaders how long their current census will stay, and the honest answer is a number from last quarter’s report. That number describes stays that have already ended. Hospice length of stay forecasting estimates it patient by patient and day by day, so a COO can see cap exposure, staffing strain, and live discharge risk before any of them reach a compliance report.

The timing matters. FY 2027 began on October 1 with a higher aggregate cap, and CMS now displays provider-level service and spending scores built from claims data. Hospice care agencies that can’t forecast their own stays are guessing at both.

This guide is for COOs and clinical operations leaders at hospice and palliative care organizations. It covers what the models predict, the data they need, how accurate they really are, and how to validate one before your leadership team stakes a decision on it.

What hospice length-of-stay forecasting predicts

Hospice length of stay forecasting uses statistical and machine learning models to estimate how many days a patient will remain on hospice service. The estimate starts from clinical, functional, and claims data at admission and updates as the stay unfolds.

Most hospice data analytics programs produce one of three outputs:

  • Survival probability by horizon. The chance a patient is still on service at 7, 30, 90, and 180 days.
  • Stay-length bands. A short stay of under a week, a typical stay, or a long stay past 180 days.
  • Live discharge risk. The likelihood a patient leaves hospice alive through revocation, an improved prognosis, or a move out of the service area.

How hospice length-of-stay prediction differs from hospital models

Most predictive analytics in healthcare was built for hospitals, where the question is when a patient goes home. A hospice model asks when a patient with a prognosis of six months or less will die or leave service, and the benefit’s rules shape that target. A hospice 6-month prognosis prediction model informs the physician’s certification, and the physician keeps the decision.

DimensionHospital length of stay modelHospice length of stay model
What it predictsDays until discharge home or transferDays until death or live discharge
Typical horizonDays to weeksDays to six months and beyond
Why accuracy mattersBed flow and discharge planningCap exposure, visit planning, and quality scores
Key inputsDiagnosis, procedures, labs, vitalsFunctional status, diagnosis trajectory, prior utilization, care setting
Regulatory tieThroughput targetsAggregate cap, Hospice Care Index, SSVI

That’s why a hospital model can’t be reused as-is. The target, the error costs, and the regulatory stakes all change.

Palliative Care and Hospice Need Separate Models

The palliative care vs hospice line shapes your models. Palliative care sits outside the hospice benefit, so it carries no aggregate cap and no six-month certification. A 2026 study of 261,290 Australian palliative care patients found that predicting episode duration stayed modest, with R² around 0.2 after calibration. That’s a useful reality check for any palliative care length of stay AI project. Train each service line on its own data and set accuracy expectations before launch.

Which of your current patients are drifting toward day 180?

Why length of stay drives cap, quality, and staffing risk

Length of stay touches three pressure points at once: Medicare payment, quality scores, and clinical capacity. Each one rewards a hospice that sees stays coming.

How Hospices Use Predictive Models to Manage Aggregate Cap Risk

The aggregate cap limits total Medicare payments to a hospice in a cap year. CMS finalized the FY 2027 cap amount at $36,174.75 per beneficiary, up 2.3% from FY 2026. Long stays raise payments per beneficiary, which is the pressure the cap is designed to catch. A forecast lets finance and clinical leaders project hospice aggregate cap financial risk every month and act before the year closes.

Short Stays and Long Stays Both Carry Risk

Both ends of the distribution matter. In FY 2025, about 20% of Medicare fee-for-service hospice patients stayed four days or fewer, while the share staying past 180 days climbed from 14.5% in FY 2021 to 17.6%. Short stays strain admission and visit capacity. Long stays raise cap exposure and need a documented clinical case for continued eligibility.

Lifetime length of stayFY 2021FY 2025Change (points)
1-4 days23.0%20.4%-2.6
5-10 days18.1%16.4%-1.7
11-30 days19.4%18.7%-0.7
31-60 days10.6%10.9%+0.3
61-90 days5.6%6.0%+0.4
90-180 days8.9%10.0%+1.1
181+ days14.5%17.6%+3.1

Source: CMS Hospice Monitoring Report, April 2026. Share of Medicare fee-for-service beneficiaries whose hospice stays had ended. The change column is calculated from the CMS figures.

Why the Average Length of Stay in Hospice Misleads

Headline averages blur this split. About 56% of FY 2025 stays ended within 30 days, and more than one in six ran past 180. A single mean describes neither group well. Forecasting by band lets a hospice team plan for the stays it will actually see.

How Length of Stay Ties to the Hospice Care Index

Stay length also shows up in public quality scores. The Hospice Care Index scores hospices on ten claims-based indicators, including live discharges in the first seven days and live discharges on or after day 180. CMS reports that the live discharge rate among Medicare hospice patients rose from 16.9% in FY 2021 to 19.1% in FY 2025. Early and late departures are exactly the events a forecast helps a hospice team see coming.

Where the CMS Service and Spending Variation Index Fits

The SSVI adds a second lens. It scores each hospice on nine claims-based measures covering utilization and non-hospice spending, and CMS says higher scores signal potentially concerning patterns. A hospice that models its own claims sees its profile before CMS does.

What data does a hospice length-of-stay prediction model use?

Strong models draw on four families of data. Every input needs a timestamp, so the model sees only what the hospice team knew on the day of prediction.

  • Functional status. Palliative Performance Scale (PPS) scores, decline in daily activities, weight loss, and oral intake. The PPS rates patients from 0% to 100% in 10-point steps across mobility, activity, self-care, intake, and level of consciousness.
  • Diagnosis and trajectory. Primary diagnosis, comorbidities, and recent hospitalizations.
  • Utilization and claims history. Prior hospital use, earlier hospice elections, referral source, and care setting.
  • Operational signals. Visit frequency, level-of-care changes, and notes from the interdisciplinary group (IDG).

Using Palliative Performance Scale data in machine learning models

Functional scores earn their place because they change. One PPS score at admission is a snapshot. The slope across repeat assessments carries the signal, and pairing it with claims history gives the model both trajectory and context.

Why data integration decides model quality

These inputs sit in different systems. Functional scores live in the clinical record, utilization in billing, and referral context in intake tools. Teams that connect EHR, billing, and CMS reporting data first spend their modeling time on modeling.

Point-in-time discipline matters just as much. Every feature should carry the date the hospice team learned it, and any later edit should keep the original version. A model trained on cleaned-up history will look more accurate than it ever is in live use.

A governed gold layer serves these inputs as consistent, documented features, so a prediction made in March can be reproduced in an audit in June.

How accurate are machine learning models at predicting hospice length-of-stay?

Accuracy depends on the horizon. Machine learning hospice mortality prediction and palliative care prognosis prediction both separate near-term deaths well and drift on longer horizons.

In a 2026 prospective cohort of 166 advanced cancer patients in a palliative care unit, specialist judgment and two prognostic scores reached a concordance index above 0.8 for short-term survival. Clinical judgment tended to underestimate 7-day survival, and every tool tended to overestimate 90-day survival.

Duration is harder still, as the Australian study above shows. Use a forecast as a triage and planning signal with a stated error band, and keep the physician’s certification as the decision of record.

Machine Learning vs Clinical Judgment

Combine them. The same 2026 cohort study recommends pairing specialist judgment with a validated prognostic score. Build the workflow the same way: the model proposes a stay band, the hospice team reviews it, and each override is recorded and fed into the next retraining cycle. That’s how hospice eligibility prognostication tools earn clinical trust.

Predicting Non-Cancer Length of Stay for Dementia and Heart Failure

Cancer accounts for about 22% of hospice users in the latest CMS data, so most of a typical census follows a non-cancer path. Dementia, heart failure, and COPD decline more slowly and are harder to date. Validate every model by diagnosis group, care setting, and age band, and share the gaps with clinical leaders. A model that works for advanced cancer and misfires on dementia will quietly distort cap projections at hospice care agencies of any size.

How to build a hospice length-of-stay forecasting model leadership can defend

How to build a hospice length-of-stay forecasting model leadership can defend

A defensible model is one a compliance officer, a medical director, and an outside reviewer can each interrogate. Six steps get you there.

  1. Name the decision. Cap projection, admission triage, visit planning, and live discharge outreach each need a different horizon and error tolerance.
  2. Build a point-in-time data set. Timestamp every feature and version every edit, so the model trains on what the hospice team knew at the time.
  3. Start with a transparent baseline. Logistic regression or a Cox model sets the benchmark. Gradient-boosted trees such as XGBoost have to beat it on calibration and subgroup performance as well as raw accuracy.
  4. Validate beyond accuracy. Check calibration by horizon, test on a later time period, and compare performance across diagnoses, care settings, and demographic groups.
  5. Make every prediction explainable. Show the top drivers for each patient, log clinician overrides, and keep model documentation current.
  6. Trace and monitor. Record where each input came from with audit-ready data lineage, and re-test performance after rule or workflow changes.

Clinical and compliance reviewers tend to ask the same three questions before they trust a model.

  • Which inputs drove this estimate?
  • How often has the model been wrong for patients like this one?
  • Who can override it?

Build those answers into the interface, because they’re hard to add later.

Putting length of stay forecasts to work

A forecast earns its keep when it triggers a task. AI-powered automation for hospice works best when each forecast routes to a named owner with a due date.

Hospice Census Forecasting and Cap Planning

Roll patient-level forecasts into a monthly census and cap projection for finance and the COO. Then test scenarios, such as what happens if admission mix shifts toward longer-stay diagnoses.

Staffing and Visit Planning by Length of Stay

Patients with a high near-term mortality estimate need added nursing and social work visits in the coming days, which also supports the CMS Hospice Visits in the Last Days of Life measure. Long-stay patients need steady aide and nursing hours. A hospice team that schedules against both curves matches visit hours to need as it develops.

Live Discharge Rate Prediction and Recertification Risk

Compare each forecast with the patient’s recent functional trend. When they diverge, the patient is a candidate for an earlier IDG review, which lets a hospice catch an eligibility question before a recertification raises it. Our COO playbook on predicting readmission risk before it happens covers the same alert-to-action discipline for discharge loops.

Admission Timing and Referral Triage

Referrals with a high near-term mortality estimate can move to the front of the intake queue. A predictive model for hospice admission that also estimates timing tells the team how much capacity next week’s admissions will require.

Where the Return Shows Up First

Returns tend to appear where exposure is largest: avoided cap repayments, visit hours moved to higher-need days, and fewer avoidable early live discharges. A pilot on one service line, scored against your own history, shows the size of the prize before anyone commits budget.

Final Thoughts

Hospice length of stay forecasting won’t call any single patient’s final day, and good teams don’t ask it to. What it gives leadership is a calibrated view of the census, a stated margin of error, and a record of how each estimate was made. That’s the version that survives a question from the board or a reviewer.

It also depends on the data underneath it. Forecasting is one use of AI in hospice care, and the same governed foundation supports eligibility, documentation, and admissions work. This article is part of our series on predictive analytics for hospice operations, and the staffing, referral intake, and dashboard pieces of that series build on the same models.

Ready to forecast hospice length of stay with data your auditors can trace?

Frequently Asked Questions 

Data Governance and CMS Compliance Frameworks for Hospice Organizations

Summary

A hospice data governance framework gives your leadership team named owners, tested data rules, and traceable records across HOPE, CAHPS, and claims data. This article lays out the hospice CMS compliance framework that protects your Annual Payment Update, prepares your hospice team for the October 1, 2026 election statement addendum rule, and holds up when CMS asks for proof.

Introduction

A hospice data governance framework decides whether your organization can prove, record by record, that CMS requirements were met. On October 1, 2026, a mandatory election statement addendum becomes part of every Medicare hospice election. Calendar year 2026 HOPE records keep counting toward your fiscal year 2028 payment update. A hospice CMS compliance framework built on real governance ties each of those obligations to a named owner, a tested rule, and evidence you can pull in minutes.

Picture a hospice team reviewing its quarter. The charts are clean. The overall HOPE timeliness number reads 92%, which feels safe. Then someone splits it by site, and one location, running a different EMR, sits at 84%. Nobody owned that site’s data. The rolling percentage hid the problem until it was a problem.

That gap is what this article closes. It’s the fourth article in our hospice series and builds on the hub, How Hospice Organizations Build a CMS-Ready Data Foundation. Here you’ll find what to govern, who should own it, and a checklist leaders at hospice care agencies can use this quarter.

What is data governance in a hospice organization?

Data governance in a hospice organization is the set of decisions about who owns each data domain, which quality rules apply, who can access the data, and how every change gets recorded. It covers clinical data in the EMR, billing and claims data, HOPE submissions in iQIES, and CAHPS records handled by an outside vendor. HIPAA data governance sits inside it: minimum-necessary access, audit logs, and PHI controls apply to every one of those systems.

Healthcare data governance and compliance are related, and they aren’t the same thing. Compliance asks whether you met a requirement. Governance asks whether you can prove it again, for every record, without heroics.

A hospice can pass HOPE this quarter through overtime and manual checks and still have no governance. That’s compliance without maturity. Maturity means the result holds when your quality director leaves or you add a fifth site. It also means one person can answer a CMS reviewer’s question without calling three departments.

Need a governance model built for HOPE, CAHPS, and claims data?

Why Hospice CMS Compliance Now Depends on Data Governance

The Hospice Quality Reporting Program (HQRP) draws on three data sources: HOPE assessments, the CAHPS Hospice Survey, and Medicare claims, according to CMS’s January 2026 HQRP guide. Each fails in its own way, so each needs its own governance.

HOPE Timeliness and the 90% Threshold

Hospices must submit and have accepted at least 90% of HOPE records within 30 calendar days of the admission date, the HOPE Update Visit (HUV) completion date, or the discharge date. Compliance is judged on records whose target date falls in the calendar year, so records dated January 1 to December 31, 2026 decide the fiscal year 2028 payment update.

The penalty is a 4 percentage point cut. For FY 2027, CMS set the payment update at 2.3%, so a hospice that misses HQRP requirements gets a 1.7% reduction instead, per the CMS FY 2027 final rule fact sheet. That’s a six point swing on the same patients and the same care.

The math is unforgiving. A hospice filing 1,000 HOPE records in a year can afford 100 late ones. The 101st costs four points of payment. And “accepted” is a status in iQIES, not in your EMR, so if nobody owns the accepted-status check, late records sit unnoticed until year end.

CAHPS Hospice Survey Data and Your Vendor

Every Medicare-certified hospice takes part unless it qualifies for the newness exemption or the size exemption (fewer than 50 survey-eligible decedents in the prior year). A CMS-approved vendor runs the survey and submits data quarterly. Compliance means the vendor submits complete, accepted data for all 12 months of the collection year. HOPE and CAHPS have separate requirements, and failing either one triggers the reduction, as the CMS reconsideration page explains.

Here’s the governance gap. Your hospice sends the vendor a monthly list of decedents and caregivers, and that list comes from your EMR. A wrong or late list means wrong or late survey data. Give the list an owner, reconcile it against discharge records, and check the CAHPS data warehouse account so you see what the vendor actually submitted.

Claims Data, HCI, HVLDL, and the SSVI

Two HQRP quality measures come from Medicare claims: Hospice Visits in the Last Days of Life and the Hospice Care Index. Because CMS pulls claims directly, hospices count as fully compliant on that requirement automatically. The exposure is data quality. The claim is the record, and CMS reads it whether you reviewed it first or not.

The FY 2027 final rule, issued July 30, 2026, finalized the Service and Spending Variation Index (SSVI). It scores each hospice from 0 to 16 using nine claims-based measures covering utilization and non-hospice spending, and a higher score signals potential concern. CMS published provider-level scores based on FY 2024 and 2025 claims and made no substantive changes to the methodology. It also says it monitors metrics such as live discharge rates, average visits per routine home care day, and non-hospice spending per day.

So, a governed hospice runs its own version of those numbers every month. Reconcile clinical visit records against billing, review live discharge patterns, and catch discrepancies before a federal score reflects them.

The Compare Tool Icon and Public Reporting

CMS finalized an icon on the Medicare.gov Care Compare tool for hospices that submit no quality data, or under 90% on time, within a year. It takes effect no earlier than FY 2028. CMS reports that 22.06% of hospices were non-compliant in FY 2024, 23.53% in FY 2025, and 20.37% in FY 2026. Roughly one in five is missing the mark, and the icon puts that gap where families and referral sources look.

What should a hospice data governance framework include?

Strong HQRP data governance rests on five components. Skip one and the others carry weight they weren’t built for.

Ownership and Stewardship

Every data domain gets one named steward: HOPE records, CAHPS lists, claims and billing, and election statement addendum data. Orphan fields are where missed timepoints hide.

Data Standards and Quality Rules

Write down what “complete” means for each HOPE timepoint, then automate the check. A missing HUV date should trigger an alert while the 30-day window is still open, not after it closes.

Lineage and Reconciliation

You need to trace any record from the clinical entry to the iQIES acceptance receipt. Layering data into raw, cleaned, and reporting-ready zones makes that trace practical, which we cover in Medallion Architecture Explained.

Access and Privacy Controls

Role-based access, PHI logging, and de-identified evidence packs keep HIPAA obligations intact while your hospice team shares data across IDG, billing, and QA.

Monitoring, Escalation, and Audit Evidence

Dashboards by site and by timepoint, thresholds that trigger escalation, and archived reports that prove what you knew and when.

Data domainTypical stewardCore controlEvidence a reviewer can ask for
HOPE recordsQuality or QA directorTimepoint alerts and daily accepted-status check in iQIESSubmission and acceptance reports by record and date
CAHPS lists and vendor dataCompliance officerMonthly list reconciliation against dischargesVendor submission confirmations for all 12 months
Claims and billingBilling or revenue cycle leadClinical to billing reconciliation before claims dropReconciliation logs and exception resolutions
Election statement addendumAdmissions and IDG leadRequired-field checks and version controlSigned addendum with timestamp and determinations

Who owns Data Governance across IDG, Billing, and QA Teams?

Build a Governance Council with one accountable executive

Committees can advise, but they can’t be accountable. Name one executive, often the COO or the compliance officer, who answers for HQRP data outcomes. Under that person, seat a council with your IDG lead, billing, QA, IT, and compliance, and have it meet monthly to review exceptions by site, domain, and timepoint.

Stewards then handle the daily work. The QA steward watches HOPE. The compliance steward owns the CAHPS vendor relationship. The billing steward owns the clinical to claims match. Everyone knows whose name is on which number.

Stop one missed hope update visit from becoming a compliance failure

One late record won’t fail you. A pattern buried inside a percentage will. Treat each HOPE timepoint as a scheduled task created at admission, with an alert to the steward when the window is closing. Pull a daily iQIES accepted-status report. Track rolling timeliness by site each week and set an escalation threshold well above 90% so you have room to correct.

That last step matters most. A 90% floor gives you no margin, so govern to an internal target that leaves one.

How to govern the hospice election statement addendum in 2026

In final rule CMS-1851-F, published in the Federal Register on August 3, 2026 and effective October 1, 2026, CMS made the addendum mandatory for every Medicare hospice election. Before, hospices provided it only when a beneficiary or representative asked. The addendum lists the conditions, items, services, and drugs the hospice has determined are unrelated to the terminal illness and related conditions, and therefore not covered by the hospice benefit. CMS also notes it gives non-hospice providers the information they need for claims, per its fact sheet.

The regulation text sets delivery in the first five days of the election effective date. That turns a document into a data workflow. Governance should cover these points:

  • Store each related or unrelated determination as a structured field tied to the plan of care, so it can be queried and audited.
  • Version every addendum and keep the signed copy, or the recorded refusal or unable-to-sign status, linked to the election record.
  • Alert the admissions steward when an election is approaching its five-day mark without an addendum on file.
  • Connect addendum data to your claims review, because CMS has tied non-hospice spending to the SSVI.

Reconciling clinical, billing, and CMS submission data

The hard question in any review is whether three sets of records agree: what clinicians documented, what billing claimed, and what CMS received. A governance framework runs that comparison on a schedule, so a reviewer never gets there first. Our piece on connecting EHR, billing, and CMS reporting covers the integration side in detail.

One billing detail deserves a flag. The FY 2027 rule extends the telehealth allowance for the hospice recertification face-to-face encounter through December 31, 2027, and adds a requirement to report modifiers or codes for those encounters. Those data points need a clean home in your billing feed.

Build reconsideration-ready evidence

When CMS finds a hospice non-compliant, it notifies through the Medicare Administrative Contractor and an electronic letter in iQIES. The hospice then has 30 days from the date on that letter to request reconsideration, by email only, with supporting documentation. CMS decisions typically follow in September, and an unresolved finding means the payment reduction starts October 1. These details come from the CMS reconsideration page.

Proof of timely submission, iQIES submission reports, and vendor confirmations all count as evidence. Requests can’t include PHI or PII, and files can’t exceed 20 MB. Keep de-identified evidence packs ready all year, because 30 days passes fast.

Centralizing governance for multi-site and multi-EMR hospices

If your sites run different EMRs, standardize the definitions before you standardize the tools. Agree on one data dictionary for HOPE timepoints, one reconciliation routine, and one reporting view that rolls every site into a shared dashboard. A central governance team owns the rules. Site stewards own execution and report exceptions upward.

Hospice data governance checklist for HOPE, CAHPS, and claims reporting

Hospice data governance checklist for HOPE, CAHPS, and claims reporting

  1. Name one accountable executive and one steward for each data domain.
  2. Register more than one iQIES Provider Security Official, since CMS recommends it.
  3. Schedule every HOPE timepoint at admission and alert stewards as windows close.
  4. Run a daily accepted-status check in iQIES and a weekly rolling timeliness view by site.
  5. Set an internal timeliness target above 90% and define an escalation path.
  6. Reconcile the monthly CAHPS decedent and caregiver list against discharge records, and monitor vendor submissions.
  7. Reconcile clinical, billing, and CMS submission data on a fixed schedule.
  8. Track your own SSVI-style utilization and non-hospice spending metrics each month.
  9. Structure and version election statement addendum data, and keep de-identified evidence packs ready for reconsideration.

Where AI-Powered automation for Hospice fits after governance

Automation earns its keep once the rules are written down. Alerts for closing HOPE windows, addendum tracking, and reconciliation checks are all rule-driven work that AI-powered automation for hospice can run continuously. Automate a process with no owner and you just move mistakes faster.

That’s why governance comes first in this series. The foundation in our hub article supports these controls today and the forecasting and agent use cases coming next.

How Inferenz approaches data governance consulting services for hospice teams

Inferenz works with hospice and home-based care organizations on ownership models, data quality rules, lineage, and integration across EMR, billing, and CMS reporting systems. If you’re weighing data governance consulting services, start with your highest-risk domain, usually HOPE timeliness, and build outward from there.

Ready to pressure-test your hospice data governance?

Frequently Asked Questions

Building Audit-Ready Data Lineage That Survives a CMS Review

Summary

A Medicare Administrative Contractor’s additional documentation request gives a hospice 45 calendar days to produce a complete record for the one claim it’s questioning. Most compliance teams can pull that claim in minutes. Far fewer can show, system by system, exactly how it got there, and that second skill is what a real audit tests.

Introduction

The letter rarely looks like the start of something serious. It names a patient, a date of service, a benefit period, and a deadline. From there, someone at the hospice has to rebuild the full story behind that record: which system captured the physician’s narrative, when the election statement was signed, whether the diagnosis on the claim still matches the diagnosis in the chart, and who touched the file along the way. That rebuild is exactly what audit-ready data lineage is built to answer, ideally long before any letter shows up.

Most hospices can answer that question eventually. Very few can answer it inside the 45 calendar days a Medicare Administrative Contractor (MAC) allows for an Additional Documentation Request, and fewer still can answer it the same way twice if a second reviewer asks. That gap, between having the data and being able to prove where it came from, is the specific problem data lineage is built to close. CMS and the HHS Office of Inspector General have both gotten sharper at testing for exactly that gap.

What “Audit-ready” actually means, and why it’s different from “Data-ready”

A hospice can be data-ready and still fail an audit. Data-ready means the EMR holds a diagnosis, the billing system holds a claim, and the two roughly agree. Audit-ready means the hospice can show, for any single record an auditor picks, the full chain of custody: which system created the data element, which system or person changed it, when the change happened, and why. That chain is data lineage, and it’s a meaningfully different deliverable from data quality alone.

The distinction matters because CMS and OIG reviewers aren’t just checking whether a number is correct. They’re checking whether the hospice care agencies can reconstruct, on demand, how that number came to be. A hospice that connects its EMR, billing, and referral intake data has usually solved the double-entry problem that eats staff time. It still has separate work to do on the lineage problem, because a clean interface moves data between systems without automatically recording where each value originated or who last touched it.

The audits that actually show up at a hospice’s door

Three oversight mechanisms account for almost every real compliance event a hospice will face, and each one tests data lineage in a slightly different way.

  • OIG compliance audits, built on statistical sampling and extrapolation. The HHS Office of Inspector General runs an ongoing series of hospice compliance audits, and it doesn’t review every claim to do it. It pulls a sample, commonly around 100 claims, checks each one against Medicare requirements, and when the error rate is high enough, extrapolates the dollar impact across the full population of claims the hospice billed for that period. CMS’s own 2026 oversight update pointed to how real that exposure has become, noting that enhanced review in four states alone had already produced more than 200 hospice Medicare enrollment revocations. OIG picks which hospices to review in the first place using computer matching, data mining, and data analysis techniques run against claims data, so audit risk starts building long before any letter shows up. A hospice that can’t trace a sampled claim back through its clinical and billing history has no real way to challenge either the finding or the extrapolation that follows it.
  • MAC medical review, through Additional Documentation Requests and Targeted Probe and Educate. MACs run both broad and targeted reviews of hospice claims. Under Targeted Probe and Educate, a MAC pulls 20 to 40 claims per round from providers with the highest denial rates or the most unusual billing patterns, running up to three rounds with individualized education between each. The clock on any ADR starts the moment it lands.
  • HQRP compliance, enforced through the HOPE submission threshold. Since October 1, 2025, the Hospice Outcomes and Patient Evaluation
  • (HOPE) tool has replaced the Hospice Item Set, and every record now has to move through iQIES, the only channel CMS accepts since the legacy QIES/ASAP system was retired. CMS requires 90% of HOPE records submitted within 30 days of the relevant admission, discharge, or update-visit date, or the hospice loses 4 percentage points off its Annual Payment Update. That threshold functions as a lineage problem more than a paperwork one: the data has to flow cleanly from the point of clinical assessment into iQIES without someone manually re-keying it under deadline pressure.

CMS has also been raising the general level of scrutiny hospices operate under. In 2026, the agency proposed new transparency measures built partly on a Service and Spending Variation Index that scores hospices using claims-based utilization metrics, publishes those scores, and flags high-scoring hospices for additional review. The same announcement noted that roughly 20% of hospices were out of compliance with HQRP reporting requirements in CY 2025, a rate CMS described as comparable to prior years. That consistency is the tell and this is a widespread industry gap.

What CMS’s Medicare Advantage Audit Framework Signals for Hospice

Hospice program audits don’t run on the same protocol as Medicare Advantage program audits, and it’s worth being precise about that before drawing any comparison. Still, the logic CMS applies to one Medicare program tends to surface in the others eventually, and the classification system CMS already uses for Part C and Part D audits is a useful preview of where hospice oversight is headed.

CMS’s Part C and Part D program audit framework sorts findings into an Observation, for noncompliance that doesn’t need a formal fix, a Corrective Action Required (CAR), for noncompliance that does, and an Invalid Data Submission (IDS) finding, reserved for cases where a sponsor cannot produce an accurate, complete “universe” of records and CMS cannot determine compliance as a result. CMS has also been evaluating Compliance Program Effectiveness (CPE) less as a checklist of written policies and more as a live conversation about how a plan actually detects and corrects problems as they happen.

The IDS classification is really a test of whether a sponsor can produce a defensible, complete record on demand, and a single incorrect answer is a much smaller problem than a universe of records nobody can reconstruct. Risk Adjustment Data Validation (RADV) audits, the mechanism CMS uses to verify Medicare Advantage risk-adjustment payments, run on a related logic: the diagnosis on a claim has to trace back to a specific, contemporary clinical encounter, or CMS claws back the payment.

Hospice oversight runs on a different vocabulary altogether: OIG extrapolation, MAC documentation requests, and SSVI scoring. The underlying test is the same one regardless. Can the organization produce a complete, source-traceable universe of records on demand? A governed data lineage layer exists to pass exactly that test.

See how hospice organizations can build a CMS-ready data foundation efficiently

Data Lineage vs. Data Provenance: A Distinction That Matters Once CMS Asks

The two terms get used interchangeably, and in a hospice audit context, the difference is worth keeping straight. Data provenance answers where a piece of data originated: which system, which form, which staff member entered it first. It’s answers the fuller question: every system and transformation that record passed through afterward, including edits, merges, and exports, on its way to the CMS submission.

Data Provenance vs. Data Lineage

Data ProvenanceData Lineage
What it answersWhere a piece of data originatedEverywhere that data went afterward
ScopeA single point in time: the system, form, or staff member who first entered itThe full path: every system, edit, merge, and export the record passed through
Example (election statement)Confirms the election was signed in the EMR on a given dateConfirms that update also reached billing and the referral record before any revocation, benefit-period change, or new admission touched the same patient again
What it catchesWho entered a value, and whenDesynchronization between systems, the exact pattern CMS’s hospital-hospice claims edits are built to flag
Why a hospice needs bothEstablishes the starting point of the recordEstablishes whether that record stayed consistent all the way to the CMS submission

A hospice election statement is a good example of why the difference matters. Provenance tells you the election was signed in the EMR on a given date. Lineage tells you whether that election status update also reached billing and the referral record before a revocation, a benefit-period change, or a new admission touched the same patient again. CMS’s newer claims edits, the ones comparing hospital and hospice claims for overlapping services and flagging admission-date and billing-date mismatches, are built to catch exactly the kind of desynchronization a gap like this creates.

What a Defensible Audit Trail Actually Has to Show

What a Defensible Audit Trail Actually Has to Show

When a MAC, a state surveyor, or an OIG auditor asks a hospice to defend a record, they’re rarely asking for a single data point. They’re asking for a reconstruction. A defensible audit trail needs to show, for any patient and any date range:

  • Source-to-submission mapping. Which system captured the original clinical assessment, referral, or diagnosis, and every hop that data made on its way into a HOPE record, a claim, or an iQIES submission.
  • Claims-to-clinical reconciliation. Whether the level of care, visit dates, and diagnosis codes on the claim still match the clinical documentation behind them, since a mismatch here is the specific pattern CMS’s newer hospital-hospice billing edits are designed to catch.
  • Election and revocation history. A timestamped, cross-system record of every election statement, revocation, and benefit-period change, so EMR, billing, and referral records can’t disagree about a patient’s current status.
  • Grievance and appeals traceability. A hospice’s own complaint and grievance records, plus any Medicare claim appeals filed on a beneficiary’s behalf, need the same source-to-outcome trail as clinical data, because surveyors and MACs both ask for it.
  • AI model lineage, where applicable. If a hospice uses AI to support documentation, eligibility screening, or care planning, an auditor can reasonably ask which data informed that output and what a clinician reviewed before it reached the record. Most hospices haven’t built for this yet, and it’s becoming a standing expectation.

Where Hospice Data Lineage Actually Breaks

Four gaps account for most of the lineage failures we see in hospice organizations, and every one of them is fixable without touching the underlying systems.

  1. The first is the referral-to-EMR handoff, where a referral arriving by fax or portal gets keyed in as a new patient record and later turns out to duplicate one created through a different intake path.
  2. The second is election status drift, where a revocation updates in one system only, creating the exact mismatch CMS’s audit logic is built to flag.
  3. The third is the pharmacy and durable medical equipment gap, where medication and equipment data still move by phone and fax while everything else has been automated, leaving a hole in the same clinical record CMS is checking.
  4. The fourth, and increasingly the most consequential, is the spreadsheet workaround: the export someone pulls into Excel to reconcile two systems by hand, which quietly becomes the record of truth nobody can trace back to its source once an auditor asks where a number came from.

These line breaks mean that hospice care agencies will repeatedly bank on erroneous data for their processes. Fixing the data lineage is crucial for these organizations to rely on accurate data and make informed decisions.

Building the Lineage Layer Without a Rip-and-Replace

Building the Lineage Layer Without a Rip-and-Replace

Fixing this leakage starts with a governed data layer that sits underneath the EMR, the billing platform, and the referral tools a hospice’s staff already know and use every day. That layer tracks, at the record level, where data entered the organization, every system it moved through, and every transformation applied along the way. In practice, that means:

  • Mapping the systems first, before the tools. Before evaluating any data lineage software, a hospice needs a clear map of every system that touches a patient record: EMR, billing, referral intake, pharmacy, DME, and any AI tools layered on top. Lineage mapping only works when it starts from a complete inventory.
  • Treating lineage as one feature of a broader governance foundation. Standalone data lineage tracking works best as part of a wider data quality management and governance framework. A point tool that only visualizes lineage after the fact does little to fix the upstream data quality gaps that create the mismatches auditors flag in the first place.
  • Building automated, near-real-time interfaces. The same bidirectional integration principles that solve hospice EMR-to-billing double entry also generate a cleaner lineage record along the way, because a system that writes and reads data automatically leaves a far more traceable trail than one staff bridge by hand.
  • Treating AI documentation and eligibility tools as lineage sources. Any AI system touching clinical documentation, eligibility screening, or care planning needs its own record of what data it used and what a clinician confirmed, a gap Inferenz has covered separately in the context of hospice AI readiness generally.

A hospice’s own data quality, governance, and compliance program is the natural home for this work, since lineage without governance mostly produces a very detailed record of an ungoverned mess. Inferenz has built this kind of foundation for post-acute care organizations moving off 32 disconnected source systems onto one governed data platform, the same underlying problem most hospices face at a smaller scale.

What to Have Ready Before the Letter Arrives

Continuous audit readiness looks different from the once-a-year scramble most hospices still run today. The organizations that stop dreading MAC letters and OIG notices tend to share a few habits: they can pull a complete case file, source-to-submission, for any patient within minutes; their compliance officer reviews a sample of records against CMS’s current claims-edit logic on a standing schedule; and their hospice and palliative care operations team treats data governance as an ongoing operational function.

That shift, from periodic to continuous, is also where CMS’s own compliance language across every Medicare program keeps pointing: fewer point-in-time checklists, more real-time evidence that an organization catches and corrects its own problems before an outside reviewer does it.

Ready to know more about building an audit-ready data foundation for your hospice?

Frequently Asked Questions

The Top 10 EHR/EMR Platforms for Home Care, Home Health, and Hospice in 2026

Summary:

Home health, hospice, home care, and post-acute leaders are choosing among ten dominant systems in 2026: Homecare Homebase and WellSky for enterprise home health and hospice, MatrixCare for multi-line post-acute organizations, AlayaCare and Axxess for cloud-native home care and private duty, HHAeXchange for Medicaid EVV compliance, PointClickCare for skilled nursing, athenahealth and eClinicalWorks for ambulatory and hospital-adjacent settings, and Intus Care for PACE programs. The right choice depends on care setting, payer mix, and how well the winning system talks to everything else you run.

Why this decision carries more weight than it used to

A home health or hospice agency picks a core clinical system once every seven to ten years. Get it right, and that system becomes the operational backbone for referrals, scheduling, billing, and every OASIS or HOPE assessment a clinician files. Get it wrong, and the organization spends the next decade working around software instead of with it.

That decision has gotten harder heading into 2027. Three forces are converging on post-acute and home care leadership teams at once.

  • First, CMS has raised the compliance bar. Under the expanded Home Health Value-Based Purchasing Model, an agency’s Calendar Year 2025 performance already determines the payment adjustment (up to plus or minus 5 percent of Medicare fee-for-service revenue) that lands on 2027 claims. Starting with the CY 2027 program year, CMS also requires all-payer OASIS data submission, so an EHR’s OASIS accuracy tools now matter for every patient on the census, not just the Medicare ones.
  • Second, the workforce math hasn’t improved. Caregiver and clinician shortages remain the top constraint most home-based care leaders name, pushing vendors toward AI-assisted scheduling, documentation, and referral intake because there simply aren’t enough hands to do it the old way.
  • Third, and this is the one CXOs underestimate most, the industry keeps consolidating. Every acquisition arrives with its own EHR, its own patient records, and its own definition of a “duplicate” patient. The question is no longer just which system your clinical team likes. It’s which system, or combination of systems, you can actually run as one business.

This guide breaks down the ten platforms home care, home health, hospice, and post-acute organizations evaluate most often in 2026, what each does well, where each falls short, and where the real integration work begins once the contract is signed.

How we evaluated these platforms

How we evaluated these platforms

Each platform was scored against the criteria CXOs, COOs, and compliance officers actually use in an RFP:

  • Care-setting depth: purpose-built workflows for home health, hospice, home care, skilled nursing, or PACE, not a generic template
  • Regulatory coverage: OASIS-E, HOPE, MDS/PDPM, HIPAA, HITRUST, SOC 2, and Electronic Visit Verification (EVV) under the 21st Century Cures Act
  • Interoperability: HL7 FHIR support and participation in Carequality, CommonWell, and TEFCA
  • Scheduling and field operations: route optimization, offline documentation, caregiver matching
  • Revenue cycle: claims scrubbing, denial management, payer-specific workflows
  • AI maturity: ambient documentation, predictive risk models, agentic workflows
  • M&A readiness: how well the platform handles multiple source systems after an acquisition
  • Total cost of ownership, since almost none of these vendors publish list pricing

What’s actually changing in 2026

Documentation is going ambient. Nearly every platform now ships some version of AI-assisted charting: an ambient scribe that drafts the note during the visit, a predictive model that flags hospitalization risk, or a natural-language layer that answers a plain-English question instead of six menu clicks.

Interoperability stopped being optional. A decade ago, “does it talk to the hospital’s EHR” was a nice-to-have. Today referral sources, ACOs, MCOs, and CMS expect clean data exchange through Carequality, CommonWell, or TEFCA, and platforms that still hoard patient data are losing referral relationships over it.

Quick comparison: the top 10 at a glance

PlatformBest forPrimary care settingsDeployment
Homecare HomebaseLarge, multi-state home health and hospice enterprisesHome health, hospice, personal care, private dutyCloud, point-of-care mobile
WellSkyAgencies of any size wanting one home-based care system of recordHome health, hospice, palliative care, personal careWeb-based
MatrixCareOrganizations spanning SNF, senior living, home health, and hospiceSNF, senior living, home health, hospice, private dutyCloud
AlayaCareCloud-native home care and private duty agencies scaling across statesHome care, home health, private duty, remote monitoringCloud, mobile-first
AxxessMid-size home health, hospice, and home care agencies wanting modular toolsHome health, hospice, home care, pediatric home careCloud, mobile
HHAeXchangeMedicaid personal care agencies and MCOs needing EVVPersonal care, Medicaid HCBS, home healthWeb-based
PointClickCareSkilled nursing and senior living, plus their post-acute referral networkSNF, senior living, assisted living, home health, hospiceCloud
athenahealthAmbulatory and hospital-adjacent primary care, including home-based primary careAmbulatory, primary care, specialtyCloud, single-instance
eClinicalWorksAmbulatory practices and community health centers, with post-acute facility supportAmbulatory, community health, hospital, post-acuteCloud or on-premise
Intus CarePACE (Programs of All-Inclusive Care for the Elderly) organizationsPACE, interdisciplinary senior careCloud, Snowflake-backed

Want to understand how to leverage your EHR with Caregence?The 10 EHR/EMR Platforms in 2026

The 10 EHR-EMR Platforms in 2026

1. Homecare Homebase (HCHB)

Best for: large, multi-site home health and hospice enterprises that need point-of-care documentation, scheduling, and revenue cycle on one configurable platform.

Homecare Homebase has been the backbone of large-scale home-based care since 1999. The platform serves all ten of the largest home health agencies and eight of the ten largest hospice agencies in the country.

Owned by Hearst, HCHB built its reputation on point-of-care depth: Mobile PointCare handles offline documentation, CareManager covers personal care field staff, and the HCHB Intelligence Suite layers Smart Scheduling and predictive hospitalization-risk models on top.

Key features:

  • Offline-capable mobile documentation for OASIS and hospice IDG workflows
  • Smart Scheduling matched by geography, skill, and availability
  • Predict: Hospitalization Risk for proactive care planning
  • Community Connect for interoperable data exchange
  • Billing and revenue cycle tools built around PDGM

Where it fits, and where it doesn’t: HCHB is built for scale, and agencies running a handful of locations often find the configuration overhead and multi-month onboarding hard to justify. For a multi-state enterprise, it remains one of two platforms (with WellSky) that dominates the large end of the market.

2. WellSky

Best for: agencies wanting one system of record across home health, hospice, palliative, and personal care, with predictive analytics built into daily workflows.

WellSky calls its home health product the Intelligent Health Record, baking real-time predictive insights (seven-day mortality risk, live discharge risk) directly into the clinician’s workflow. More than 4,500 agencies and 1.6 million home health and hospice patients run on the platform, and its hospice product is HOPE-compliant out of the box with a dedicated operational dashboard.

Key features:

  • Predictive insights for hospitalization and discharge risk
  • Referral management with AI-assisted response, added in 2026
  • HOPE-compliant hospice documentation and dashboard
  • Centralized eligibility, authorizations, and denial management
  • Agency performance analytics for QAPI and referral relationships

Where it fits, and where it doesn’t: WellSky’s reputation as “The Clinician’s Choice” for ease of use is earned, and its interoperability posture suits organizations proving outcomes to referral partners. Some agencies cite pricing as the reason they migrate away, since the tiered per-census model climbs fast at scale.

3. MatrixCare

Best for: post-acute organizations spanning SNF, senior living, home health, and hospice under one EHR family rather than a patchwork of point solutions.

MatrixCare, owned by ResMed, has served the post-acute space since 2001 and now serves more than 15,000 long-term care providers, the second-largest long-term care EHR platform behind PointClickCare. Its home health and hospice line descends from Brightree and was named Best in KLAS across multiple categories in 2024.

Key features:

  • Unified EHR across SNF, senior living, home health, hospice, private duty
  • MDS 3.0 and PDPM-aware compliance tools
  • Interoperability with hospitals, labs, and pharmacy partners
  • Real-time analytics and mobile point-of-care charting

Where it fits, and where it doesn’t: A pure-play home care agency often finds MatrixCare’s breadth is more platform than it needs. For a multi-line post-acute group, that breadth is the entire point, and several independent comparisons rate it ahead of PointClickCare for organizations spanning home health, hospice, and senior living together.

4. AlayaCare

Best for: cloud-native home care, private duty, and home-based care organizations wanting AI embedded across scheduling, billing, and documentation from day one.

Founded in Canada in 2014, AlayaCare has grown to serve more than 2,000 home care agencies across North America. AlayaLabs, its dedicated data science team, builds the scheduling algorithms, the Clinical Notes Detector that flags warning signs automatically, and remote patient monitoring dashboards that cut unnecessary visits.

Key features:

  • AI-powered scheduling and route optimization with live GPS
  • Remote patient monitoring and HIPAA-compliant telehealth
  • Family and stakeholder portal
  • Open API (Alayaconnector) for third-party EMR and CRM integration

Where it fits, and where it doesn’t: AlayaCare’s open API stands out in a market that mostly treats integration as an afterthought, which makes it a strong pick for agencies already running a broader tech stack they don’t want to abandon. Where it fits less well is for smaller, single-location operators who don’t need that level of extensibility and would rather have a simpler, more prescriptive setup out of the box.

5. Axxess

Best for: small to mid-size home health, hospice, and home care agencies wanting modular tools without an enterprise-scale commitment.

Axxess (formerly AgencyCore) has quietly become one of the most widely deployed platforms in the segment, with 9,000-plus organizations, ONC 2015 CEHRT certification, SOC 2 Type II compliance, and more than 40 interoperable integrations. Its ‘Ask Axxess’ tool lets staff query records conversationally instead of navigating menus.

Key features:

  • Modular product lines: home health, hospice, home care, pediatric
  • Interactive wound manager and OASIS scrubber
  • Ask Axxess conversational search
  • Bulk hospice scheduling and on-call monitoring

Where it fits, and where it doesn’t: Modular pricing makes Axxess approachable for agencies that don’t need every feature immediately. A minority of reviews flag integration gaps for complex, multi-payer operations, worth stress-testing in a pilot.

6. HHAeXchange

Best for: Medicaid personal care agencies, MCOs, and state programs needing best-in-class Electronic Visit Verification and Medicaid-specific billing compliance.

HHAeXchange built its reputation as the leading EVV system for Medicaid-funded personal care, certified by CMS as an official EVV Aggregator in several states, connecting state Medicaid programs, MCOs, providers, and caregivers under the 21st Century Cures Act’s EVV mandate.

Key features:

  • GPS and fixed-object EVV with pre-billing validation
  • CMS-certified EVV Aggregator status in multiple states
  • Claims matching against EVV data before adjudication
  • CarePay payroll built specifically for home care

Where it fits, and where it doesn’t: For an agency running primarily on Medicaid personal care contracts, HHAeXchange’s EVV depth is hard for a generalist EHR to match. Agencies with a broader private-pay mix often pair it with a separate clinical system rather than run everything through it.

7. PointClickCare

Best for: skilled nursing and senior living operators needing a connected referral network reaching into home health, hospice, and hospital systems.

PointClickCare has been rated the top Long-Term Care Software Provider by KLAS for six consecutive years and holds roughly 60 percent skilled nursing market share. Its real relevance here is the network effect: 27,000-plus long-term and post-acute providers, 3,100-plus hospitals, and a Marketplace of 210-plus integrated partners, the largest interoperability ecosystem in the category.

Key features:

  • Point of Care app for bedside vitals and medication administration
  • AI-powered Chart Advisor, expanding into senior living in 2026
  • Marketplace ecosystem across 20 use case categories
  • Deep interoperability through Kno2, Carequality, and CommonWell

Where it fits, and where it doesn’t: PointClickCare’s financial tooling and SNF depth consistently rate ahead of competitors, though MatrixCare edges it out for organizations centered on home health, hospice, and senior living rather than skilled nursing.

8. athenahealth (athenaOne)

Best for: ambulatory practices and hospital-adjacent primary care, including home-based primary care, needing cloud-native interoperability and a hands-off revenue cycle.

athenaOne bundles athenaClinicals, athenaCollector, and patient engagement into a single-instance cloud system that updates automatically for all 160,000-plus providers at once, no manual upgrade cycle, no version to fall behind on. athenahealth’s claims-scrubbing engine runs more than 29,000 rules with a first-pass acceptance rate north of 95 percent.

Key features:

  • Single-instance cloud with automatic, zero-downtime updates
  • FHIR R4 APIs, plus CommonWell, Carequality, and TEFCA participation
  • 250-plus pre-integrated Marketplace apps
  • AI-native documentation and ambient scribing

Where it fits, and where it doesn’t: athenahealth earned the 2026 Best in KLAS award for independent ambulatory practices, but it’s built for clinic-based workflows, not field-based home visits, so home health and hospice agencies typically look elsewhere for their core system even when athenahealth sits upstream as the referring physician’s EHR.

9. eClinicalWorks

Best for: ambulatory practices, community health centers, and hospital-affiliated post-acute facilities wanting one AI-forward vendor across EHR, revenue cycle, and patient engagement.

eClinicalWorks has scaled to more than 850,000 users and 180,000 physicians on Microsoft Azure. Its 2026 direction centers on agentic AI: Sunoh.ai for ambient documentation, healow Genie for automated patient calls and scheduling, and PRISMA for searching a patient’s consolidated record across outside systems. CommonWell and Carequality exchange is free, unlike some competitors.

Key features:

  • ai ambient scribe and healow Genie call automation
  • PRISMA record-search across outside health systems
  • healow patient portal, TeleVisits, remote monitoring
  • 50-plus specialty templates, including post-acute facility support

Where it fits, and where it doesn’t: eClinicalWorks’ AI ecosystem is one of the more mature in ambulatory care, but home health and hospice-specific field workflows aren’t its focus, so home-based organizations typically use it as a connected upstream system rather than their primary EHR.

10. Intus Care (CareHub)

Best for: Programs of All-Inclusive Care for the Elderly (PACE) organizations needing an EMR built around interdisciplinary, value-based senior care rather than a generic long-term care template.

Intus Care is the most specialized platform here, deliberately so. Its CareHub EMR launched in May 2025 and expanded to 33 PACE programs across 16 states within its first year, fast adoption in a niche most organizations had been running on generic long-term care software. CareHub sits inside a broader ecosystem including PRISM (population health), IRIS (AI risk adjustment), and ILLUMINATE (2026 CMS PACE Audit Protocol compliance).

Key features:

  • Interdisciplinary team (IDT) care planning built for the PACE model
  • Out-of-the-box TPA and Carequality integration
  • Snowflake-backed warehouse with natural-language querying
  • Compliance tooling aligned to the 2026 CMS PACE Audit Protocol

Where it fits, and where it doesn’t: For a PACE organization, CareHub’s specificity is the whole value proposition. Outside of PACE, it isn’t relevant, and organizations running PACE alongside home health or hospice still need a second system for those lines.

Where Inferenz adds value: PACE participants are often hospice-eligible, and CareHub’s own roadmap points toward curated, normalized data, precisely the direction Inferenz’s MPI and Patient 360 work builds toward for organizations running CareHub alongside a separate home health or hospice EHR.

How to choose: a decision framework by care setting

Start with care setting; it eliminates more of the list than any other filter.

  • Enterprise home health and hospice: Homecare Homebase or WellSky. Both are strong; the decision usually comes down to clinician preference in a pilot.
  • Multi-setting post-acute (SNF, senior living, home health, hospice): MatrixCare, with PointClickCare as the alternative if skilled nursing is your largest line.
  • Home care, personal care, private duty: AlayaCare for AI-native scheduling and an open API, Axxess for modular, incremental pricing.
  • Medicaid personal care and managed care: HHAeXchange, usually run alongside a separate clinical EHR.
  • Skilled nursing with post-acute network reach: PointClickCare, with MatrixCare as the multi-setting alternative.
  • Ambulatory, hospital-adjacent, or home-based primary care: athenahealth’s percentage-of-collections model versus eClinicalWorks’ AI-forward, flatter fee structure.
  • PACE programs: Intus Care’s CareHub, with no real generalist substitute.

After care setting, weigh interoperability, EVV and compliance coverage for your payer mix, total cost of ownership including migration, and AI maturity, in that order. Pilot with your own census before signing. Every demo looks smooth; month three, with your actual edge cases, is where the real gaps show up.

What the RFP never asks: what happens to your data after you sign

Every vendor here shows up with a clean demo and a tidy patient list. Almost none will walk through what your data looks like eighteen months after go-live, once you’ve completed an acquisition or accumulated years of records your last vendor never fully migrated.

That’s the gap Inferenz was built to close. Inferenz is a data and AI engineering company for US healthcare enterprises, with a HIPAA-aligned agentic AI platform called Caregence that sits on top of whatever EHR an organization already runs, built and governed to earn clinical trust rather than bypass it.

The work isn’t theoretical. Inferenz helped a national home care provider managing over 60,000 patients unify more than 40 disconnected source systems, including multiple EMRs left behind by a decade of acquisitions, into one governed warehouse. The engagement resolved duplicate identities through AI-powered de-duplication, built an M&A onboarding framework that gets every new entity analytics-ready within 8 to 10 weeks, and shipped three AI applications into production, including a caregiver recommendation engine that fills last-minute cancellations automatically.

None of that required replacing the underlying EHR. It required someone who understood how to make the EHR, or the five EHRs, actually work together. If you’re choosing between the platforms above, or already running two or three after a merger, that’s the conversation worth having before the next acquisition closes. Book a strategy consultation with Inferenz to talk through what unifying your EHR data would look like for your organization.

The bottom line

Every platform here can run a home care, home health, hospice, or post-acute organization competently. The differences that matter show up in your care settings, payer mix, growth plans, and how well your system shares data with everything else you run. Pick on those factors, pilot before you commit, and plan the data unification work from day one rather than after your third acquisition forces the issue.

Do you want to see how home care, home health, and hospice organizations turn fragmented EHR data into governed, AI-ready systems?

Frequently Asked Questions

How Hospice Organizations Build a CMS-Ready Data Foundation

Summary

On October 1, 2025, CMS replaced the Hospice Item Set (HIS) with the Hospice Outcomes and Patient Evaluation (HOPE) tool. The core compliance rule did not change: at least 90% of required records must be submitted and accepted within 30 days, or the hospice loses 4 percentage points from its Annual Payment Update. What changed is everything around that rule: up to twice as many records per patient, tightly timed clinical windows in the first 30 days of care, a new submission system, and mandatory third-party encoding. This article explains what HOPE requires of hospice care organizations, where data infrastructure comes under pressure, and what a CMS-ready data foundation is built from.

Introduction

It is late in the quarter.

A hospice compliance officer runs the Timeliness Compliance Threshold Report in iQIES and sees the on-time rate drifting toward 90%. The clinical work was done. The visits happened and were documented. But several HOPE Update Visit records were completed in the EHR and never left it, a batch of discharge records was rejected at validation and never resubmitted, and nobody saw the pattern until the report did. By then the 30-day windows had closed.

Nothing in that scenario is a clinical failure. It is a data-movement failure, and HOPE has made it far easier to have one. The 90% / 30-day timeliness rule itself is not new: CMS finalized it in the FY 2016 Hospice Wage Index final rule and phased it in from 70% for FY 2018 to 90% under HIS. What HOPE changed is the volume, timing, and technical path of the records that rule applies to.

That is the real question for hospice leadership: can a data environment built for HIS carry HOPE’s workload? This article covers what HOPE requires, why the 90% threshold and 4-percentage-point penalty matter more now, where hospice data stacks come under strain, and what a governed, integrated foundation looks like in practice. Connecting EHR, billing, and CMS reporting with a robust hospice EMR and referral data integration is one of the mainstays of this foundation.

What Is HOPE, and What Actually Changed from HIS?

HOPE is the standardized patient-level data collection tool CMS finalized in the FY 2025 Hospice Wage Index Final Rule (CMS-1810-F). According to CMS, it is a modification and functional replacement for the HIS, and it became the only accepted tool for patients admitted on or after October 1, 2025.

The transition closed cleanly on CMS’s side. Hospices could submit corrected or late HIS records with target dates of September 30, 2025 or earlier through February 15, 2026; after that, the legacy QIES ASAP system was decommissioned and the free HART data-entry tool was retired. A patient admitted before October 1, 2025 but discharged after it receives a HOPE-Discharge, not an HIS discharge, which is exactly the kind of edge case a transition-era data pipeline must handle correctly.

The practical differences look like this:

DimensionHIS (through Sept 30, 2025)HOPE (from Oct 1, 2025)
Records per patientTwo: Admission and DischargeUp to four: Admission, HUV1, HUV2, Discharge
Timeliness rule90% submitted and accepted within 30 daysUnchanged: 90% submitted and accepted within 30 days
Submission systemQIES ASAPiQIES
EncodingFree CMS tool (HART) availableVendor or third party required
Data collectionAbstraction from the clinical recordReal-time collection or abstraction from the clinical record
New clinical process—Symptom Follow-up Visit within 2 calendar days for moderate/severe symptom impact

Sources: CMS Getting Started with the HQRP (Jan 2026); CMS HIS and HOPE webpages; CMS HOPE training materials.

Two of those rows deserve emphasis. First, CMS states that HOPE data collection consists of collecting real-time patient-level data or abstracting data from patient clinical records, so the shift is not a ban on abstraction; it is a design built around the timing of actual patient interactions. Second, hospice providers now need a vendor or third party to encode their HOPE assessments. Every hospice is therefore running a multi-party data supply chain, whether or not it thinks of it that way.

HOPE Timepoints: Four Records, Each on Its Own Clock

HOPE layers clinical timing windows on top of regulatory submission deadlines. Per CMS training and guidance:

  • HOPE-Admission: collected within five days after the effective date of the hospice election, establishing the baseline.
  • HOPE Update Visit 1 (HUV1): on or between days 6 and 15 of the hospice stay.
  • HOPE Update Visit 2 (HUV2): on or between days 16 and 30. Whether a patient needs one, both, or neither HUV depends on length of stay.
  • HOPE-Discharge: at the end of the stay, whether by death, transfer, revocation, or live discharge.
  • Symptom Follow-up Visit (SFV): an in-person visit expected within two calendar days when pain or non-pain symptom impact is rated moderate or severe at Admission or an HUV. The SFV is a separate visit, documented in connection with the Admission or HUV that triggered it.

Each record then has its own submission deadline. CMS requires that all HOPE records be submitted to iQIES and accepted no later than 30 calendar days after the Admission Date (A0220), the HUV completion date (Z0350), or the Discharge Date (A0270), with submission times measured in Eastern time.

Our point of view: In data terms, every admission spawns a small dependency graph: up to three assessments and any triggered follow-up visits inside the first 30 days, plus a discharge record at an unknown future date, each with a clinical due date and a regulatory due date running in parallel. Under HIS, a hospice tracked two events per patient. Under HOPE it can be tracking four records and several visit windows at once. Spreadsheets and end-of-month exports do not scale to that; event-driven pipelines do.

Submission itself runs through iQIES. Before any record can move, a hospice needs at least one staff member registered as a Provider Security Official (PSO), who approves every other iQIES user. CMS strongly recommends more than one PSO and notes that failure to obtain iQIES access will affect the ability to submit HOPE records. A single PSO who leaves the organization is a single point of failure for an entire year’s compliance.

Wondering how hospitals decide which post-acute partners get the referral?

HQRP Compliance in 2026: The 90% Threshold and the 4-Point Penalty

The Hospice Quality Reporting Program (HQRP) is where HOPE stops being a clinical workflow question and becomes a financial one. HOPE compliance is based on the timeliness of data submission: hospices must submit and have accepted at least 90% of their HOPE records within the 30-day deadline. Compliance is assessed on records with a target date in the calendar year, so HOPE records with target dates from January 1 to December 31, 2026 determine the FY 2028 Annual Payment Update (APU), and the cycle repeats each year.

Two details matter for system design. First, the requirement is submitted and accepted: CMS states that providers must verify submitted records were accepted. A record rejected at validation and corrected after day 30 is a late record. Second, the deadline is per record, so the threshold is a ratio across the whole year’s volume, which under HOPE is materially larger than under HIS.

The consequence of missing the threshold is set by statute. The Consolidated Appropriations Act, 2021 raised the reduction from 2 to 4 percentage points beginning with FY 2024. CMS applies the reduction only to the fiscal year involved, not cumulatively, but it can reduce the update below zero, meaning payment rates lower than the prior year’s. For a hospice operating on tight margins, one missed reporting year can turn an expected payment increase into a payment cut across the entire Medicare census for that year.

HQRP has two other components. Hospices must contract with a CMS-approved vendor for the CAHPS® Hospice Survey, with quarterly vendor submissions (newness and size exemptions are available), and administrative claims data is drawn automatically from Medicare billing, so hospices are automatically considered compliant for that component. HOPE is the component most exposed to a hospice’s own data infrastructure, because it depends on internal systems moving information correctly and on time.

Where Hospice Data Infrastructure Comes Under Pressure

Because HOPE compliance is defined by timeliness, threshold risk is fundamentally a data-operations risk. The patterns we see most often are consistent:

  • No single timeline per patient. Election and admission dates live in the EHR, visit scheduling in a separate tool, discharge events in another workflow. No system holds the complete, authoritative list of which HOPE records are due, and when.
  • Lagging, not leading, indicators. The iQIES timeliness report shows what has already happened. Teams that rely on it alone discover a shortfall only after the 30-day windows have closed.
  • Open rejection loops. Records rejected at validation sit unworked because rejection feedback never returns to the clinician or coder who can fix it.
  • Manual handoffs to the encoding vendor. Exports, re-keying, and file transfers add days to every record and introduce errors that surface only as rejections.
  • No lineage. When a record is late, nobody can quickly trace which system, interface, or handoff introduced the delay, so the same failure repeats next month.
  • Access and continuity gaps. A single PSO, informal iQIES role management, or undocumented interface ownership turns ordinary staff turnover into a compliance event.

None of these require more clinical training to fix. They require a healthcare data platform designed with governance, integration, and lineage as first-class requirements.

How to Evaluate Hospice Software and Data Partners for HOPE

Vendor selection is where this is either solved or quietly deferred. Leadership evaluating hospice data collection software and integration partners should ask for demonstrated capability, not a HOPE form:

  • Current CMS specification alignment. Conformance with the latest HOPE data submission specifications and testing against CMS’s HOPE Validation Utility Tool (VUT) before records reach iQIES.
  • Version agility. CMS has already published several revisions of the HOPE guidance manual and item sets since launch (through v1.03 on the CMS HOPE page). Ask how quickly specification changes reach production and how they are regression-tested.
  • Closed-loop submission. Encoding and iQIES submission without manual re-keying, plus automated capture of accepted and rejected outcomes back into the operational workflow.
  • Standards-based integration with existing EHR, billing, scheduling, and referral intake systems, so HOPE compliance does not require replacing tools clinicians already rely on.
  • Deadline intelligence. Forward-looking visibility into records due, at risk, and rejected, not just a historical compliance percentage.
  • Lineage and auditability. The ability to show, for any record, its source events, transformations, submission timestamp, and acceptance status. Learn more about audit-ready data lineage here,

A point solution that satisfies today’s item set but is not built for interoperability will need rework every time CMS revises HOPE, and CMS has stated that additional measures may follow.

Building an Interoperable Data Foundation for Hospice Quality Reporting

A CMS-ready foundation is not a new EHR module or a HOPE-specific workaround. It is three disciplines working together as one healthcare data integration platform. Skip any one and the other two stay exposed.

Data Governance: The Compliance Backbone

Data governance in healthcare turns “we have the data somewhere” into “we can show where it came from, who changed it, and when it moved.” For HOPE, that means named ownership of each item section across clinical, quality, and operations teams; documented data quality rules that run before submission, such as an HUV completion date falling outside its window, an admission date inconsistent with the election date, or a moderate or severe symptom impact with no follow-up visit recorded; role-based, minimum-necessary access to PHI consistent with HIPAA; and an audit trail that answers a reviewer’s question in minutes. Our Data Quality, Governance and Compliance services build this layer. We can explore this in a deeper manner as outlined in Data Governance and CMS Compliance Frameworks for Hospice Organizations.

Data Engineering and Integration: One Timeline Instead of Many Systems

Governance defines the rules; integration makes the data move. Our Data Engineering and Integration services connect EHR, scheduling, billing, and intake systems into a single governed pipeline built around four capabilities:

  • Event-driven ingestion of elections, admissions, visits, and discharges as they occur, rather than in periodic batch exports.
  • A HOPE timeline engine that derives each patient’s clinical windows (Admission, HUV1, HUV2, SFV) and each record’s 30-day submission deadline in Eastern time from source dates.
  • Pre-submission validation against CMS specifications, so errors are fixed while the clock still allows it.
  • Closed-loop reconciliation of submitted versus accepted records, feeding rejections back to the people who can correct them.

Underneath, data is organized in distinct raw, cleansed, and reporting-ready layers rather than one undifferentiated store, an approach we explain in Medallion Architecture Explained: Bronze, Silver, and Gold Layers for Healthcare Data. That layering is what makes lineage possible: once each record has a defined path from source event to iQIES acceptance, audit-ready data lineage that survives a CMS review becomes something a compliance officer can produce on request.

What good looks like: a daily operational view showing records due in the next seven days, records past day 20 and not yet submitted, rejections awaiting correction, follow-up visits due within 48 hours, and a rolling on-time rate against the 90% threshold. These are leading indicators; the iQIES report confirms the outcome.

Data Strategy: Sequencing the Foundation for What Comes Next

Governance and integration solve today’s HOPE problem. Strategy makes sure the same foundation supports what comes next: length-of-stay and census forecasting, staffing models that anticipate HUV and follow-up visit demand, and AI agents for intake, documentation support, and patient engagement. Our Data Strategy services sequence that roadmap so the foundation is engineered once, for CMS reporting now and for analytics and AI later. It is the same principle behind the Caregence™ platform: governed, healthcare-native data first, intelligence on top.

What New Quality Measures Will HOPE Data Support?

HOPE already carries HQRP measurement: CMS continues to collect the data for the Comprehensive Assessment at Admission measure (CBE #3235) through HOPE. Beyond that, CMS has finalized two HOPE-based quality measures: Timely Follow-up for Pain Impact and Timely Follow-up for Non-Pain Symptom Impact. Each captures the percentage of assessments with a symptom follow-up visit within two days after impact was assessed as moderate or severe. CMS states that two new process measures will be added to the HQRP using HOPE data in fall 2027, the start of FY 2028, and it already describes both measures in its iQIES quality measure report materials.

Two implications follow. First, these are measures of care timeliness, so the same timeline engine that protects submission deadlines should also track follow-up visit deadlines; one foundation serves both. Second, CMS has said patients and families will be better informed about the hospice they choose through public reporting of HOPE assessment-based measures. The data a hospice generates today is the dataset its referral partners and families will eventually see.

Why This Is a Foundation, Not a Fix

Hospice executives evaluating this space often ask whether it is a compliance project or an operational one. It is both. Treating it only as the former is how organizations end up building the same pipeline twice: once under HOPE pressure and again when the next operational priority arrives.

A governed, integrated healthcare data platform is what makes HOPE submission reliable. It is also the prerequisite for what hospice leadership wants next: forecasts of length of stay and staffing needs that hold up in a board discussion, and AI agents that support clinical and administrative teams without adding compliance risk. Neither works on fragmented, ungoverned data. The foundation comes first because no other order holds up.

Not sure where your data foundation stands for HOPE, HQRP, and iQIES submission?Frequently Asked Questions